WARNING: POSTTREATMENT ACUTE EXACERBATION OF HEPATITIS B Severe acute exacerbations of hepatitis B virus (HBV) have been reported in HBV-infected patients who have discontinued anti-hepatitis B therapy, including VIREAD. Hepatic function should be monitored closely with both clinical and laboratory follow-up for at least several months in HBV-infected patients who discontinue anti-hepatitis B therapy, including VIREAD.
If appropriate, resumption of anti-hepatitis B therapy may be warranted [see Warnings and Precautions (5.1)]. WARNING: POSTTREATMENT ACUTE EXACERBATION OF HEPATITIS B See full prescribing information for complete boxed warning. Severe acute exacerbations of hepatitis B virus (HBV) have been reported in HBV-infected patients who have discontinued anti-hepatitis B therapy, including VIREAD.
Hepatic function should be monitored closely in HBV-infected patients who discontinue VIREAD. If appropriate, resumption of anti-hepatitis B therapy may be warranted. (5.1)
Use: Labeled indications
- in combination with other antiretroviral agents for the treatment of HIV-1 infection in adults and pediatric patients 2 years of age and older weighing at least 10 kg.
- for the treatment of chronic hepatitis B in adults and pediatric patients 2 years and older weighing at least 10 kg.
Full indications and usage US FDA label
1 INDICATIONS AND USAGE VIREAD is a nucleotide analog HIV-1 reverse transcriptase inhibitor and an HBV reverse transcriptase inhibitor and is indicated: in combination with other antiretroviral agents for the treatment of HIV-1 infection in adults and pediatric patients 2 years of age and older weighing at least 10 kg. (1.1) for the treatment of chronic hepatitis B in adults and pediatric patients 2 years and older weighing at least 10 kg.
(1.2) 1.1 HIV-1 Infection VIREAD is indicated in combination with other antiretroviral agents for the treatment of human immunodeficiency virus type 1 (HIV-1) infection in adults and pediatric patients 2 years of age and older weighing at least 10 kg. 1.2 Chronic Hepatitis B VIREAD is indicated for the treatment of chronic hepatitis B virus (HBV) in adults and pediatric patients 2 years of age and older weighing at least 10 kg.
Contraindications
4 CONTRAINDICATIONS None. None. (4)
US FDA labelDosing: Adult
- Testing: Prior to or when initiating VIREAD test for hepatitis B virus infection and HIV-1 infection. Prior to initiation and during use of VIREAD, on a clinically appropriate schedule, assess serum creatinine, estimated creatinine clearance, urine glucose, and urine protein in all patients. In patients with chronic kidney disease, also assess serum phosphorous. (2.1)
- Recommended tablet dosage in adults and pediatric patients weighing at least 35 kg: One VIREAD 300 mg tablet once daily taken orally without regard to food. (2.2)
- Recommended dosage in pediatric patients at least 2 years of age and adults: Tablets: For patients weighing at least 17 kg who can swallow an intact tablet, one VIREAD tablet (150 mg, 200 mg, 250 mg, or 300 mg based on body weight) once daily taken orally without regard to food. (2.2)
- Oral powder: For patients weighing at least 10 kg and unable to swallow a tablet, 8 mg per kg VIREAD oral powder (up to a maximum of 300 mg) taken once daily with food. (2.3)
- Recommended dosage in renally impaired adult patients: Creatinine clearance (CrCl) 30–49 mL/min: 300 mg every 48 hours. (2.4)
- CrCl 10–29 mL/min: 300 mg every 72 to 96 hours. (2.4)
- Hemodialysis: 300 mg every 7 days or after approximately 12 hours of dialysis. (2.4)
2.1 Testing Prior to Initiation
2.1 Testing Prior to Initiation of VIREAD for Treatment of HIV-1 Infection or Chronic Hepatitis B Prior to or when initiating VIREAD, test patients for HBV infection and HIV-1 infection. VIREAD alone should not be used in patients with HIV-1 infection [see Warnings and Precautions (5.3)]. Prior to initiation and during use of VIREAD, on a clinically appropriate schedule, assess serum creatinine, estimated creatinine clearance, urine glucose and urine protein in all patients.
In patients with chronic kidney disease, also assess serum phosphorus [see Warnings and Precautions (5.2)].
2.2 Recommended Tablet Dosage in Adults and Pediatric Patients 2 Years and Older Weighing
2.2 Recommended Tablet Dosage in Adults and Pediatric Patients 2 Years and Older Weighing at Least 17 kg The recommended dosage of VIREAD in adults and pediatric patients weighing at least 35 kg is one 300 mg tablet taken orally once daily without regard to food. The dosage for VIREAD is the same for both HIV and HBV indications.
The recommended dosage of VIREAD tablet in adults and pediatric patients 2 years and older weighing at least 17 kg is 8 mg of tenofovir disoproxil fumarate (TDF) per kg of body weight (up to a maximum of 300 mg) once daily. Dosage for pediatric patients 2 years and older weighing between 17 kg and 35 kg and able to swallow an intact tablet is provided in Table 1.
Weight should be monitored periodically and the VIREAD dose adjusted accordingly. Table 1 Recommended Dosing for Patients 2 Years and Older and Weighing at Least 17 kg Using VIREAD Tablets Body Weight (kg) Dosing of VIREAD Tablets 17 to less than 22 one 150 mg tablet once daily 22 to less than 28 one 200 mg tablet once daily 28 to less than 35 one 250 mg tablet once daily at least 35 one 300 mg tablet once daily
2.3 Recommended Oral Powder Dosage in Adults and Pediatric Patients 2 Years and Older
2.3 Recommended Oral Powder Dosage in Adults and Pediatric Patients 2 Years and Older Weighing at Least 10 kg The recommended dosage of VIREAD oral powder in adults and pediatric patients 2 years and older weighing at least 10 kg who are unable to swallow a tablet is 8 mg of TDF per kg of body weight (up to a maximum of 300 mg) once daily administered as oral powder (see Table 2). Weight should be monitored periodically and the VIREAD dose adjusted accordingly.
VIREAD oral powder should be measured only with the supplied dosing scoop. One level scoop delivers 1 g of powder, which contains 40 mg of TDF. VIREAD oral powder should be mixed in a container with 2 to 4 ounces of soft food not requiring chewing (e.g., applesauce, baby food, yogurt). The entire mixture should be ingested immediately to avoid a bitter taste.
Do not administer VIREAD oral powder in a liquid as the powder may float on top of the liquid even after stirring. Further patient instructions on how to administer VIREAD oral powder with the supplied dosing scoop are provided in the FDA-approved patient labeling (Patient Information). Table 2 Dosing for Patients 2 Years and Older Weighing at least 10 kg Using VIREAD Oral Powder Body Weight (kg) Dosing of VIREAD Oral Powder Total Daily Dosage (40 mg per scoop) 10 to less than 12 2 scoops once daily 80 mg 12 to less than 14 2.5 scoops once daily 100 mg 14 to less than 17 3 scoops once daily 120 mg 17 to less than 19 3.5 scoops once daily 140 mg 19 to less than 22 4 scoops once daily 160 mg 22 to less than 24 4.5 scoops once daily 180 mg 24 to less than 27 5 scoops once daily 200 mg 27 to less than 29 5.5 scoops once daily 220 mg 29 to less than 32 6 scoops once daily 240 mg 32 to less than 34 6.5 scoops once daily 260 mg 34 to less than 35 7 scoops once daily 280 mg at least 35 7.5 scoops once daily 300 mg
2.4 Dosage Adjustment in Patients with Renal Impairment
2.4 Dosage Adjustment in Patients with Renal Impairment Significant increase in drug exposures occurred when VIREAD was administered to subjects with moderate to severe renal impairment (creatinine clearance below 50 mL/min). Table 3 provides dosage interval adjustment for patients with renal impairment. No dosage adjustment of VIREAD tablets 300 mg is necessary for patients with mild renal impairment (creatinine clearance 50–80 mL/min) [see Warnings and Precautions (5.3), Use in Specific Populations (8.6), and Clinical Pharmacology (12.3)].
Table 3 Dosage Interval Adjustment for Adult Patients with Altered Creatinine Clearance Creatinine Clearance (mL/min) Calculated using ideal (lean) body weight. Hemodialysis Patients 50 or greater 30–49 10–29 Recommended 300 mg Dosing Interval Every 24 hours Every 48 hours Every 72 to 96 hours Every 7 days or after a total of approximately 12 hours of dialysis Generally once weekly assuming 3 hemodialysis sessions a week of approximately 4 hours' duration.
VIREAD should be administered following completion of dialysis. No data are available to make dosage recommendations in patients with creatinine clearance below 10 mL/min who are not on hemodialysis. No data are available to make dosage recommendations in pediatric patients with renal impairment.
Dosing: Altered kidney function
2.4 Dosage Adjustment in Patients with Renal Impairment Significant increase in drug exposures occurred when VIREAD was administered to subjects with moderate to severe renal impairment (creatinine clearance below 50 mL/min). Table 3 provides dosage interval adjustment for patients with renal impairment. No dosage adjustment of VIREAD tablets 300 mg is necessary for patients with mild renal impairment (creatinine clearance 50–80 mL/min) [see Warnings and Precautions (5.3), Use in Specific Populations (8.6), and Clinical Pharmacology (12.3)].
Table 3 Dosage Interval Adjustment for Adult Patients with Altered Creatinine Clearance Creatinine Clearance (mL/min) Calculated using ideal (lean) body weight. Hemodialysis Patients 50 or greater 30–49 10–29 Recommended 300 mg Dosing Interval Every 24 hours Every 48 hours Every 72 to 96 hours Every 7 days or after a total of approximately 12 hours of dialysis Generally once weekly assuming 3 hemodialysis sessions a week of approximately 4 hours' duration.
VIREAD should be administered following completion of dialysis. No data are available to make dosage recommendations in patients with creatinine clearance below 10 mL/min who are not on hemodialysis. No data are available to make dosage recommendations in pediatric patients with renal impairment.
8.6 Renal Impairment The dosing interval for VIREAD should be modified in adult patients with estimated creatinine clearance below 50 mL/min or in patients with end stage renal disease requiring dialysis [see Dosage and Administration (2.4) and Clinical Pharmacology (12.3)].
Patients with Renal Impairment The pharmacokinetics of tenofovir are altered in subjects with renal impairment [see Warnings and Precautions (5.2)]. In subjects with creatinine clearance below 50 mL/min or with end-stage renal disease (ESRD) requiring dialysis, C max, and AUC 0–∞ of tenofovir were increased (Table 14). Table 14 Pharmacokinetic Parameters (Mean ± SD) of Tenofovir 300 mg, single dose of VIREAD in Subjects with Varying Degrees of Renal Function Baseline Creatinine Clearance (mL/min) >80 N=3 50–80 N=10 30–49 N=8 12–29 N=11 C max (µg/mL) 0.34 ± 0.03 0.33 ± 0.06 0.37 ± 0.16 0.60 ± 0.19 AUC 0–∞ (µg ∙ hr/mL) 2.18 ± 0.26 3.06 ± 0.93 6.01 ± 2.50 15.98 ± 7.22 CL/F (mL/min) 1043.7 ± 115.4 807.7 ± 279.2 444.4 ± 209.8 177.0 ± 97.1 CL renal (mL/min) 243.5 ± 33.3 168.6 ± 27.5 100.6 ± 27.5 43.0 ± 31.2 Patients with Hepatic Impairment The pharmacokinetics of tenofovir following a 300 mg single dose of VIREAD have been studied in non-HIV infected subjects with moderate to severe hepatic impairment.
There were no substantial alterations in tenofovir pharmacokinetics in subjects with hepatic impairment compared with unimpaired subjects. No change in VIREAD dosing is required in patients with hepatic impairment. Assessment of Drug Interactions At concentrations substantially higher (~300-fold) than those observed in vivo, tenofovir did not inhibit in vitro drug metabolism mediated by any of the following human CYP isoforms: CYP3A4, CYP2D6, CYP2C9, or CYP2E1.
However, a small (6%) but statistically significant reduction in metabolism of CYP1A substrate was observed. Based on the results of in vitro experiments and the known elimination pathway of tenofovir, the potential for CYP-mediated interactions involving tenofovir with other medicinal products is low. VIREAD has been evaluated in healthy volunteers in combination with other antiretroviral and potential concomitant drugs.
Tables 15 and 16 summarize pharmacokinetic effects of coadministered drug on tenofovir pharmacokinetics and effects of VIREAD on the pharmacokinetics of coadministered drug. TDF is a substrate of P-glycoprotein (P-gp) and breast cancer resistance protein (BCRP) transporters. When TDF is coadministered with an inhibitor of these transporters, an increase in absorption may be observed.
No clinically significant drug interactions have been observed between VIREAD and efavirenz, methadone, nelfinavir, oral contraceptives, ribavirin, or sofosbuvir. Table 15 Drug Interactions: Changes in Pharmacokinetic Parameters for Tenofovir Subjects received VIREAD 300 mg once daily. in the Presence of the Coadministered Drug Coadministered Drug Dose of Coadministered Drug (mg) N % Change of Tenofovir Pharmacokinetic Parameters Increase = ↑; Decrease = ↓; No Effect = ⇔ (90% CI) C max AUC C min Atazanavir Reyataz Prescribing Information. 400 once daily × 14 days 33 ↑ 14 (↑ 8 to ↑ 20) ↑ 24 (↑ 21 to ↑ 28) ↑ 22 (↑ 15 to ↑ 30) Atazanavir/ Ritonavir 300/100 once daily 12 ↑ 34 (↑ 20 to ↑ 51) ↑ 37 (↑ 30 to ↑ 45) ↑ 29 (↑ 21 to ↑ 36) Darunavir/ Ritonavir Prezista Prescribing Information. 300/100 twice daily 12 ↑ 24 (↑ 8 to ↑ 42) ↑ 22 (↑ 10 to ↑ 35) ↑ 37 (↑ 19 to ↑ 57) Indinavir 800 three times daily × 7 days 13 ↑ 14 (↓ 3 to ↑ 33) ⇔ ⇔ Ledipasvir/ Sofosbuvir Data generated from simultaneous dosing with HARVONI (ledipasvir/sofosbuvir).
Staggered administration (12 hours apart) provided similar results., Comparison based on exposures when administered as atazanavir/ritonavir + FTC/TDF. 90/400 once daily × 10 days 24 ↑ 47 (↑ 37 to ↑ 58) ↑ 35 (↑ 29 to ↑ 42) ↑ 47 (↑ 38 to ↑ 57) Ledipasvir/ Sofosbuvir, Comparison based on exposures when administered as darunavir/ritonavir + FTC/TDF. 23 ↑ 64 (↑ 54 to ↑ 74) ↑ 50 (↑ 42 to ↑ 59) ↑ 59 (↑ 49 to ↑ 70) Ledipasvir/ Sofosbuvir Study conducted with ATRIPLA ® (EFV/FTC/TDF) coadministered with HARVONI; coadministration with HARVONI also results in comparable increases in tenofovir exposure when TDF is administered as COMPLERA ® (FTC/rilpivirine/TDF), or TRUVADA + dolutegravir. 90/40
Kidney-specific guidance from renalcarematters.com: in preparation.
Dosing: Pediatric
Pediatric use (US label) US FDA label
8.4 Pediatric Use Pediatric Patients 2 Years and Older with HIV-1 Infection The safety and effectiveness of VIREAD in pediatric patients 2 years to less than 18 years of age is supported by data from two randomized trials. Trial 352 was a randomized controlled trial in 92 HIV-1 treatment experienced subjects 2 years to less than 12 years of age who were virologically suppressed on a stavudine- or zidovudine-containing regimen and were randomized to either switch to a VIREAD-containing regimen (N=44) or stay on their original regimen (N=48) for 48 weeks.
At Week 48, 89% of subjects in the VIREAD treatment group and 90% of subjects in the d4T or AZT treatment group had HIV-1 RNA concentrations <400 copies/mL. Trial 321 was a placebo-controlled trial in 87 HIV-1 treatment experienced subjects 12 years to less than 18 years of age who were treated with VIREAD (N=45) or placebo (N=42) in combination with an optimized background regimen for 48 weeks.
Overall, the trial failed to show a difference in virologic response between the VIREAD and placebo groups. Subgroup analyses suggest the lack of difference in virologic response may be attributable to imbalances between treatment arms in baseline viral susceptibility to VIREAD and OBR [see Adverse Reactions (6.1) and Clinical Studies (14.3)].
Although changes in HIV-1 RNA in these highly treatment-experienced subjects in Trial 321 were less than anticipated, the pharmacokinetic profile of tenofovir in patients 2 years to less than 18 years of age at the recommended doses was similar to that found to be safe and effective in adult clinical trials [see Clinical Pharmacology (12.3)]. The effects of VIREAD-associated changes in BMD and biochemical markers on long-term bone health and future fracture risk in HIV-1 pediatric patients 2 years and older are unknown.
The long-term effect of lower spine and total body BMD on skeletal growth in pediatric patients 2 years and older, and in particular, the effects of long-duration exposure in younger children is unknown [see Warnings and Precautions (5.5), Adverse Reactions (6.1)]. Safety and effectiveness of VIREAD in pediatric patients younger than 2 years of age and weighing less than 10 kg with HIV-1 infection have not been established.
Pediatric Patients 2 Years of Age and Older with Chronic Hepatitis B The safety and effectiveness of VIREAD in pediatric patients 2 years to less than 18 years of age is supported by data from two randomized trials (Trial 115 and Trial 144) in which VIREAD was administered to HBV-infected treatment-experienced subjects. In Trial 115, 106 HBeAg negative (9%) and positive (91%) subjects 12 years to less than 18 years of age with chronic HBV infection were randomized to receive blinded treatment with VIREAD or placebo for 72 weeks.
At Week 72, 88% of subjects in the VIREAD group and 0% of subjects in the placebo group had HBV DNA <400 copies/mL (69 IU/mL). In Trial 144, 89 HBeAg positive (96%) and negative (4%) subjects 2 years to less than 12 years of age were treated with VIREAD 8 mg/kg up to maximum dose of 300 mg or placebo once daily for 48 weeks.
At Week 48, 77% of subjects in the VIREAD group and 7% of subjects in the placebo group had HBV DNA <400 copies/mL (69 IU/mL). The effects of VIREAD-associated changes in BMD and biochemical markers on long-term bone health and future fracture risk in chronic HBV-infected pediatric patients 2 years and older are unknown.
The long-term effect of lower spine and total body BMD on skeletal growth in pediatric patients 2 years and older, and in particular, the effects of long-duration exposure in younger children is unknown [see Warnings and Precautions (5.5), Adverse Reactions (6.1)]. Safety and effectiveness of VIREAD in chronic HBV-infected pediatric patients younger than 2 years of age and weighing less than 10 kg have not been established.
Dosing: Older adult
Geriatric use (US label) US FDA label
8.5 Geriatric Use Clinical trials of VIREAD did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. In general, dose selection for the elderly patient should be cautious, keeping in mind the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
Dosage forms
Philippines
- Film-coated tablet: 300 mg
Registered products in the Philippines
12 products registered with the Food and Drug Administration (FDA) Philippines list Tenofovir disoproxil as the generic name. Registration status changes; confirm a product's current status on the FDA portal before relying on it.
All registered products12
| Package insert | |||||||
|---|---|---|---|---|---|---|---|
AnviraTenofovir disoproxil fumarate | 300 mg Film-Coated TabletAlu/Alu Blister Pack x 10's (Box of 30's) | Rx | Lloyd Laboratories, Inc.Bulacan | Trader: Innogen Pharmaceuticals, Inc. | DRP-10413 | Sep 23, 2031 | |
FovirTenofovir Disoproxil Fumarate | 300 mg Film-Coated TabletWhite Opaque HDPE Bottle with Desiccant x 30's Box of 1's | Rx | Laurus Labs LimitedIndia | I.E. Medica, Inc. | DRP-9104 | Nov 19, 2027 | |
HivarTenofovir Disoproxil Fumarate | 300mg Film-Coated TabletAlu/PVDC Blister Pack x 10's (Box of 30's and 100's) | Rx | Simpex Pharma Pvt. Ltd.India | Despina Pharma Inc. | DRP-14427 | Sep 5, 2028 | |
HofovirTenofovir Disoproxil Fumarate | 300mg Film Coated TabletWhite, opaque HDPE bottle with white opaque polypropylene (PP) child resistant cap x 30's (Box of 1 bottle x 30 tablets) | Rx | Chia Tai-Tianqing Pharmaceutical Group Co., Ltd.China | Hovid Inc.Trader: Hovid Bhd. | DRP-12898 | Oct 27, 2027 | |
noneTenofovir disoproxil fumarate | 300 mg Film-Coated TabletWhite opaque HDPE bottle with white opaque child resistant PP cap x 30 tablets (box of 30 tablets); and White opaque HDPE bottle with white opaque child resistant PP cap x 30 tablets (box of 30 tablets) (For DOH use only); | Rx | Hetero Labs LimitedIndia | Importer: Camber Pharmaceuticals, Inc. | DR-XY45900 | May 23, 2027 | |
NoneTenofovir Disoproxil Fumarate | 300 mg Film-Coated TabletWhite Opaque HDPE Bottle with Desiccant x 30's Box of 1's | Rx | Laurus Labs LimitedIndia | I.E. Medica, Inc. | DRP-9103 | Nov 19, 2027 | |
Tenofo-BTenofovir Disoproxil Fumarate | 300 mg Film-Coated TabletWhite HDPE Bottle x 30's (Box of 1 bottle) | Rx | Getz Pharma (Pvt.), Ltd.Pakistan | Importer: Getz Pharma (Phils.), Inc. | DRP-16169 | Jan 30, 2027 | |
TenohopeTenofovir Disoproxil Fumarate | 300 mg Film-Coated TabletWhite HDPE bottle and cap x 30's (Box of 30's) | Rx | Macleods Pharmaceuticals LimitedIndia | Macleods Pharmaceuticals Philippines, Inc. | DR-XY49135 | Jul 16, 2029 | |
TenolivTenofovir Disoproxil Fumarate | 300 mg Film-Coated TabletAlu/Alu Blister Pack x 10's (Box of 10's) | Rx | RV Group Phil. BranchIndia | RV Lifesciences Limited | DRP-15271 | Jun 4, 2029 | |
TenolonTenofovir Disoproxil Fumarate | 300 mg Film-Coated TabletHDPE Bottle with white opaque HDPE screw cap x 30 tablets (Box of 30 tablets) | Rx | Shijiazhuang Lonzeal Pharmaceuticals Co., Ltd.China | SMHP Pharmaceuticals Incorporated | DRP-17036 | Sep 12, 2030 | |
Tenovir 300Tenofovir disoproxil fumarate | 300 mg Film Coated TabletAlu/Alu Blister Pack x 10’s (Box of 30’s) | Rx | Unison Laboratories Co., Ltd.Thailand | JustRight Healthcare Inc. | DR-XY49704 | Apr 29, 2031 | |
TenvirTenofovir disoproxil fumarate | 300 mg Film-Coated TabletWhite opaque HDPE bottle with white opaque non-child resistant screw cap x 30 tablets (Box of 30 tablets) | Rx | Cipla Limited - Goa (Unit VII)India | Phil Pharmawealth, Inc. | DR-XY47459 | Oct 13, 2031 |
Source: FDA Philippines product registration database. "Valid until" is the registration validity date listed by the FDA; a past date may mean a renewal is pending. Package insert links point to files published by the FDA.
United States (label)
Dosage forms and strengths (US label) US FDA label
3 DOSAGE FORMS AND STRENGTHS VIREAD is available as tablets in four dose strengths or as an oral powder. 150 mg Tablets: 150 mg of tenofovir disoproxil fumarate (TDF) (equivalent to 123 mg of tenofovir disoproxil): triangle shaped, white, film coated, debossed with "GSI" on one side and with "150" on the other side. 200 mg Tablets: 200 mg of TDF (equivalent to 163 mg of tenofovir disoproxil): round shaped, white, film coated, debossed with "GSI" on one side and with "200" on the other side. 250 mg Tablets: 250 mg of TDF (equivalent to 204 mg of tenofovir disoproxil): capsule shaped, white, film coated, debossed with "GSI" on one side and with "250" on the other side. 300 mg Tablets: 300 mg of TDF (equivalent to 245 mg of tenofovir disoproxil): almond shaped, light blue, film coated, debossed with "GILEAD" and "4331" on one side and with "300" on the other side. Oral Powder: white, taste-masked, coated granules containing 40 mg of TDF (equivalent to 33 mg of tenofovir disoproxil) per level scoop.
Each level scoop contains 1 gram of oral powder. Tablets: 150 mg, 200 mg, 250 mg, and 300 mg of tenofovir disoproxil fumarate. (3) Oral Powder: 40 mg per 1 g of oral powder of tenofovir disoproxil fumarate. (3)
Warnings/Precautions
The boxed warning is shown at the top of this page.
- New onset or worsening renal impairment: Can include acute renal failure and Fanconi syndrome. Avoid administering VIREAD with concurrent or recent use of nephrotoxic drugs. (5.2)
- HIV testing: HIV antibody testing should be offered to all HBV-infected patients before initiating therapy with VIREAD. VIREAD should only be used as part of an appropriate antiretroviral combination regimen in HIV-infected patients with or without HBV coinfection. (5.3)
- Immune reconstitution syndrome: May necessitate further evaluation and treatment. (5.4)
- Decreases in bone mineral density (BMD): Consider assessment of BMD in patients with a history of pathologic fracture or other risk factors for osteoporosis or bone loss. (5.5)
- Lactic acidosis/severe hepatomegaly with steatosis: Discontinue treatment in patients who develop symptoms or laboratory findings suggestive of lactic acidosis or pronounced hepatotoxicity. (5.6)
5.1 Severe Acute Exacerbation of Hepatitis B in Patients with HBV Infection
5.1 Severe Acute Exacerbation of Hepatitis B in Patients with HBV Infection All patients should be tested for the presence of chronic hepatitis B virus (HBV) before or when initiating VIREAD [see Dosage and Administration (2.1)]. Discontinuation of anti-HBV therapy, including VIREAD, may be associated with severe acute exacerbations of hepatitis B.
Patients infected with HBV who discontinue VIREAD should be closely monitored with both clinical and laboratory follow-up for at least several months after stopping treatment. If appropriate, resumption of anti-hepatitis B therapy may be warranted, especially in patients with advanced liver disease or cirrhosis, since posttreatment exacerbation of hepatitis may lead to hepatic decompensation and liver failure.
5.2 New Onset or Worsening Renal Impairment
5.2 New Onset or Worsening Renal Impairment Tenofovir is principally eliminated by the kidney. Renal impairment, including cases of acute renal failure and Fanconi syndrome (renal tubular injury with severe hypophosphatemia), has been reported with the use of VIREAD [see Adverse Reactions (6.2)]. Prior to initiation and during use of VIREAD, on a clinically appropriate schedule, assess serum creatinine, estimated creatinine clearance, urine glucose, and urine protein in all patients.
In patients with chronic kidney disease, also assess serum phosphorus. Dosing interval adjustment of VIREAD and close monitoring of renal function are recommended in all patients with creatinine clearance below 50 mL/min [see Dosage and Administration (2.4)]. No safety or efficacy data are available in patients with renal impairment who received VIREAD using these dosing guidelines, so the potential benefit of VIREAD therapy should be assessed against the potential risk of renal toxicity.
VIREAD should be avoided with concurrent or recent use of a nephrotoxic agent (e.g., high-dose or multiple non-steroidal anti-inflammatory drugs [NSAIDs]) [see Drug Interactions (7.1)]. Cases of acute renal failure after initiation of high-dose or multiple NSAIDs have been reported in HIV-infected patients with risk factors for renal dysfunction who appeared stable on TDF.
Some patients required hospitalization and renal replacement therapy. Alternatives to NSAIDs should be considered, if needed, in patients at risk for renal dysfunction. Persistent or worsening bone pain, pain in extremities, fractures and/or muscular pain or weakness may be manifestations of proximal renal tubulopathy and should prompt an evaluation of renal function in patients at risk of renal dysfunction.
5.3 Patients Coinfected with HIV-1 and HBV
5.3 Patients Coinfected with HIV-1 and HBV Due to the risk of development of HIV-1 resistance, VIREAD should only be used in HIV-1 and HBV coinfected patients as part of an appropriate antiretroviral combination regimen. HIV-1 antibody testing should be offered to all HBV-infected patients before initiating therapy with VIREAD.
It is also recommended that all patients with HIV-1 be tested for the presence of chronic hepatitis B before initiating treatment with VIREAD.
5.4 Immune Reconstitution Syndrome
5.4 Immune Reconstitution Syndrome Immune reconstitution syndrome has been reported in HIV-1 infected patients treated with combination antiretroviral therapy, including VIREAD. During the initial phase of combination antiretroviral treatment, HIV-1 infected patients whose immune system responds may develop an inflammatory response to indolent or residual opportunistic infections (such as Mycobacterium avium infection, cytomegalovirus, Pneumocystis jirovecii pneumonia [PCP], or tuberculosis), which may necessitate further evaluation and treatment.
Autoimmune disorders (such as Graves' disease, polymyositis, and Guillain-Barré syndrome) have also been reported to occur in the setting of immune reconstitution; however, the time to onset is more variable, and can occur many months after initiation of treatment.
5.5 Bone Loss and Mineralization Defects Bone
5.5 Bone Loss and Mineralization Defects Bone Mineral Density In clinical trials in HIV-1 infected adults, VIREAD was associated with slightly greater decreases in bone mineral density (BMD) and increases in biochemical markers of bone metabolism, suggesting increased bone turnover relative to comparators [see Adverse Reactions (6.1)]. Serum parathyroid hormone levels and 1,25 Vitamin D levels were also higher in subjects receiving VIREAD.
Clinical trials evaluating VIREAD in pediatric subjects were conducted. Under normal circumstances, BMD increases rapidly in pediatric patients. In HIV-1 infected subjects 2 years to less than 18 years of age, bone effects were similar to those observed in adult subjects and suggest increased bone turnover. Total body BMD gain was less in the VIREAD-treated HIV-1 infected pediatric subjects as compared to the control groups.
Similar trends were observed in chronic HBV-infected pediatric subjects 2 years to less than 18 years of age. In all pediatric trials, normal skeletal growth (height) was not affected for the duration of the clinical trials [see Adverse Reactions (6.1)]. The effects of VIREAD-associated changes in BMD and biochemical markers on long-term bone health and future fracture risk in adults and pediatric subjects 2 years and older are unknown.
The long-term effect of lower spine and total body BMD on skeletal growth in pediatric patients, and in particular, the effects of long-duration exposure in younger children is unknown. Although the effect of supplementation with calcium and vitamin D was not studied, such supplementation may be beneficial. Assessment of BMD should be considered for adult and pediatric patients who have a history of pathologic bone fracture or other risk factors for osteoporosis or bone loss.
If bone abnormalities are suspected, appropriate consultation should be obtained. Mineralization Defects Cases of osteomalacia associated with proximal renal tubulopathy, manifested as bone pain or pain in extremities and which may contribute to fractures, have been reported in association with VIREAD use [see Adverse Reactions (6.2)].
Arthralgia and muscle pain or weakness have also been reported in cases of proximal renal tubulopathy. Hypophosphatemia and osteomalacia secondary to proximal renal tubulopathy should be considered in patients at risk of renal dysfunction who present with persistent or worsening bone or muscle symptoms while receiving TDF-containing products [see Warnings and Precautions (5.2)].
5.6 Lactic Acidosis/Severe Hepatomegaly with Steatosis
5.6 Lactic Acidosis/Severe Hepatomegaly with Steatosis Lactic acidosis and severe hepatomegaly with steatosis, including fatal cases, have been reported with the use of nucleoside analogs, including TDF, alone or in combination with other antiretrovirals. Treatment with VIREAD should be suspended in any patient who develops clinical or laboratory findings suggestive of lactic acidosis or pronounced hepatotoxicity (which may include hepatomegaly and steatosis even in the absence of marked transaminase elevations).
5.7 Risk of Adverse Reactions Due to Drug Interactions
5.7 Risk of Adverse Reactions Due to Drug Interactions The concomitant use of VIREAD and other drugs may result in known or potentially significant drug interactions, some of which may lead to possible clinically significant adverse reactions from greater exposures of concomitant drugs [see Drug Interactions (7.2)]. See Table 12 for steps to prevent or manage these possible and known significant drug interactions, including dosing recommendations.
Consider the potential for drug interactions prior to and during therapy with VIREAD; review concomitant medications during therapy with VIREAD; and monitor for adverse reactions associated with the concomitant drugs.
Drug interactions
- Tenofovir disoproxil fumarate increases didanosine concentrations. Dose reduction and close monitoring for didanosine toxicity are warranted. (7.2)
- Coadministration decreases atazanavir concentrations. When coadministered with VIREAD, use atazanavir given with ritonavir. (7.2)
- Coadministration of VIREAD with certain HIV-1 protease inhibitors or certain drugs to treat HCV increases tenofovir concentrations. Monitor for evidence of tenofovir toxicity. (7.2)
- Consult Full Prescribing Information prior to and during treatment for important drug interactions. (7.2)
7.1 Drugs Affecting Renal Function
7.1 Drugs Affecting Renal Function Tenofovir is primarily eliminated by the kidneys [see Clinical Pharmacology (12.3)]. Coadministration of VIREAD with drugs that are eliminated by active tubular secretion may increase concentrations of tenofovir and/or the coadministered drug. Some examples include, but are not limited to, acyclovir, cidofovir, ganciclovir, valacyclovir, valganciclovir, aminoglycosides (e.g., gentamicin), and high-dose or multiple NSAIDs [see Warnings and Precautions (5.2)].
Drugs that decrease renal function may increase concentrations of tenofovir. In the treatment of chronic hepatitis B, VIREAD should not be administered in combination with HEPSERA (adefovir dipivoxil).
7.2 Established and Significant Interactions
7.2 Established and Significant Interactions Table 12 provides a listing of established or clinically significant drug interactions. The drug interactions described are based on studies conducted with TDF [see Clinical Pharmacology (12.3)]. Table 12 Established and Significant This table is not all inclusive. Drug Interactions: Alteration in Dose or Regimen May Be Recommended Based on Drug Interaction Trials Concomitant Drug Class: Drug Name Effect on Concentration ↑=Increase, ↓=Decrease Clinical Comment NRTI: didanosine ↑ didanosine Patients receiving VIREAD and didanosine should be monitored closely for didanosine-associated adverse reactions.
Discontinue didanosine in patients who develop didanosine-associated adverse reactions. Higher didanosine concentrations could potentiate didanosine-associated adverse reactions, including pancreatitis, and neuropathy. Suppression of CD4+ cell counts has been observed in patients receiving VIREAD with didanosine 400 mg daily.
In patients weighing greater than 60 kg, reduce the didanosine dose to 250 mg when it is coadministered with VIREAD. In patients weighing less than 60 kg, reduce the didanosine dose to 200 mg when it is coadministered with VIREAD. When coadministered, VIREAD and Videx EC may be taken under fasted conditions or with a light meal (less than 400 kcal, 20% fat).
HIV-1 Protease Inhibitor s: atazanavir ↓ atazanavir When coadministered with VIREAD, atazanavir 300 mg should be given with ritonavir 100 mg. lopinavir/ritonavir atazanavir/ritonavir darunavir/ritonavir ↑ tenofovir Monitor patients receiving VIREAD concomitantly with lopinavir/ritonavir, ritonavir-boosted atazanavir, or ritonavir-boosted darunavir for TDF-associated adverse reactions. Discontinue VIREAD in patients who develop TDF-associated adverse reactions.
Hepatitis C Antiviral Agents: sofosbuvir/velpatasvir sofosbuvir/velpatasvir/voxilaprevir ↑ tenofovir Monitor patients receiving VIREAD concomitantly with EPCLUSA ® (sofosbuvir/velpatasvir) for adverse reactions associated with TDF. ledipasvir/sofosbuvir Monitor patients receiving VIREAD concomitantly with HARVONI ® (ledipasvir/sofosbuvir) without an HIV-1 protease inhibitor/ritonavir or an HIV-1 protease inhibitor/cobicistat combination, for adverse reactions associated with TDF. In patients receiving VIREAD concomitantly with HARVONI and an HIV-1 protease inhibitor/ritonavir or an HIV-1 protease inhibitor/cobicistat combination, consider an alternative HCV or antiretroviral therapy, as the safety of increased tenofovir concentrations in this setting has not been established.
If coadministration is necessary, monitor for adverse reactions associated with TDF.
Metabolism and transporters (CYP, P-gp, OATP; US label) US FDA label
Assessment of Drug Interactions At concentrations substantially higher (~300-fold) than those observed in vivo, tenofovir did not inhibit in vitro drug metabolism mediated by any of the following human CYP isoforms: CYP3A4, CYP2D6, CYP2C9, or CYP2E1.
However, a small (6%) but statistically significant reduction in metabolism of CYP1A substrate was observed.
TDF is a substrate of P-glycoprotein (P-gp) and breast cancer resistance protein (BCRP) transporters.
Adverse reactions
- The following adverse reactions are discussed in other sections of the labeling: Severe Acute Exacerbation of Hepatitis B in Patients with HBV Infection [see Warnings and Precautions (5.1)]. New Onset or Worsening Renal Impairment [see Warnings and Precautions (5.2)]. Immune Reconstitution Syndrome [see Warnings and Precautions (5.4)]. Bone Loss and Mineralization Defects [see Warnings and Precautions (5.5)]. Lactic Acidosis/Severe Hepatomegaly with Steatosis [see Warnings and Precautions (5.6)]. In HIV-infected adult subjects: Most common adverse reactions (incidence greater than or equal to 10%, Grades 2–4) were rash, diarrhea, nausea, headache, pain, depression, and asthenia. (6.1)
- In HBV-infected subjects with compensated liver disease: Most common adverse reaction (all grades) was nausea (9%). (6.1)
- In HBV-infected subjects with decompensated liver disease: Most common adverse reactions (incidence greater than or equal to 10%, all grades) were abdominal pain, nausea, insomnia, pruritus, vomiting, dizziness, and pyrexia. (6.1)
- In pediatric subjects: Adverse reactions in pediatric subjects were consistent with those observed in adults. (6.1)
- To report SUSPECTED ADVERSE REACTIONS, contact Gilead Sciences, Inc. at 1-800-GILEAD-5 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1 Clinical Trials Experience
6.1 Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adverse Reactions from Clinical Trials Experience in HIV-1 Infected Adults More than 12,000 subjects have been treated with VIREAD alone or in combination with other antiretroviral medicinal products for periods of 28 days to 215 weeks in clinical trials and expanded access programs.
A total of 1,544 subjects have received VIREAD 300 mg once daily in clinical trials; over 11,000 subjects have received VIREAD in expanded access programs. The most common adverse reactions (incidence greater than or equal to 10%, Grades 2–4) identified from any of the 3 large controlled clinical trials include rash, diarrhea, headache, pain, depression, asthenia, and nausea.
Clinical Trials in Treatment-Naïve HIV-1 Infected Adult Subjects In Trial 903, 600 antiretroviral-naïve subjects received VIREAD (N=299) or stavudine (d4T) (N=301) administered in combination with lamivudine (3TC) and efavirenz (EFV) for 144 weeks. The most common adverse reactions were mild to moderate gastrointestinal events and dizziness.
Mild adverse reactions (Grade 1) were common with a similar incidence in both arms and included dizziness, diarrhea, and nausea. Table 4 provides the treatment-emergent adverse reactions (Grades 2–4) occurring in greater than or equal to 5% of subjects treated in any treatment group. Table 4 Selected Adverse Reactions Frequencies of adverse reactions are based on all treatment-emergent adverse events, regardless of relationship to study drug.
(Grades 2–4) Reported in ≥5% in Any Treatment Group in Trial 903 (0–144 Weeks) VIREAD+3TC+EFV d4T+3TC+EFV N=299 N=301 Rash event Rash event includes rash, pruritus, maculopapular rash, urticaria, vesiculobullous rash, and pustular rash. 18% 12% Headache 14% 17% Pain 13% 12% Diarrhea 11% 13% Depression 11% 10% Back pain 9% 8% Nausea 8% 9% Fever 8% 7% Abdominal pain 7% 12% Asthenia 6% 7% Anxiety 6% 6% Vomiting 5% 9% Insomnia 5% 8% Arthralgia 5% 7% Pneumonia 5% 5% Dyspepsia 4% 5% Dizziness 3% 6% Myalgia 3% 5% Lipodystrophy Lipodystrophy represents a variety of investigator-described adverse events not a protocol-defined syndrome. 1% 8% Peripheral neuropathy Peripheral neuropathy includes peripheral neuritis and neuropathy. 1% 5% Laboratory Abnormalities: Table 5 provides a list of laboratory abnormalities (Grades 3–4) observed in Trial 903. With the exception of fasting cholesterol and fasting triglyceride elevations that were more common in the d4T group (40% and 9%) compared with the VIREAD group (19% and 1%), respectively, laboratory abnormalities observed in this trial occurred with similar frequency in the VIREAD and d4T treatment arms.
Table 5 Grades 3–4 Laboratory Abnormalities Reported in ≥1% of VIREAD-Treated Subjects in Trial 903 (0–144 Weeks) VIREAD+3TC+EFV d4T+3TC+EFV N=299 N=301 Any ≥ Grade 3 Laboratory Abnormality 36% 42% Fasting Cholesterol (>240 mg/dL) 19% 40% Creatine Kinase (M: >990 U/L; F: >845 U/L) 12% 12% Serum Amylase (>175 U/L) 9% 8% AST (M: >180 U/L; F: >170 U/L) 5% 7% ALT (M: >215 U/L; F: >170 U/L) 4% 5% Hematuria (>100 RBC/HPF) 7% 7% Neutrophils (<750/mm 3) 3% 1% Fasting Triglycerides (>750 mg/dL) 1% 9% Changes in Bone Mineral Density: In HIV-1 infected adult subjects in Trial 903, there was a significantly greater mean percentage decrease from baseline in BMD at the lumbar spine in subjects receiving VIREAD + 3TC + EFV (−2.2% ± 3.9) compared with subjects receiving d4T + 3TC + EFV (−1.0% ± 4.6) through 144 weeks. Changes in BMD at the hip were similar between the two treatment groups (−2.8% ± 3.5 in the VIREAD group vs. −2.4% ± 4.5 in the d4T group).
In both groups, the majority of the reduction in BMD occurred in the first 24–48 weeks of the trial and this reduction was sustained through Week 144. Twenty-eight percent of VIREAD-treated subjects vs. 21% of d4T-treated subjects lost at least 5% of BMD at the spine or 7% of BMD at the hip. Clinically relevant fractures (excluding fingers and toes) were reported in 4 subjects in the VIREAD group and 6 subjects in the d4T group.
In addition, there were significant increases in biochemical markers of bone metabolism (serum bone-specific alkaline phosphatase, serum osteocalcin, serum C telopeptide, and urinary N telopeptide) and higher serum parathyroid hormone levels and 1,25 Vitamin D levels in the VIREAD group relative to the d4T group; however, except for bone-specific alkaline phosphatase, these changes resulted in values that remained within the normal range [see Warnings and Precautions (5.5)]. In Trial 934, 511 antiretroviral-naïve subjects received efavirenz (EFV) administered in combination with either emtricitabine (FTC) + VIREAD (N=257) or zidovudine (AZT)/lamivudine (3TC) (N=254) for 144 weeks.
The most common adverse reactions (incidence greater than or equal to 10%, all grades) included diarrhea, nausea, fatigue, headache, dizziness, depression, insomnia, abnormal dreams, and rash. Table 6 provides the treatment-emergent adverse reactions (Grades 2–4) occurring in greater than or equal to 5% of subjects treated in any treatment group.
Table 6 Selected Adverse Reactions Frequencies of adverse reactions are based on all treatment-emergent adverse events, regardless of relationship to study drug. (Grades 2–4) Reported in ≥5% in Any Treatment Group in Trial 934 (0–144 Weeks) VIREAD From Weeks 96 to 144 of the trial, subjects received TRUVADA ® with EFV in place of VIREAD + FTC with EFV. +FTC+EFV AZT/3TC+EFV N=257 N=254 Fatigue 9% 8% Depression 9% 7% Nausea 9% 7% Diarrhea 9% 5% Dizziness 8% 7% Upper respiratory tract infections 8% 5% Sinusitis 8% 4% Rash event Rash event includes rash, exfoliative rash, rash generalized, rash macular, rash maculopapular, rash pruritic, and rash vesicular. 7% 9% Headache 6% 5% Insomnia 5% 7% Nasopharyngitis 5% 3% Vomiting 2% 5% Laboratory Abnormalities: Laboratory abnormalities observed in this trial were generally consistent with those seen in previous trials (Table 7).
Table 7 Significant Laboratory Abnormalities Reported in ≥1% of Subjects in Any Treatment Group in Trial 934 (0–144 Weeks) VIREAD+FTC+EFV From Weeks 96 to 144 of the trial, subjects received TRUVADA with EFV in place of VIREAD + FTC with EFV. AZT/3TC+EFV N=257 N=254 Any ≥ Grade 3 Laboratory Abnormality 30% 26% Fasting Cholesterol (>240 mg/dL) 22% 24% Creatine Kinase (M: >990 U/L; F: >845 U/L) 9% 7% Serum Amylase (>175 U/L) 8% 4% Alkaline Phosphatase (>550 U/L) 1% 0% AST (M: >180 U/L; F: >170 U/L) 3% 3% ALT (M: >215 U/L; F: >170 U/L) 2% 3% Hemoglobin (<8.0 mg/dL) 0% 4% Hyperglycemia (>250 mg/dL) 2% 1% Hematuria (>75 RBC/HPF) 3% 2% Glycosuria (≥3+) <1% 1% Neutrophils (<750/mm 3) 3% 5% Fasting Triglycerides (>750 mg/dL) 4% 2% Clinical Trials in Treatment-Experienced HIV-1 Infected Adult Subjects In Trial 907, the adverse reactions seen in HIV-1 infected treatment-experienced subjects were generally consistent with those seen in treatment-naïve subjects, including mild to moderate gastrointestinal events, such as nausea, diarrhea, vomiting, and flatulence.
Less than 1% of subjects discontinued participation in the clinical trials due to gastrointestinal adverse reactions. Table 8 provides the treatment-emergent adverse reactions (Grades 2–4) occurring in greater than or equal to 3% of subjects treated in any treatment group. Table 8 Selected Adverse Reactions Frequencies of adverse reactions are based on all treatment-emergent adverse events, regardless of relationship to study drug.
(Grades 2–4) Reported in ≥3% in Any Treatment Group in Trial 907 (0–48 Weeks) VIREAD N=368 (Week 0–24) Placebo N=182 (Week 0–24) VIREAD N=368 (Week 0–48) Placebo Crossover to VIREAD N=170 (Week 24–48) Body as a Whole Asthenia 7% 6% 11% 1% Pain 7% 7% 12% 4% Headache 5% 5% 8% 2% Abdominal pain 4% 3% 7% 6% Back pain 3% 3% 4% 2% Chest pain 3% 1% 3% 2% Fever 2% 2% 4% 2% Digestive System Diarrhea 11% 10% 16% 11% Nausea 8% 5% 11% 7% Vomiting 4% 1% 7% 5% Anorexia 3% 2% 4% 1% Dyspepsia 3% 2% 4% 2% Flatulence 3% 1% 4% 1% Respiratory Pneumonia 2% 0% 3% 2% Nervous System Depression 4% 3% 8% 4% Insomnia 3% 2% 4% 4% Peripheral neuropathy Peripheral neuropathy includes peripheral neuritis and neuropathy. 3% 3% 5% 2% Dizziness 1% 3% 3% 1% Skin and Appendage Rash event Rash event includes rash, pruritus, maculopapular rash, urticaria, vesiculobullous rash, and pustular rash. 5% 4% 7% 1% Sweating 3% 2% 3% 1% Musculoskeletal Myalgia 3% 3% 4% 1% Metabolic Weight loss 2% 1% 4% 2% Laboratory Abnormalities: Table 9 provides a list of Grade 3–4 laboratory abnormalities observed in Trial 907. Laboratory abnormalities occurred with similar frequency in the VIREAD and placebo groups.
Table 9 Grades 3–4 Laboratory Abnormalities Reported in ≥1% of VIREAD-Treated Subjects in Trial 907 (0–48 Weeks) VIREAD N=368 (Week 0–24) Placebo N=182 (Week 0–24) VIREAD N=368 (Week 0–48) Placebo Crossover to VIREAD N=170 (Week 24–48) Any ≥ Grade 3 Laboratory Abnormality 25% 38% 35% 34% Triglycerides (>750 mg/dL) 8% 13% 11% 9% Creatine Kinase (M: >990 U/L; F: >845 U/L) 7% 14% 12% 12% Serum Amylase (>175 U/L) 6% 7% 7% 6% Glycosuria (≥3+) 3% 3% 3% 2% AST (M: >180 U/L; F: >170 U/L) 3% 3% 4% 5% ALT (M: >215 U/L; F: >170 U/L) 2% 2% 4% 5% Serum Glucose (>250 U/L) 2% 4% 3% 3% Neutrophils (<750/mm 3) 1% 1% 2% 1% Adverse Reactions from Clinical Trials Experience in HIV-1 Infected Pediatric Subjects 2 Years and Older Assessment of adverse reactions is based on two randomized trials (Trials 352 and 321) in 184 HIV-1 infected pediatric subjects (2 years to less than 18 years of age) who received treatment with VIREAD (N=93) or placebo/active comparator (N=91) in combination with other antiretroviral agents for 48 weeks [see Clinical Studies (14.3)]. The adverse reactions observed in subjects who received treatment with VIREAD were consistent with those observed in clinical trials in adults.
In Trial 352, 89 pediatric subjects (2 years to less than 12 years of age) received VIREAD for a median exposure of 104 weeks. Of these, 4 subjects discontinued from the trial due to adverse reactions consistent with proximal renal tubulopathy. Three of these 4 subjects presented with hypophosphatemia and also had decreases in total body or spine BMD Z-score [see Warnings and Precautions (5.5)].
Changes in Bone Mineral Density: In Trial 321 (12 years to less than 18 years of age), the mean rate of BMD gain at Week 48 was less in the VIREAD group compared to the placebo group. Six VIREAD-treated subjects and one placebo-treated subject had significant (greater than 4%) lumbar spine BMD loss at Week 48. Changes from baseline BMD Z-scores were −0.341 for lumbar spine and −0.458 for total body in the 28 subjects who were treated with VIREAD for 96 weeks.
In Trial 352 (2 years to less than 12 years of age), the mean rate of BMD gain in lumbar spine at Week 48 was similar between the VIREAD and the d4T or AZT treatment groups. Total body BMD gain was less in the VIREAD group compared to the d4T or AZT treatment group. One VIREAD-treated subject and none of the d4T- or AZT-treated subjects experienced significant (greater than 4%) lumbar spine BMD loss at Week 48.
Changes from baseline in BMD Z-scores were −0.012 for lumbar spine and −0.338 for total body in the 64 subjects who were treated with VIREAD for 96 weeks. In both trials, skeletal growth (height) appeared to be unaffected for the duration of the clinical trials [see Warnings and Precautions (5.5)]. Adverse Reactions from Clinical Trials Experience in HBV-Infected Adults Clinical Trials in Adult Subjects with Chronic Hepatitis B and Compensated Liver Disease In controlled clinical trials in 641 subjects with chronic hepatitis B (0102 and 0103), more subjects treated with VIREAD during the 48-week double-blind period experienced nausea: 9% with VIREAD versus 2% with HEPSERA ®.
Other treatment-emergent adverse reactions reported in more than 5% of subjects treated with VIREAD included: abdominal pain, diarrhea, headache, dizziness, fatigue, nasopharyngitis, back pain, and skin rash. In Trials 0102 and 0103, during the open-label phase of treatment with VIREAD (weeks 48–384), 2% of subjects (13/585) experienced a confirmed increase in serum creatinine of 0.5 mg/dL from baseline.
No significant change in the tolerability profile was observed with continued treatment for up to 384 weeks. Laboratory Abnormalities: Table 10 provides a list of Grade 3–4 laboratory abnormalities through Week 48. Grades 3–4 laboratory abnormalities were similar in subjects continuing VIREAD treatment for up to 384 weeks in these trials.
Table 10 Grades 3–4 Laboratory Abnormalities Reported in ≥1% of VIREAD-Treated Subjects in Trials 0102 and 0103 (0–48 Weeks) VIREAD N=426 HEPSERA N=215 Any ≥ Grade 3 Laboratory Abnormality 19% 13% Creatine Kinase (M: >990 U/L; F: >845 U/L) 2% 3% Serum Amylase (>175 U/L) 4% 1% Glycosuria (≥3+) 3% <1% AST (M: >180 U/L; F: >170 U/L) 4% 4% ALT (M: >215 U/L; F: >170 U/L) 10% 6% The overall incidence of on-treatment ALT flares (defined as serum ALT greater than 2 × baseline and greater than 10 × ULN, with or without associated symptoms) was similar between VIREAD (2.6%) and HEPSERA (2%). ALT flares generally occurred within the first 4 to 8 weeks of treatment and were accompanied by decreases in HBV DNA levels.
No subject had evidence of decompensation. ALT flares typically resolved within 4 to 8 weeks without changes in study medication. The adverse reactions observed in subjects with chronic hepatitis B and lamivudine resistance who received treatment with VIREAD were consistent with those observed in other HBV clinical trials in adults.
Clinical Trials in Adult Subjects with Chronic Hepatitis B and Decompensated Liver Disease In Trial 0108, a small randomized, double-blind, active-controlled trial, subjects with chronic HBV and decompensated liver disease received treatment with VIREAD or other antiviral drugs for up to 48 weeks [see Clinical Studies (14.4)]. Among the 45 subjects receiving VIREAD, the most frequently reported treatment-emergent adverse reactions of any severity were abdominal pain (22%), nausea (20%), insomnia (18%), pruritus (16%), vomiting (13%), dizziness (13%), and pyrexia (11%).
Two of 45 (4%) subjects died through Week 48 of the trial due to progression of liver disease. Three of 45 (7%) subjects discontinued treatment due to an adverse event. Four of 45 (9%) subjects experienced a confirmed increase in serum creatinine of 0.5 mg/dL (1 subject also had a confirmed serum phosphorus less than 2 mg/dL through Week 48).
Three of these subjects (each of whom had a Child-Pugh score greater than or equal to 10 and MELD score greater than or equal to 14 at entry) developed renal failure. Because both VIREAD and decompensated liver disease may have an impact on renal function, the contribution of VIREAD to renal impairment in this population is difficult to ascertain.
One of 45 subjects experienced an on-treatment hepatic flare during the 48-week trial. Adverse Reactions from Clinical Trials Experience in HBV-Infected Pediatric Subjects 2 Years and Older Assessment of adverse reactions in pediatric subjects infected with chronic HBV is based on two randomized trials: Trial GS-US-174-0115 in 106 subjects (12 years to less than 18 years of age) receiving treatment with VIREAD (N=52) or placebo (N=54) for 72 weeks and Trial GS-US-174-0144 in 89 subjects (2 years to less than 12 years of age) receiving treatment with VIREAD (N=60) or placebo (N=29) for 48 weeks [see Clinical Studies (14.5)].
The adverse reactions observed in pediatric subjects who received treatment with VIREAD were consistent with those observed in clinical trials of VIREAD in adults. In Trial 115 (12 years to less than 18 years of age) and Trial 144 (2 years to less than 12 years of age), both the VIREAD and placebo treatment arms experienced an overall increase in mean lumbar spine and total body BMD over 72 and 48 weeks, respectively, as expected for a pediatric population (Table 11).
In Trial 115, the mean percentage BMD gains from baseline to Week 72 in lumbar spine and total body BMD in VIREAD-treated subjects were less than the mean percentage BMD gains observed in placebo-treated subjects (Table 11).Three subjects (6%) in the VIREAD group and two subjects (4%) in the placebo group had significant (greater than or equal to 4%) lumbar spine BMD loss at Week 72. In Trial 144 (2 years to less than 12 years of age), mean percentage BMD gains from baseline to Week 48 in lumbar spine and total body BMD in VIREAD-treated subjects were less than the mean percentage BMD gains observed in placebo-treated subjects.
At Week 48, the cumulative percentage of subjects with greater than or equal to 4% decreases in spine or whole body BMD was numerically higher for subjects in the TDF group compared with the placebo group (Table 11). As observed in pediatric studies of HIV-infected subjects, normal skeletal growth (height) was not affected for the duration of the clinical trial [see Warnings and Precautions (5.5)].
Table 11 Change in Bone Mineral Density from Baseline in Pediatric Subjects 2 Years to <12 Years of Age (Trials 115 and 144) Trial 115 (Week 72) Trial 144 (Week 48) VIREAD (N=52) Placebo (N=54) VIREAD (N=60) Placebo (N=29) Mean percentage change in BMD Lumbar spine +5% +8% +4% +8% Total body +3% +5% +5% +9% Cumulative incidence of ≥4% decrease in BMD Lumbar spine 6% 4% 18% 7% Total body 0% 2% 7% 0% Baseline BMD Z-score (mean) Lumbar spine −0.43 −0.28 +0.02 −0.29 Total body −0.20 −0.26 +0.11 −0.05 Mean change in BMD Z-score Lumbar spine -0.05 +0.07 −0.12 +0.14 Total body -0.15 +0.06 −0.18 +0.22 The effects of VIREAD-associated changes in BMD and biochemical markers on long-term bone health and future fracture risk in pediatric patients 2 years and older are unknown. The long-term effect of lower spine and total body BMD on skeletal growth in pediatric patients 2 years and older, and in particular, the effects of long-duration exposure in younger children is unknown [see Warnings and Precautions (5.5)].
6.2 Postmarketing Experience
6.2 Postmarketing Experience The following adverse reactions have been identified during postapproval use of VIREAD. Because postmarketing reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Immune System Disorders allergic reaction, including angioedema Metabolism and Nutrition Disorders lactic acidosis, hypokalemia, hypophosphatemia Respiratory, Thoracic, and Mediastinal Disorders dyspnea Gastrointestinal Disorders pancreatitis, increased amylase, abdominal pain Hepatobiliary Disorders hepatic steatosis, hepatitis, increased liver enzymes (most commonly AST, ALT gamma GT) Skin and Subcutaneous Tissue Disorders rash Musculoskeletal and Connective Tissue Disorders rhabdomyolysis, osteomalacia (manifested as bone pain and which may contribute to fractures), muscular weakness, myopathy Renal and Urinary Disorders acute renal failure, renal failure, acute tubular necrosis, Fanconi syndrome, proximal renal tubulopathy, interstitial nephritis (including acute cases), nephrogenic diabetes insipidus, renal insufficiency, increased creatinine, proteinuria, polyuria General Disorders and Administration Site Conditions asthenia The following adverse reactions, listed under the body system headings above, may occur as a consequence of proximal renal tubulopathy: rhabdomyolysis, osteomalacia, hypokalemia, muscular weakness, myopathy, hypophosphatemia.
Adverse reaction frequency tables (US label) US FDA label
| VIREAD+3TC+EFV | d4T+3TC+EFV | |
|---|---|---|
| N=299 | N=301 | |
| Rash eventRash event includes rash, pruritus, maculopapular rash, urticaria, vesiculobullous rash, and pustular rash. | 18% | 12% |
| Headache | 14% | 17% |
| Pain | 13% | 12% |
| Diarrhea | 11% | 13% |
| Depression | 11% | 10% |
| Back pain | 9% | 8% |
| Nausea | 8% | 9% |
| Fever | 8% | 7% |
| Abdominal pain | 7% | 12% |
| Asthenia | 6% | 7% |
| Anxiety | 6% | 6% |
| Vomiting | 5% | 9% |
| Insomnia | 5% | 8% |
| Arthralgia | 5% | 7% |
| Pneumonia | 5% | 5% |
| Dyspepsia | 4% | 5% |
| Dizziness | 3% | 6% |
| Myalgia | 3% | 5% |
| LipodystrophyLipodystrophy represents a variety of investigator-described adverse events not a protocol-defined syndrome. | 1% | 8% |
| Peripheral neuropathyPeripheral neuropathy includes peripheral neuritis and neuropathy. | 1% | 5% |
| VIREAD+3TC+EFV | d4T+3TC+EFV | |
|---|---|---|
| N=299 | N=301 | |
| Any ≥ Grade 3 Laboratory Abnormality | 36% | 42% |
| Fasting Cholesterol (>240 mg/dL) | 19% | 40% |
| Creatine Kinase (M: >990 U/L; F: >845 U/L) | 12% | 12% |
| Serum Amylase (>175 U/L) | 9% | 8% |
| AST (M: >180 U/L; F: >170 U/L) | 5% | 7% |
| ALT (M: >215 U/L; F: >170 U/L) | 4% | 5% |
| Hematuria (>100 RBC/HPF) | 7% | 7% |
| Neutrophils (<750/mm3) | 3% | 1% |
| Fasting Triglycerides (>750 mg/dL) | 1% | 9% |
| VIREADFrom Weeks 96 to 144 of the trial, subjects received TRUVADA® with EFV in place of VIREAD + FTC with EFV.+FTC+EFV | AZT/3TC+EFV | |
|---|---|---|
| N=257 | N=254 | |
| Fatigue | 9% | 8% |
| Depression | 9% | 7% |
| Nausea | 9% | 7% |
| Diarrhea | 9% | 5% |
| Dizziness | 8% | 7% |
| Upper respiratory tract infections | 8% | 5% |
| Sinusitis | 8% | 4% |
| Rash eventRash event includes rash, exfoliative rash, rash generalized, rash macular, rash maculopapular, rash pruritic, and rash vesicular. | 7% | 9% |
| Headache | 6% | 5% |
| Insomnia | 5% | 7% |
| Nasopharyngitis | 5% | 3% |
| Vomiting | 2% | 5% |
| VIREAD+FTC+EFVFrom Weeks 96 to 144 of the trial, subjects received TRUVADA with EFV in place of VIREAD + FTC with EFV. | AZT/3TC+EFV | |
|---|---|---|
| N=257 | N=254 | |
| Any ≥ Grade 3 Laboratory Abnormality | 30% | 26% |
| Fasting Cholesterol (>240 mg/dL) | 22% | 24% |
| Creatine Kinase (M: >990 U/L; F: >845 U/L) | 9% | 7% |
| Serum Amylase (>175 U/L) | 8% | 4% |
| Alkaline Phosphatase (>550 U/L) | 1% | 0% |
| AST (M: >180 U/L; F: >170 U/L) | 3% | 3% |
| ALT (M: >215 U/L; F: >170 U/L) | 2% | 3% |
| Hemoglobin (<8.0 mg/dL) | 0% | 4% |
| Hyperglycemia (>250 mg/dL) | 2% | 1% |
| Hematuria (>75 RBC/HPF) | 3% | 2% |
| Glycosuria (≥3+) | <1% | 1% |
| Neutrophils (<750/mm3) | 3% | 5% |
| Fasting Triglycerides (>750 mg/dL) | 4% | 2% |
| VIREAD N=368 (Week 0–24) | Placebo N=182 (Week 0–24) | VIREAD N=368 (Week 0–48) | Placebo Crossover to VIREAD N=170 (Week 24–48) | |
|---|---|---|---|---|
| Body as a Whole | ||||
| Asthenia | 7% | 6% | 11% | 1% |
| Pain | 7% | 7% | 12% | 4% |
| Headache | 5% | 5% | 8% | 2% |
| Abdominal pain | 4% | 3% | 7% | 6% |
| Back pain | 3% | 3% | 4% | 2% |
| Chest pain | 3% | 1% | 3% | 2% |
| Fever | 2% | 2% | 4% | 2% |
| Digestive System | ||||
| Diarrhea | 11% | 10% | 16% | 11% |
| Nausea | 8% | 5% | 11% | 7% |
| Vomiting | 4% | 1% | 7% | 5% |
| Anorexia | 3% | 2% | 4% | 1% |
| Dyspepsia | 3% | 2% | 4% | 2% |
| Flatulence | 3% | 1% | 4% | 1% |
| Respiratory | ||||
| Pneumonia | 2% | 0% | 3% | 2% |
| Nervous System | ||||
| Depression | 4% | 3% | 8% | 4% |
| Insomnia | 3% | 2% | 4% | 4% |
| Peripheral neuropathyPeripheral neuropathy includes peripheral neuritis and neuropathy. | 3% | 3% | 5% | 2% |
| Dizziness | 1% | 3% | 3% | 1% |
| Skin and Appendage | ||||
| Rash eventRash event includes rash, pruritus, maculopapular rash, urticaria, vesiculobullous rash, and pustular rash. | 5% | 4% | 7% | 1% |
| Sweating | 3% | 2% | 3% | 1% |
| Musculoskeletal | ||||
| Myalgia | 3% | 3% | 4% | 1% |
| Metabolic | ||||
| Weight loss | 2% | 1% | 4% | 2% |
| VIREAD N=368 (Week 0–24) | Placebo N=182 (Week 0–24) | VIREAD N=368 (Week 0–48) | Placebo Crossover to VIREAD N=170 (Week 24–48) | |
|---|---|---|---|---|
| Any ≥ Grade 3 Laboratory Abnormality | 25% | 38% | 35% | 34% |
| Triglycerides (>750 mg/dL) | 8% | 13% | 11% | 9% |
| Creatine Kinase (M: >990 U/L; F: >845 U/L) | 7% | 14% | 12% | 12% |
| Serum Amylase (>175 U/L) | 6% | 7% | 7% | 6% |
| Glycosuria (≥3+) | 3% | 3% | 3% | 2% |
| AST (M: >180 U/L; F: >170 U/L) | 3% | 3% | 4% | 5% |
| ALT (M: >215 U/L; F: >170 U/L) | 2% | 2% | 4% | 5% |
| Serum Glucose (>250 U/L) | 2% | 4% | 3% | 3% |
| Neutrophils (<750/mm3) | 1% | 1% | 2% | 1% |
| VIREAD N=426 | HEPSERA N=215 | |
|---|---|---|
| Any ≥ Grade 3 Laboratory Abnormality | 19% | 13% |
| Creatine Kinase (M: >990 U/L; F: >845 U/L) | 2% | 3% |
| Serum Amylase (>175 U/L) | 4% | 1% |
| Glycosuria (≥3+) | 3% | <1% |
| AST (M: >180 U/L; F: >170 U/L) | 4% | 4% |
| ALT (M: >215 U/L; F: >170 U/L) | 10% | 6% |
| Trial 115 (Week 72) | Trial 144 (Week 48) | |||
|---|---|---|---|---|
| VIREAD (N=52) | Placebo (N=54) | VIREAD (N=60) | Placebo (N=29) | |
| Mean percentage change in BMD | ||||
| Lumbar spine | +5% | +8% | +4% | +8% |
| Total body | +3% | +5% | +5% | +9% |
| Cumulative incidence of ≥4% decrease in BMD | ||||
| Lumbar spine | 6% | 4% | 18% | 7% |
| Total body | 0% | 2% | 7% | 0% |
| Baseline BMD Z-score (mean) | ||||
| Lumbar spine | −0.43 | −0.28 | +0.02 | −0.29 |
| Total body | −0.20 | −0.26 | +0.11 | −0.05 |
| Mean change in BMD Z-score | ||||
| Lumbar spine | -0.05 | +0.07 | −0.12 | +0.14 |
| Total body | -0.15 | +0.06 | −0.18 | +0.22 |
Pregnancy considerations
Pregnancy (US label) US FDA label
8.1 Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to VIREAD during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Available data from the APR show no increase in the overall risk of major birth defects with first trimester exposure for tenofovir disoproxil fumarate (TDF) (2.1%) compared with the background rate for major birth defects of 2.7% in a U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP) (see Data).
The rate of miscarriage for individual drugs is not reported in the APR. In the U.S. general population, the estimated background risk of miscarriage in clinically recognized pregnancies is 15–20%. Published studies in HBV-infected subjects do not report an increased risk of adverse pregnancy-related outcomes with the use of VIREAD during the third trimester of pregnancy (see Data).
In animal reproduction studies, no adverse developmental effects were observed when TDF was administered at doses/exposures ≥ 14 (TDF) and 2.7 (tenofovir) times those of the recommended daily dose of VIREAD (see Data). Data Human Data Based on prospective reports from the APR exposures to TDF-containing regimens during pregnancy resulting in live births (including 3,342 exposed in the first trimester and 1,475 exposed in the second/third trimester), there was no increase in overall major birth defects with TDF compared with the background birth defect rate of 2.7% in a U.S. reference population of the MACDP.
The prevalence of major birth defects in live births was 2.3% (95% CI: 1.8% to 2.8%) with first trimester exposure to TDF-containing regimens, and 2.1% (95% CI: 1.4% to 3.0%) with the second/third trimester exposure to TDF-containing regimens. Prospective reports from the APR of overall major birth defects in pregnancies exposed to TDF are compared with a U.S. background major birth defect rate.
Methodological limitations of the APR include the use of MACDP as the external comparator group. Limitations of using an external comparator include differences in methodology and populations, as well as confounding due to the underlying disease. In published data from three controlled clinical trials, a total of 327 pregnant women with chronic HBV infection were administered VIREAD from 28 to 32 weeks gestation through 1 to 2 months postpartum and followed for up to 12 months after delivery.
There were no new safety findings in pregnant women compared with the known safety profile of VIREAD in HBV-infected adults. An increased risk of adverse pregnancy-related outcomes was not observed; 2 stillbirths were identified, and there was 1 major birth defect (talipes) and 1 occurrence of multiple congenital abnormalities (not further specified) in VIREAD-exposed infants.
Infants were followed for up to 12 months after delivery; there were no clinically relevant drug-related safety findings in infants exposed to VIREAD during late gestation. Animal Data TDF was administered orally to pregnant rats (at 0, 50, 150, or 450 mg/kg/day) and rabbits (at 0, 30, 100, or 300 mg/kg/day) through organogenesis (on gestation days 7 through 17, and 6 through 18, respectively).
No significant toxicological effects were observed in embryo-fetal toxicity studies performed with TDF in rats at doses up to 14 times the human dose based on body surface area comparisons and in rabbits at doses up to 19 times the human dose based on body surface area comparisons. In a pre/postnatal development study in rats, TDF was administered orally through lactation at doses up to 600 mg/kg/day; no adverse effects were observed in the offspring at tenofovir exposures of approximately 2.7 times higher than human exposures at the recommended daily dose of VIREAD.
Mechanism of action
12.1 Mechanism of Action Tenofovir disoproxil fumarate is an antiviral drug [see Microbiology (12.4)].
US FDA labelPharmacokinetics
Following single dose, oral administration of VIREAD, the terminal elimination half-life of tenofovir is approximately 17 hours.
Pharmacokinetics (US label) US FDA label
12.3 Pharmacokinetics The pharmacokinetics of TDF have been evaluated in healthy volunteers and HIV-1 infected individuals. Tenofovir pharmacokinetics are similar between these populations. Absorption VIREAD is a water soluble diester prodrug of the active ingredient tenofovir. The oral bioavailability of tenofovir from VIREAD in fasted subjects is approximately 25%.
Following oral administration of a single dose of VIREAD 300 mg to HIV-1 infected subjects in the fasted state, maximum serum concentrations (C max) are achieved in 1.0 ± 0.4 hrs. C max and AUC values are 0.30 ± 0.09 µg/mL and 2.29 ± 0.69 µg ∙ hr/mL, respectively. The pharmacokinetics of tenofovir are dose proportional over a VIREAD dose range of 75 to 600 mg and are not affected by repeated dosing.
In a single-dose bioequivalence study conducted under non-fasted conditions (dose administered with 4 oz. applesauce) in healthy adult volunteers, the mean C max of tenofovir was 26% lower for the oral powder relative to the tablet formulation. Mean AUC of tenofovir was similar between the oral powder and tablet formulations.
Distribution In vitro binding of tenofovir to human plasma or serum proteins is less than 0.7 and 7.2%, respectively, over the tenofovir concentration range 0.01 to 25 µg/mL. The volume of distribution at steady-state is 1.3 ± 0.6 L/kg and 1.2 ± 0.4 L/kg, following intravenous administration of tenofovir 1.0 mg/kg and 3.0 mg/kg.
Metabolism and Elimination In vitro studies indicate that neither tenofovir disoproxil nor tenofovir are substrates of CYP enzymes. Following IV administration of tenofovir, approximately 70–80% of the dose is recovered in the urine as unchanged tenofovir within 72 hours of dosing. Following single dose, oral administration of VIREAD, the terminal elimination half-life of tenofovir is approximately 17 hours.
After multiple oral doses of VIREAD 300 mg once daily (under fed conditions), 32 ± 10% of the administered dose is recovered in urine over 24 hours. Tenofovir is eliminated by a combination of glomerular filtration and active tubular secretion. There may be competition for elimination with other compounds that are also renally eliminated.
Effects of Food on Oral Absorption Administration of VIREAD 300 mg tablets following a high-fat meal (~700 to 1,000 kcal containing 40 to 50% fat) increases the oral bioavailability, with an increase in tenofovir AUC 0–∞ of approximately 40% and an increase in C max of approximately 14%. However, administration of VIREAD with a light meal did not have a significant effect on the pharmacokinetics of tenofovir when compared to fasted administration of the drug.
Food delays the time to tenofovir C max by approximately 1 hour. C max and AUC of tenofovir are 0.33 ± 0.12 µg/mL and 3.32 ± 1.37 µg ∙ hr/mL following multiple doses of VIREAD 300 mg once daily in the fed state, when meal content was not controlled. Specific Populations Race There were insufficient numbers from racial and ethnic groups other than Caucasian to adequately determine potential pharmacokinetic differences among these populations.
Gender Tenofovir pharmacokinetics are similar in male and female subjects. Pediatric Patients 2 Years and Older: Steady-state pharmacokinetics of tenofovir were evaluated in 31 HIV-1 infected pediatric subjects 2 years to less than 18 years of age (Table 13). Tenofovir exposure achieved in these pediatric subjects receiving oral once daily doses of VIREAD 300 mg (tablet) or 8 mg/kg of body weight (powder) up to a maximum dose of 300 mg was similar to exposures achieved in adults receiving once-daily doses of VIREAD 300 mg.
Table 13 Mean (± SD) Tenofovir Pharmacokinetic Parameters by Age Groups for HIV-1 infected Pediatric Patients 2 years and older for the Tablet and Oral Powder Dose and Formulation 300 mg Tablet 8 mg/kg Oral Powder 12 Years to <18 Years (N=8) 2 Years to <12 Years (N=23) C max (µg/mL) 0.38 ± 0.13 0.24 ± 0.13 AUC tau (µg ∙ hr/mL) 3.39 ± 1.22 2.59 ± 1.06 Tenofovir exposures in HBV-infected pediatric subjects (12 years to less than 18 years of age) receiving oral once-daily doses of VIREAD 300 mg tablet and pediatric subjects 2 years to less than 12 years of age receiving VIREAD 8 mg/kg of body weight (tablet or powder) up to a maximum dose of 300 mg were comparable to exposures achieved in HIV-1 infected adult subjects receiving identical doses. Geriatric Patients Pharmacokinetic trials have not been performed in the elderly (65 years and older).
Patients with Renal Impairment The pharmacokinetics of tenofovir are altered in subjects with renal impairment [see Warnings and Precautions (5.2)]. In subjects with creatinine clearance below 50 mL/min or with end-stage renal disease (ESRD) requiring dialysis, C max, and AUC 0–∞ of tenofovir were increased (Table 14). Table 14 Pharmacokinetic Parameters (Mean ± SD) of Tenofovir 300 mg, single dose of VIREAD in Subjects with Varying Degrees of Renal Function Baseline Creatinine Clearance (mL/min) >80 N=3 50–80 N=10 30–49 N=8 12–29 N=11 C max (µg/mL) 0.34 ± 0.03 0.33 ± 0.06 0.37 ± 0.16 0.60 ± 0.19 AUC 0–∞ (µg ∙ hr/mL) 2.18 ± 0.26 3.06 ± 0.93 6.01 ± 2.50 15.98 ± 7.22 CL/F (mL/min) 1043.7 ± 115.4 807.7 ± 279.2 444.4 ± 209.8 177.0 ± 97.1 CL renal (mL/min) 243.5 ± 33.3 168.6 ± 27.5 100.6 ± 27.5 43.0 ± 31.2 Patients with Hepatic Impairment The pharmacokinetics of tenofovir following a 300 mg single dose of VIREAD have been studied in non-HIV infected subjects with moderate to severe hepatic impairment.
There were no substantial alterations in tenofovir pharmacokinetics in subjects with hepatic impairment compared with unimpaired subjects. No change in VIREAD dosing is required in patients with hepatic impairment. Assessment of Drug Interactions At concentrations substantially higher (~300-fold) than those observed in vivo, tenofovir did not inhibit in vitro drug metabolism mediated by any of the following human CYP isoforms: CYP3A4, CYP2D6, CYP2C9, or CYP2E1.
However, a small (6%) but statistically significant reduction in metabolism of CYP1A substrate was observed. Based on the results of in vitro experiments and the known elimination pathway of tenofovir, the potential for CYP-mediated interactions involving tenofovir with other medicinal products is low. VIREAD has been evaluated in healthy volunteers in combination with other antiretroviral and potential concomitant drugs.
Tables 15 and 16 summarize pharmacokinetic effects of coadministered drug on tenofovir pharmacokinetics and effects of VIREAD on the pharmacokinetics of coadministered drug. TDF is a substrate of P-glycoprotein (P-gp) and breast cancer resistance protein (BCRP) transporters. When TDF is coadministered with an inhibitor of these transporters, an increase in absorption may be observed.
No clinically significant drug interactions have been observed between VIREAD and efavirenz, methadone, nelfinavir, oral contraceptives, ribavirin, or sofosbuvir. Table 15 Drug Interactions: Changes in Pharmacokinetic Parameters for Tenofovir Subjects received VIREAD 300 mg once daily. in the Presence of the Coadministered Drug Coadministered Drug Dose of Coadministered Drug (mg) N % Change of Tenofovir Pharmacokinetic Parameters Increase = ↑; Decrease = ↓; No Effect = ⇔ (90% CI) C max AUC C min Atazanavir Reyataz Prescribing Information. 400 once daily × 14 days 33 ↑ 14 (↑ 8 to ↑ 20) ↑ 24 (↑ 21 to ↑ 28) ↑ 22 (↑ 15 to ↑ 30) Atazanavir/ Ritonavir 300/100 once daily 12 ↑ 34 (↑ 20 to ↑ 51) ↑ 37 (↑ 30 to ↑ 45) ↑ 29 (↑ 21 to ↑ 36) Darunavir/ Ritonavir Prezista Prescribing Information. 300/100 twice daily 12 ↑ 24 (↑ 8 to ↑ 42) ↑ 22 (↑ 10 to ↑ 35) ↑ 37 (↑ 19 to ↑ 57) Indinavir 800 three times daily × 7 days 13 ↑ 14 (↓ 3 to ↑ 33) ⇔ ⇔ Ledipasvir/ Sofosbuvir Data generated from simultaneous dosing with HARVONI (ledipasvir/sofosbuvir).
Staggered administration (12 hours apart) provided similar results., Comparison based on exposures when administered as atazanavir/ritonavir + FTC/TDF. 90/400 once daily × 10 days 24 ↑ 47 (↑ 37 to ↑ 58) ↑ 35 (↑ 29 to ↑ 42) ↑ 47 (↑ 38 to ↑ 57) Ledipasvir/ Sofosbuvir, Comparison based on exposures when administered as darunavir/ritonavir + FTC/TDF. 23 ↑ 64 (↑ 54 to ↑ 74) ↑ 50 (↑ 42 to ↑ 59) ↑ 59 (↑ 49 to ↑ 70) Ledipasvir/ Sofosbuvir Study conducted with ATRIPLA ® (EFV/FTC/TDF) coadministered with HARVONI; coadministration with HARVONI also results in comparable increases in tenofovir exposure when TDF is administered as COMPLERA ® (FTC/rilpivirine/TDF), or TRUVADA + dolutegravir. 90/400 once daily × 14 days 15 ↑ 79 (↑ 56 to ↑ 104) ↑ 98 (↑ 77 to ↑ 123) ↑ 163 (↑ 132 to↑ 197) Lopinavir/ Ritonavir 400/100 twice daily × 14 days 24 ⇔ ↑ 32 (↑ 25 to ↑ 38) ↑ 51 (↑ 37 to ↑ 66) Saquinavir/ Ritonavir 1000/100 twice daily × 14 days 35 ⇔ ⇔ ↑ 23 (↑ 16 to ↑ 30) Sofosbuvir Study conducted with ATRIPLA coadministered with SOVALDI ® (sofosbuvir). 400 single dose 16 ↑ 25 (↑ 8 to ↑ 45) ⇔ ⇔ Sofosbuvir/ Velpatasvir Study conducted with COMPLERA coadministered with EPCLUSA; coadministration with EPCLUSA also results in comparable increases in tenofovir exposures when TDF is administered as ATRIPLA, STRIBILD ® (elvitegravir/cobicistat/FTC/TDF), TRUVADA + atazanavir/ritonavir, or TRUVADA + darunavir/ritonavir. 400/100 once daily 24 ↑ 44 (↑ 33 to ↑ 55) ↑ 40 (↑ 34 to ↑ 46) ↑ 84 (↑ 76 to ↑ 92) Sofosbuvir/ Velpatasvir Administered as raltegravir + FTC/TDF. 400/100 once daily 30 ↑ 46 (↑ 39 to ↑ 54) ↑ 40 (↑ 34 to ↑ 45) ↑ 70 (↑ 61 to ↑ 79) Sofosbuvir/ Velpatasvir/ Voxilaprevir Comparison based on exposures when administered as darunavir + ritonavir + FTC/TDF. 400/100/100 + Voxilaprevir Study conducted with additional voxilaprevir 100 mg to achieve voxilaprevir exposures expected in HCV-infected patients. 100 once daily 29 ↑ 48 (↑ 36 to ↑ 61) ↑ 39 (↑ 32 to ↑ 46) ↑ 47 (↑ 38 to ↑ 56) Tacrolimus 0.05 mg/kg twice daily × 7 days 21 ↑ 13 (↑ 1 to ↑ 27) ⇔ ⇔ Tipranavir/ Ritonavir Aptivus Prescribing Information. 500/100 twice daily 22 ↓ 23 (↓ 32 to ↓ 13) ↓ 2 (↓ 9 to ↑ 5) ↑ 7 (↓ 2 to ↑ 17) 750/200 twice daily (23 doses) 20 ↓ 38 (↓ 46 to ↓ 29) ↑ 2 (↓ 6 to ↑ 10) ↑ 14 (↑ 1 to ↑ 27) No effect on the pharmacokinetic parameters of the following coadministered drugs was observed with VIREAD: abacavir, didanosine (buffered tablets), emtricitabine, entecavir, and lamivudine. Table 16 Drug Interactions: Changes in Pharmacokinetic Parameters for Coadministered Drug in the Presence of VIREAD Coadministered Drug Dose of Coadministered Drug (mg) N % Change of Coadministered Drug Pharmacokinetic Parameters Increase = ↑; Decrease = ↓; No Effect = ⇔; NA = Not Applicable (90% CI) C max AUC C min Abacavir 300 once 8 ↑ 12 (↓ 1 to ↑ 26) ⇔ NA Atazanavir Reyataz Prescribing Information. 400 once daily × 14 days 34 ↓ 21 (↓ 27 to ↓ 14) ↓ 25 (↓ 30 to ↓ 19) ↓ 40 (↓ 48 to ↓ 32) Atazanavir Atazanavir/ Ritonavir 300/100 once daily × 42 days 10 ↓ 28 (↓ 50 to ↑ 5) ↓ 25 In HIV-infected subjects, addition of TDF to atazanavir 300 mg plus ritonavir 100 mg, resulted in AUC and C min values of atazanavir that were 2.3- and 4-fold higher than the respective values observed for atazanavir 400 mg when given alone.
(↓ 42 to ↓ 3) ↓ 23 (↓ 46 to ↑ 10) Darunavir Prezista Prescribing Information. Darunavir/Ritonavir 300/100 once daily 12 ↑ 16 (↓ 6 to ↑ 42) ↑ 21 (↓ 5 to ↑ 54) ↑ 24 (↓ 10 to ↑ 69) Didanosine Videx EC Prescribing Information. Subjects received didanosine enteric-coated capsules. 250 once, simultaneously with VIREAD and a light meal 373 kcal, 8.2 g fat 33 ↓ 20 Compared with didanosine (enteric-coated) 400 mg administered alone under fasting conditions.
(↓ 32 to ↓ 7) ⇔ NA Emtricitabine 200 once daily × 7 days 17 ⇔ ⇔ ↑ 20 (↑ 12 to ↑ 29) Entecavir 1 mg once daily × 10 days 28 ⇔ ↑ 13 (↑ 11 to ↑ 15) ⇔ Indinavir 800 three times daily × 7 days 12 ↓ 11 (↓ 30 to ↑ 12) ⇔ ⇔ Lamivudine 150 twice daily × 7 days 15 ↓ 24 (↓ 34 to ↓ 12) ⇔ ⇔ Lopinavir Lopinavir/Ritonavir 400/100 twice daily × 14 days 24 ⇔ ⇔ ⇔ Ritonavir ⇔ ⇔ ⇔ Saquinavir Saquinavir/Ritonavir 1000/100 twice daily × 14 days 32 ↑ 22 (↑ 6 to ↑ 41) ↑ 29 Increases in AUC and C min are not expected to be clinically relevant; hence no dose adjustments are required when TDF and ritonavir-boosted saquinavir are coadministered. (↑ 12 to ↑ 48) ↑ 47 (↑ 23 to ↑ 76) Ritonavir ⇔ ⇔ ↑ 23 (↑ 3 to ↑ 46) Tacrolimus 0.05 mg/kg twice daily × 7 days 21 ⇔ ⇔ ⇔ Tipranavir Aptivus Prescribing Information.
Tipranavir/Ritonavir 500/100 twice daily 22 ↓ 17 (↓ 26 to ↓ 6) ↓ 18 (↓ 25 to ↓ 9) ↓ 21 (↓ 30 to ↓ 10) Tipranavir/Ritonavir 750/200 twice daily (23 doses) 20 ↓ 11 (↓ 16 to ↓ 4) ↓ 9 (↓ 15 to ↓ 3) ↓ 12 (↓ 22 to 0)
Formulary and pricing (Philippines)
Government price references
| Preparation | Price (PHP) | Unit | Type |
|---|---|---|---|
| Tenofovir Disoproxil Fumarate 300 mg Tablet | ₱40.00–₱43.64Reference ₱40.00 | per tablet | DPRI procurement range |
Range = lowest-highest procurement price (highest usable only in GIDA areas); reference_price = 2021 DPRI ceiling (median)
These are government procurement and reimbursement references, not retail prices. Sources:
- DOH Drug Price Reference Index (DPRI) 2021, 9th edition (as of September 17, 2021); https://caro.doh.gov.ph/wp-content/uploads/2021/09/2021DPRI-as-of-9-17-2021.pdf, as of September 17, 2021
Formulary and coverage
| Philippine National Formulary | Listed as Tenofovir disoproxil fumarate |
| PNF listing | Oral: 300 mg tablet |
| PhilHealth GAMOT | No |
Sources:
- PNF Essential Medicines List, 8th ed. (as of November 2, 2022), DOH; https://www.philhealth.gov.ph/partners/providers/pdf/PNF-EML_11022022.pdf, as of November 2, 2022
Check availability
Prices and stock vary by branch; renalcarematters.com does not sell medicines or receive payment from pharmacies.
Related guides
Guides on renalcarematters.com for this medicine, for patients and clinicians.
 GuideHIVAN: The Kidney Disease You Can Fight Back AgainstHIV-associated nephropathy (HIVAN) explained for patients and clinicians — causes, symptoms, diagnosis, ART as treatment, proteinuria management, and long-term kidney protection in PLHIV.
 GuideThe CKD Prescriber's PlaybookClinician-focused operational guide: exactly how to start, titrate, and adjust SGLT2 inhibitors, ACEi/ARB, GLP-1 agonists, diuretics, phosphate binders, and ESAs in CKD and nephrology practice. KDIGO 2024 aligned.
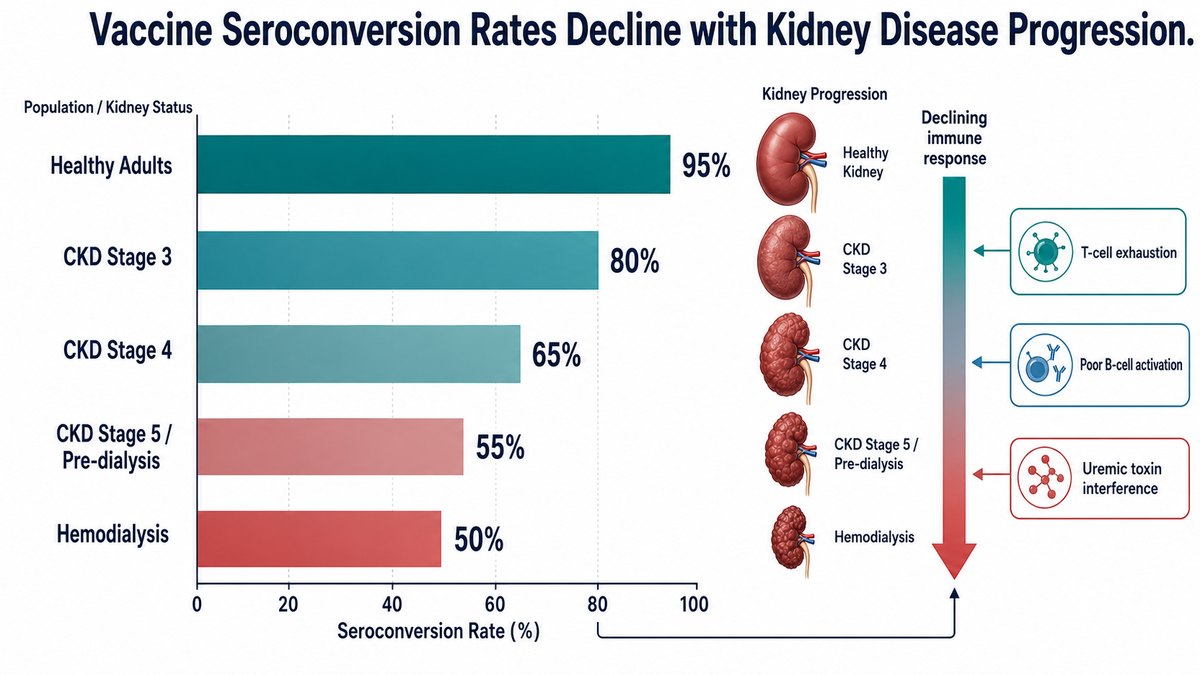 GuideViral Infections & Vaccinations in CKDViral infections and vaccinations for CKD and dialysis patients — COVID-19, hepatitis B, influenza, pneumonia vaccines, and immune protection in the Philippines.
 GuideSubstance Use & Chronic Kidney DiseaseHow tobacco, stimulants (shabu), opioids, inhalants, and misused painkillers and supplements injure the kidneys — plus a stigma-free, evidence-based recovery roadmap for Filipino patients with CKD. Patient and clinician views.
References
- U.S. Food and Drug Administration. Viread · Gilead Sciences, Inc. [US FDA-approved label, version 31, February 18, 2025]. Via DailyMed/openFDA. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=33fd6418-fbdc-42ca-a50d-ce2a476a5418
- Food and Drug Administration Philippines. Verification portal (product registrations). https://verification.fda.gov.ph
- PNF Essential Medicines List, 8th ed. (as of November 2, 2022), DOH; https://www.philhealth.gov.ph/partners/providers/pdf/PNF-EML_11022022.pdf
- DOH Drug Price Reference Index (DPRI) 2021, 9th edition (as of September 17, 2021); https://caro.doh.gov.ph/wp-content/uploads/2021/09/2021DPRI-as-of-9-17-2021.pdf
This page shows official label and registry text only; no renalcarematters.com clinical summary has been approved for it yet.
Last updated: .