WARNING: LACTIC ACIDOSIS Postmarketing cases of metformin-associated lactic acidosis have resulted in death, hypothermia, hypotension, and resistant bradyarrhythmias. The onset of metformin-associated lactic acidosis is often subtle, accompanied only by nonspecific symptoms such as malaise, myalgias, respiratory distress, somnolence, and abdominal pain.
Metformin-associated lactic acidosis was characterized by elevated blood lactate levels (>5 mmol/Liter), anion gap acidosis (without evidence of ketonuria or ketonemia), an increased lactate/pyruvate ratio; and metformin plasma levels generally >5 mcg/mL [see Warnings and Precautions (5.1)]. Risk factors for metformin-associated lactic acidosis include renal impairment, concomitant use of certain drugs (e.g., carbonic anhydrase inhibitors such as topiramate), age 65 years old or greater, having a radiological study with contrast, surgery and other procedures, hypoxic states (e.g., acute congestive heart failure), excessive alcohol intake, hepatic impairment, and mitochondrial diseases [see Warnings and Precautions (5.1)].
Steps to reduce the risk of and manage metformin-associated lactic acidosis in these high risk groups are provided in the full prescribing information [see Dosage and Administration (2.2), Contraindications (4), Warnings and Precautions (5.1), Drug Interactions (7), and Use in Specific Populations (8.6, 8.7)]. If metformin-associated lactic acidosis is suspected, immediately discontinue JENTADUETO and institute general supportive measures in a hospital setting.
Prompt hemodialysis is recommended [see Warnings and Precautions (5.1)]. WARNING: LACTIC ACIDOSIS See full prescribing information for complete boxed warning. Postmarketing cases of metformin-associated lactic acidosis have resulted in death, hypothermia, hypotension, and resistant bradyarrhythmias. Symptoms included malaise, myalgias, respiratory distress, somnolence, and abdominal pain.
Laboratory abnormalities included elevated blood lactate levels, anion gap acidosis, increased lactate/pyruvate ratio; and metformin plasma levels generally >5 mcg/mL. (5.1) Risk factors include renal impairment, concomitant use of certain drugs, age ≥65 years old, radiological studies with contrast, surgery and other procedures, hypoxic states, excessive alcohol intake, hepatic impairment, and mitochondrial diseases.
Steps to reduce the risk of and manage metformin-associated lactic acidosis in these high risk groups are provided in the Full Prescribing Information. (5.1) If lactic acidosis is suspected, discontinue JENTADUETO and institute general supportive measures in a hospital setting. Prompt hemodialysis is recommended. (5.1)
Use: Labeled indications
- JENTADUETO is indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus .
Full indications and usage US FDA label
1 INDICATIONS AND USAGE JENTADUETO is indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus. Limitations of Use JENTADUETO is not recommended in patients with type 1 diabetes mellitus. JENTADUETO has not been studied in patients with a history of pancreatitis. It is unknown whether patients with a history of pancreatitis are at an increased risk for the development of pancreatitis while using JENTADUETO [see Warnings and Precautions (5.2)].
JENTADUETO is a combination of linagliptin, a dipeptidyl peptidase-4 (DPP-4) inhibitor and metformin hydrochloride (HCl), a biguanide, indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus (1) Limitations of Use Not recommended in patients with type 1 diabetes mellitus (1) Has not been studied in patients with a history of pancreatitis (1)
Contraindications
4 CONTRAINDICATIONS JENTADUETO is contraindicated in patients with: severe renal impairment (eGFR below 30 mL/min/1.73 m²) [see Warnings and Precautions (5.1)]. acute or chronic metabolic acidosis, including diabetic ketoacidosis [see Warnings and Precautions (5.1)]. hypersensitivity to linagliptin, metformin, or any of the excipients in JENTADUETO, reactions such as anaphylaxis, angioedema, exfoliative skin conditions, urticaria, or bronchial hyperreactivity have occurred with linagliptin [see Warnings and Precautions (5.4) and Adverse Reactions (6.1)]. Severe renal impairment (eGFR below 30 mL/min/1.73 m²) (4) Metabolic acidosis, including diabetic ketoacidosis (4) Hypersensitivity to linagliptin, metformin, or any of the excipients in JENTADUETO (4)
US FDA labelDosing: Adult
- Individualize the starting dosage of JENTADUETO based on the patient's current regimen (2.1)
- The maximum recommended dosage is 2.5 mg linagliptin/1,000 mg metformin HCl twice daily (2.1)
- Take orally twice daily with meals, with gradual dosage escalation to reduce the gastrointestinal effects due to metformin (2.1)
- Prior to initiation, assess renal function with estimated glomerular filtration rate (eGFR) (2.2)
- Do not use in patients with eGFR below 30 mL/min/1.73 m² Initiation is not recommended in patients with eGFR between 30 - 45 mL/min/1.73 m² Assess risk/benefit of continuing if eGFR falls below 45 mL/min/1.73 m² Discontinue if eGFR falls below 30 mL/min/1.73 m² JENTADUETO may need to be discontinued at time of, or prior to, iodinated contrast imaging procedures (2.3)
2.1 Recommended Dosage and Administration
2.1 Recommended Dosage and Administration The dosage of JENTADUETO should be individualized on the basis of both effectiveness and tolerability, while not exceeding the maximum recommended dosage of 2.5 mg linagliptin/1,000 mg metformin hydrochloride (HCl), taken orally twice daily. JENTADUETO should be given twice daily with meals.
Dosage escalation should be gradual to reduce the gastrointestinal (GI) side effects associated with metformin use. Recommended starting dosage: In patients currently not treated with metformin HCl, initiate treatment with 2.5 mg linagliptin/500 mg metformin HCl twice daily. In patients already treated with metformin HCl, start with 2.5 mg linagliptin and the current dosage of metformin HCl taken at each of the two daily meals (e.g., a patient on metformin HCl 1,000 mg twice daily would be started on 2.5 mg linagliptin/1,000 mg metformin HCl twice daily with meals).
Patients already treated with linagliptin and metformin HCl individual components may be switched to JENTADUETO containing the same dosages of each component.
2.2 Recommended Dosing in Renal Impairment
2.2 Recommended Dosing in Renal Impairment Assess renal function prior to initiation of JENTADUETO and periodically thereafter. JENTADUETO is contraindicated in patients with an estimated glomerular filtration rate (eGFR) below 30 mL/min/1.73 m². Initiation of JENTADUETO in patients with an eGFR between 30-45 mL/min/1.73 m² is not recommended.
In patients taking JENTADUETO whose eGFR later falls below 45 mL/min/1.73 m², assess benefit/risk of continuing therapy. Discontinue JENTADUETO if the patient's eGFR later falls below 30 mL/min/1.73 m² [see Contraindications (4) and Warnings and Precautions (5.1)].
2.3 Discontinuation for Iodinated Contrast Imaging Procedures
2.3 Discontinuation for Iodinated Contrast Imaging Procedures Discontinue JENTADUETO at the time of, or prior to, an iodinated contrast imaging procedure in patients with an eGFR between 30 and 60 mL/min/1.73 m²; in patients with a history of liver disease, alcoholism or heart failure; or in patients who will be administered intra-arterial iodinated contrast. Re-evaluate eGFR 48 hours after the imaging procedure; restart JENTADUETO if renal function is stable [see Warnings and Precautions (5.1)].
Dosing: Altered kidney function
2.2 Recommended Dosing in Renal Impairment Assess renal function prior to initiation of JENTADUETO and periodically thereafter. JENTADUETO is contraindicated in patients with an estimated glomerular filtration rate (eGFR) below 30 mL/min/1.73 m². Initiation of JENTADUETO in patients with an eGFR between 30-45 mL/min/1.73 m² is not recommended.
In patients taking JENTADUETO whose eGFR later falls below 45 mL/min/1.73 m², assess benefit/risk of continuing therapy. Discontinue JENTADUETO if the patient's eGFR later falls below 30 mL/min/1.73 m² [see Contraindications (4) and Warnings and Precautions (5.1)].
8.6 Renal Impairment Metformin is substantially excreted by the kidney, and the risk of metformin accumulation and lactic acidosis increases with the degree of renal impairment. JENTADUETO is contraindicated in severe renal impairment, patients with an estimated glomerular filtration rate (eGFR) below 30 mL/min/1.73 m² [see Dosage and Administration (2.2), Contraindications (4), Warnings and Precautions (5.1), and Clinical Pharmacology (12.3)].
In the linagliptin treatment arm of the CARMELINA trial [see Clinical Studies (14.2)], 2,200 (63%) patients had renal impairment (eGFR <60 mL/min/1.73 m²). Approximately 20% of the population had eGFR ≥45 to <60 mL/min/1.73 m², 28% of the population had eGFR ≥30 to <45 mL/min/1.73 m² and 15% had eGFR <30 mL/min/1.73 m².
The overall incidence of adverse reactions were generally similar between the linagliptin and placebo treatment arms.
Renal Impairment JENTADUETO: Studies characterizing the pharmacokinetics of linagliptin and metformin after administration of JENTADUETO in renally impaired patients have not been performed. Linagliptin: Under steady-state conditions, linagliptin exposure in patients with mild renal impairment was comparable to healthy subjects.
In patients with moderate renal impairment under steady-state conditions, mean exposure of linagliptin increased (AUC 𝜏,ss by 71% and C max by 46%) compared with healthy subjects. This increase was not associated with a prolonged accumulation half-life, terminal half-life, or an increased accumulation factor. Renal excretion of linagliptin was below 5% of the administered dose and was not affected by decreased renal function.
Kidney-specific guidance from renalcarematters.com: in preparation.
Dosing: Hepatic impairment
8.7 Hepatic Impairment Use of metformin in patients with hepatic impairment has been associated with some cases of lactic acidosis. JENTADUETO is not recommended in patients with hepatic impairment [see Warnings and Precautions (5.1)].
US FDA labelDosing: Pediatric
Pediatric use (US label) US FDA label
8.4 Pediatric Use Safety and effectiveness of JENTADUETO have not been established in pediatric patients. Effectiveness of linagliptin was not demonstrated in a 26-week randomized, double-blind, placebo-controlled trial (NCT03429543) in 157 pediatric patients aged 10 to 17 years with inadequately controlled type 2 diabetes mellitus.
Dosing: Older adult
Geriatric use (US label) US FDA label
8.5 Geriatric Use Linagliptin is minimally excreted by the kidney; however, metformin is substantially excreted by the kidney [see Warnings and Precautions (5.1) and Clinical Pharmacology (12.3)]. Linagliptin In linagliptin studies, 1,085 linagliptin-treated patients were 65 years of age and older and 131 patients were 75 years of age and older.
In these linagliptin studies, no overall differences in safety or effectiveness of linagliptin were observed between geriatric patients and younger adult patients. Metformin Controlled clinical studies of metformin did not include sufficient numbers of elderly patients to determine whether they respond differently from younger patients.
In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy and the higher risk of lactic acidosis. Assess renal function more frequently in elderly patients [see Contraindications (4), Warnings and Precautions (5.1), and Clinical Pharmacology (12.3)].
Administration
2.1 Recommended Dosage and Administration The dosage of JENTADUETO should be individualized on the basis of both effectiveness and tolerability, while not exceeding the maximum recommended dosage of 2.5 mg linagliptin/1,000 mg metformin hydrochloride (HCl), taken orally twice daily. JENTADUETO should be given twice daily with meals. Dosage escalation should be gradual to reduce the gastrointestinal (GI) side effects associated with metformin use. Recommended starting dosage: In patients currently not treated with metformin HCl, initiate treatment with 2.5 mg linagliptin/500 mg metformin HCl twice daily. In patients already treated with metformin HCl, start with 2.5 mg linagliptin and the current dosage of metformin HCl taken at each of the two daily meals (e.g., a patient on metformin HCl 1,000 mg twice daily would be started on 2.5 mg linagliptin/1,000 mg metformin HCl twice daily with meals). Patients already treated with linagliptin and metformin HCl individual components may be switched to JENTADUETO containing the same dosages of each component.
US FDA labelDosage forms
Philippines
- Film-coated tablet: 2.5 mg + 1 g, 2.5 mg + 500 mg, 2.5 mg/1 g, 2.5 mg/500 mg, 2.5 mg/850 mg
- Tablet: 2.5 mg/1 g, 2.5 mg/500 mg
- Film-caoted tablet: 2.5 mg/500 mg
Registered products in the Philippines
31 products registered with the Food and Drug Administration (FDA) Philippines list Linagliptin + Metformin as the generic name (including products registered under a variant spelling). Registration status changes; confirm a product's current status on the FDA portal before relying on it.
Also registered under: Linagliptin +Metformin HC1 (2 products) · Linagliptin + Metformin Hydrocholoride (1 product). Products registered under these spellings are included in the table and marked.
All registered products31
| Package insert | |||||||
|---|---|---|---|---|---|---|---|
2.5 mg/1 g TabletAlu/Alu Blister Pack x 10's (Box of 30's & 100's) 's (Box of 30's & 100's) | Rx | Hebei Tiancheng Pharmaceutical Co., Ltd.China | AMB HK Enterprises Inc. | DRP-16977 | Sep 3, 2030 | ||
2.5 mg/500 mg TabletAlu/Alu Blister Pack x 10's (Box of 30's & 100's) | Rx | Hebei Tiancheng Pharmaceutical Co., Ltd.China | AMB HK Enterprises Inc. | DRP-16980 | Sep 3, 2030 | ||
Glucox-Duo 1000Linagliptin + Metformin Hydrochloride | 2.5 mg/1 g Film-Coated TabletAlu/White PVC/PVdC Blister Pack x 10’s (Box of 30’s) | RxVAT-exempt | Lloyd Laboratories, Inc.Philippines | Trader: Euro-Health Care Exponents, Inc. | DRP-19019 | Oct 19, 2031 | |
Glucox-Duo 500Linagliptin + Metformin Hydrochloride | 2.5 mg/500 mg Film-Coated TabletAlu/White PVC/PVdC Blister Pack x 10’s (Box of 30’s) | RxVAT-exempt | Lloyd Laboratories, Inc.Philippines | Trader: Euro-Health Care Exponents, Inc. | DRP-19018 | Oct 19, 2031 | |
Glypta MetLinagliptin + Metformin HCl | 2.5 mg/500 mg Film-Coated TabletAlu-PVC/PVdC Blister Pack X 10's (Box of 30's) | RxVAT-exempt | Lloyd Laboratories Inc.Philippines | Trader: Aldril Pharmaceuticals, Inc. | DRP-18289 | Jun 4, 2031 | |
ILIATA MAXLinagliptin + Metformin Hydrochloride | 2.5 mg/500 mg Film-Coated TabletAlu/Alu Blister Pack x 10’s (Box of 30’s) | RxVAT-exempt | Baroque Pharmaceuticals Private LimitedIndia | Helande Kidney Care Inc.Importer: AMB HK ENTERPRISES INC. | DRP-16005-01 | Oct 11, 2029 | |
Linaglide MLinagliptin + Metformin Hcl | 2.5 mg + 1 g Film-Coated TabletAlu-PVC/PVdC Blister Pack x 10's (Box of 30's) | RxVAT-exempt | Lloyd Laboratories Inc.Philippines | Trader: Innogen Pharmaceuticals, Inc. | DRP-18287 | Jun 4, 2032 | |
Linaglide MLinagliptin + Metformin HCl | 2.5 mg + 500 mg Film-Coated TabletAlu-PVC/PVdC Blister Pack x 10's (Box of 30's) | RxVAT-exempt | Lloyd Laboratories Inc.Philippines | Trader: Innogen Pharmaceuticals, Inc. | DRP-18288 | Jun 4, 2032 | |
Linax Plus 2.5/1000Linagliptin + Metformin Hydrochloride | 2.5 mg/1 g Film-Coated TabletAlu/Alu Blister Pack x 10's (Box of 30's, 50's & 100's) | RxVAT-exempt | Azarias Pharmaceutical Laboratories Inc.Philippines | — | DRP-18306 | Jun 9, 2031 | |
LinazoneLinagliptin + Metformin hydrochloride | 2.5 mg/1 g Film-Coated TabletAlu/Alu Blister Pack x 10's (Box of 30's) | RxVAT-exempt | Exemed PharmaceuticalsIndia | AMB HK Enterprises Inc. | DRP-17318 | Nov 14, 2030 | |
LinazoneLinagliptin + Metformin Hydrochloride | 2.5 mg/500 mg Film-Caoted TabletAlu/Alu Blister Pack X 10'S (Box of 30's) | RxVAT-exempt | Base Medico Private LimitedIndia | AMB HK Enterprises, Inc. | DRP-18485 | Jul 21, 2031 | |
LinazoneLinagliptin + Metformin hydrochloride | 2.5 mg/500 mg Film-Coated TabletAlu/Alu Blister Pack x 10's (Box of 30's) | RxVAT-exempt | Exemed PharmaceuticalsIndia | AMB HK Enterprises Inc. | DRP-17317 | Nov 14, 2030 | |
LinazoneLinagliptin + Metformin Hydrochloride | 2.5mg/1g Film-Coated TabletAlu/Alu Blister Pack X 10'S (Box of 30's) | RxVAT-exempt | Base Medico Private LimitedIndia | AMB HK Enterprises, Inc. | DRP-18487 | Jul 21, 2031 | |
LinazoneLinagliptin + Metformin Hydrochloride | 2.5mg/850mg Film-Coated TabletAlu/Alu Blister Pack X 10'S (Box of 30's) | RxVAT-exempt | Base Medico Private LimitedIndia | AMB HK Enterprises, Inc. | DRP-18486 | Jul 21, 2031 | |
LinazoneLinagliptin + Metformin Hydrochloride | 2.5mg/850mg Film-Coated TabletAlu/Alu Blister Pack x 10's (Box of 30's) | RxVAT-exempt | Exemed PharmaceuticalsIndia | AMB HK Enterprises, Inc. | DRP-18490 | Jul 21, 2031 | |
Lincreta-MLinagliptin + Metformin Hydrochloride | 2.5 mg/1 g Film-Coated TabletAlu/Alu Blister Pack x 10’s (Box of 30’s) | RxVAT-exempt | Baroque Pharmaceuticals Pvt. Ltd.India | Emcure Pharma Philippines Inc.Importer: AMB HK Enterprises Inc. | DRP-16003-01 | Oct 11, 2029 | |
Lincreta-MLinagliptin + Metformin Hydrochloride | 2.5 mg/500 mg Film-Coated TabletAlu/Alu Blister Pack x 10’s (Box of 30’s) | RxVAT-exempt | Baroque Pharmaceuticals Pvt. Ltd.India | Emcure Pharma Philippines Inc.Importer: AMB HK Enterprises Inc. | DRP-16005-02 | Oct 11, 2029 | |
Linglu-M 2.5/1000Linagliptin + Metformin hydrochloride | 2.5 mg/1 g Film Coated TabletAlu/Opaque White PVC Blister Pack x 10's (Box of 30's) | RxVAT-exempt | Hetero Labs Limited (Unit V)India | Camber Pharmaceuticals Inc. | DRP-17597 | Mar 5, 2031 | |
2.5 mg/ 500 mg Film-Coated TabletAlu/Alu Blister Pack x 10's (Box of 30's) | Rx | Baroque Pharmaceuticals Private LimitedIndia | Multicare Pharmaceuticals Phils. Inc.Importer: AMB HK Enterprises, Inc. | DRP-16005-03 | Oct 11, 2029 | ||
MetgliptLinagliptin + Metformin Hydrochloride | 2.5 mg/500 mg Film-Coated TabletAlu/Alu Blister Pack x 10's (Box of 30's) | RxVAT-exempt | Baroque Pharmaceuticals Private LimitedIndia | AMB HK Enterprises Inc. | DRP-16005 | Oct 11, 2029 | |
Metglipt ForteLinagliptin + Metformin Hydrochloride | 2.5 mg/1 g Film Coated TabletAlu/Alu Blister Pack x 10's (Box of 30's) | RxVAT-exempt | Baroque Pharmaceuticals Private LimitedIndia | AMB HK Enterprises Inc. | DRP-16003 | Oct 11, 2029 | |
Metglipt PlusLinagliptin + Metformin Hydrochloride | 2.5 mg/850 mg Film-Coated TabletAlu/Alu Blister Pack x 10's (Box of 30's) | RxVAT-exempt | Baroque Pharmaceuticals Private LimitedIndia | AMB HK Enterprises Inc. | DRP-16004 | Oct 11, 2029 | |
MetlinaLinagliptin + Metformin hydrochloride (in extended- release form) | 2.5mg/1g Film Coated TabletAlu/Alu Blister Pack x 10's (Box of 100's) | RxVAT-exempt | Windlas Biotech Limited (Plant 2)India | Synergia Health Care & Life Sciences, Inc. | DRP-17941 | Apr 14, 2031 | |
Myglip Plus 2.5/1000Linagliptin + Metformin Hydrochloride | 2.5 mg/1 g Film-Coated TabletAlu/Alu Blister Pack x 10's (Box of 3 blister packs x 10 tablets; Box of 1 blister pack x 10 tablets as physician sample) | RxVAT-exempt | Alidac Healthcare (Myanmar) Ltd.Myanmar | Zydus Healthcare Philippines, Inc.Trader: Cadila Healthcare Limited | DRP-14842 | Jan 23, 2029 | |
Myglip Plus 2.5/500Linagliptin + Metformin Hydrochloride | 2.5 mg/ 500 mg Film-Coated TabletAlu/Alu Blister Pack x 10's (Box of 3 blister packs x 10 tablets; Box of 1 blister pack x 10 tablets as physician. sample) | RxVAT-exempt | Alidac Healthcare (Myanmar) Ltd.Myanmar | Zydus Healthcare Philippines, Inc.Trader: Cadila Healthcare Limited | DRP-14840 | Jan 23, 2029 | |
Myglip Plus 2.5/850Linagliptin + Metformin Hydrochloride | 2.5 mg/ 850 mg Film-Coated TabletAlu/Alu Blister Pack x 10's (Box of 3 blister packs x 10 tablets; Box of 1 blister pack x 10 tablets as physician. sample) | RxVAT-exempt | Alidac Healthcare (Myanmar) Ltd.Myanmar | Zydus Healthcare Philippines, Inc.Trader: Cadila Healthcare Limited | DRP-14841 | Jan 23, 2029 | |
SuganilLinagliptin + Metformin Hydrochloride | 2.5 mg/1 g Film-Coated TabletAlu/White PVC/PVdC Blister Pack x 10’s (Box of 30’s) | RxVAT-exempt | Lloyd Laboratories, Inc.Philippines | Trader: Euro-Health Care Exponents, Inc. | DRP-19017 | Oct 19, 2031 | |
Trajenta DuoLinagliptin + Metformin Hydrochloride | 2.5 mg/1 g Film-Coated TabletAlu/PV/PCTFE Blister Pack x 10's Box of 30's | RxVAT-exempt | Boehringer Inghelheim Pharma GmbH & Co. KGGermany | Importer: Boehringer Ingelheim (Philippines), Inc. | DR-XY42182 | Jun 28, 2028 | |
Trajenta DuoLinagliptin + Metformin Hydrochloride | 2.5 mg/500 mg Film-Coated TabletAlu/PV/PCTFE Blister Pack x 10's (Box of 30 Tablets) | RxVAT-exempt | Boehringer Ingelheim Pharma GmbH & Co. KGGermany | Importer: Boehringer Ingelheim (Philippines), Inc. | DR-XY42181 | Jun 28, 2028 | |
Trajenta DuoLinagliptin + Metformin Hydrochloride | 2.5 mg/850 mg Film-Coated TabletAlu/PV/PCTFE Blister Pack x 10's (Box of 30 tablets) | RxVAT-exempt | Boehringer Ingelheim Pharma GmbH & Co. KGGermany | Boehrigner Ingelheim (Philippines), Inc. | DR-XY42180 | Jun 28, 2028 | |
(no brand name)Linagliptin + Metformin hydrochloride | 2.5 mg/500 mg Film-Coated TabletAlu/White PVC-PVdC Blister Pack x 10's (Box of 30's) | RxVAT-exempt | Lloyd Laboratories, Inc.Philippines | — | DRP-18254 | Jun 3, 2031 |
Source: FDA Philippines product registration database. "Valid until" is the registration validity date listed by the FDA; a past date may mean a renewal is pending. Package insert links point to files published by the FDA.
United States (label)
Dosage forms and strengths (US label) US FDA label
3 DOSAGE FORMS AND STRENGTHS JENTADUETO tablets are a combination of linagliptin and metformin HCl available as: 2.5 mg linagliptin/500 mg metformin HCl tablets are light yellow, oval, biconvex tablets debossed with "D2/500" on one side and the Boehringer Ingelheim symbol on the other side 2.5 mg linagliptin/850 mg metformin HCl tablets are light orange, oval, biconvex tablets debossed with "D2/850" on one side and the Boehringer Ingelheim symbol on the other side 2.5 mg linagliptin/1,000 mg metformin HCl tablets are light pink, oval, biconvex tablets debossed with "D2/1000" on one side and the Boehringer Ingelheim symbol on the other side Tablets: 2.5 mg linagliptin/500 mg metformin HCl (3) 2.5 mg linagliptin/850 mg metformin HCl (3) 2.5 mg linagliptin/1,000 mg metformin HCl (3)
Warnings/Precautions
The boxed warning is shown at the top of this page.
- Lactic Acidosis: See boxed warning (5.1)
- Pancreatitis: There have been reports of acute pancreatitis, including fatal pancreatitis. If pancreatitis is suspected, promptly discontinue JENTADUETO. (5.2)
- Hypoglycemia: Consider lowering the dosage of insulin secretagogue or insulin to reduce the risk of hypoglycemia when initiating JENTADUETO (5.3)
- Hypersensitivity Reactions: Serious hypersensitivity reactions (e.g., anaphylaxis, angioedema, and exfoliative skin conditions) have occurred with JENTADUETO. If hypersensitivity reactions occur discontinue JENTADUETO, treat promptly, and monitor until signs and symptoms resolve. (5.4)
- Vitamin B12 Deficiency: Metformin may lower vitamin B12 levels. Measure hematologic parameters annually and vitamin B12 at 2 to 3 year intervals and manage any abnormalities. (5.5)
- Arthralgia: Severe and disabling arthralgia has been reported in patients taking linagliptin. Consider as a possible cause for severe joint pain and discontinue drug if appropriate. (5.6)
- Bullous Pemphigoid: There have been reports of bullous pemphigoid requiring hospitalization. Tell patients to report development of blisters or erosions. If bullous pemphigoid is suspected, discontinue JENTADUETO. (5.7)
- Heart Failure: Heart failure has been observed with two other members of the DPP-4 inhibitor class. Consider risks and benefits of JENTADUETO in patients who …
5.1 Lactic Acidosis
5.1 Lactic Acidosis Metformin There have been postmarketing cases of metformin-associated lactic acidosis, including fatal cases. These cases had a subtle onset and were accompanied by nonspecific symptoms such as malaise, myalgias, abdominal pain, respiratory distress, or increased somnolence; however, hypothermia, hypotension and resistant bradyarrhythmias have occurred with severe acidosis.
Metformin-associated lactic acidosis was characterized by elevated blood lactate concentrations (>5 mmol/Liter), anion gap acidosis (without evidence of ketonuria or ketonemia), and an increased lactate/pyruvate ratio; metformin plasma levels generally >5 mcg/mL. Metformin decreases liver uptake of lactate increasing lactate blood levels which may increase risk of lactic acidosis, especially in patients at risk.
If metformin-associated lactic acidosis is suspected, general supportive measures should be instituted promptly in a hospital setting, along with immediate discontinuation of JENTADUETO. In JENTADUETO-treated patients with a diagnosis or strong suspicion of lactic acidosis, prompt hemodialysis is recommended to correct the acidosis and remove accumulated metformin (metformin is dialyzable, with clearance of up to 170 mL/min under good hemodynamic conditions).
Hemodialysis has often resulted in reversal of symptoms and recovery. Educate patients and their families about the symptoms of lactic acidosis and if these symptoms occur instruct them to discontinue JENTADUETO and report these symptoms to their healthcare provider. For each of the known and possible risk factors for metformin-associated lactic acidosis, recommendations to reduce the risk of and manage metformin-associated lactic acidosis are provided below: Renal Impairment: The postmarketing metformin-associated lactic acidosis cases primarily occurred in patients with significant renal impairment.
The risk of metformin accumulation and metformin-associated lactic acidosis increases with the severity of renal impairment because metformin is substantially excreted by the kidney. Clinical recommendations based upon the patient's renal function include [see Dosage and Administration (2.2) and Clinical Pharmacology (12.3)]: Before initiating JENTADUETO, obtain an estimated glomerular filtration rate (eGFR).
JENTADUETO is contraindicated in patients with an eGFR less than 30 mL/min/1.73 m² [see Contraindications (4)]. Initiation of JENTADUETO is not recommended in patients with eGFR between 30 – 45 mL/min/1.73 m². Obtain an eGFR at least annually in all patients taking JENTADUETO. In patients at increased risk for the development of renal impairment (e.g., the elderly), renal function should be assessed more frequently.
In patients taking JENTADUETO whose eGFR later falls below 45 mL/min/1.73 m², assess the benefit and risk of continuing therapy. Drug Interactions: The concomitant use of JENTADUETO with specific drugs may increase the risk of metformin-associated lactic acidosis: those that impair renal function, result in significant hemodynamic change, interfere with acid-base balance or increase metformin accumulation [see Drug Interactions (7)].
Therefore, consider more frequent monitoring of patients. Age 65 or Greater: The risk of metformin-associated lactic acidosis increases with the patient's age because elderly patients have a greater likelihood of having hepatic, renal, or cardiac impairment than younger patients. Assess renal function more frequently in elderly patients [see Use in Specific Populations (8.5)].
Radiological Studies with Contrast: Administration of intravascular iodinated contrast agents in metformin-treated patients has led to an acute decrease in renal function and the occurrence of lactic acidosis. Stop JENTADUETO at the time of, or prior to, an iodinated contrast imaging procedure in patients with an eGFR between 30 and 60 mL/min/1.73 m²; in patients with a history of hepatic impairment, alcoholism, or heart failure; or in patients who will be administered intra-arterial iodinated contrast.
Re-evaluate eGFR 48 hours after the imaging procedure, and restart JENTADUETO if renal function is stable. Surgery and Other Procedures: Withholding of food and fluids during surgical or other procedures may increase the risk for volume depletion, hypotension and renal impairment. JENTADUETO should be temporarily discontinued while patients have restricted food and fluid intake.
Hypoxic States: Several of the postmarketing cases of metformin-associated lactic acidosis occurred in the setting of acute congestive heart failure (particularly when accompanied by hypoperfusion and hypoxemia). Cardiovascular collapse (shock), acute myocardial infarction, sepsis, and other conditions associated with hypoxemia have been associated with lactic acidosis and may also cause prerenal azotemia.
When such events occur, discontinue JENTADUETO. Excessive Alcohol Intake: Alcohol potentiates the effect of metformin on lactate metabolism and this may increase the risk of metformin-associated lactic acidosis. Warn patients against excessive alcohol intake while receiving JENTADUETO. Hepatic Impairment: Patients with hepatic impairment have developed cases of metformin-associated lactic acidosis.
This may be due to impaired lactate clearance resulting in higher lactate blood levels. Therefore, avoid use of JENTADUETO in patients with clinical or laboratory evidence of hepatic disease. Mitochondrial Diseases: Metformin may increase the risk of lactic acidosis in patients with mitochondrial diseases such as mitochondrial encephalomyopathy with lactic acidosis, and stroke-like episodes (MELAS) syndrome and maternally inherited diabetes and deafness (MIDD).
JENTADUETO is not recommended in patients with mitochondrial diseases such as MELAS syndrome and MIDD. If a patient taking JENTADUETO develops elevated lactic acid levels (with or without accompanying neurologic signs and symptoms), discontinue JENTADUETO. Depending on the clinical context, consider evaluating the patient for MELAS, MIDD, or other mitochondrial disease.
5.2 Pancreatitis
5.2 Pancreatitis Acute pancreatitis, including fatal pancreatitis, has been reported in patients treated with linagliptin. In the CARMELINA trial [see Clinical Studies (14.2)], acute pancreatitis was reported in 9 (0.3%) patients treated with linagliptin and in 5 (0.1%) patients treated with placebo. Two patients treated with linagliptin in the CARMELINA trial had acute pancreatitis with a fatal outcome.
There have been postmarketing reports of acute pancreatitis, including fatal pancreatitis, in patients treated with linagliptin. Take careful notice of potential signs and symptoms of pancreatitis. If pancreatitis is suspected, promptly discontinue JENTADUETO and initiate appropriate management. It is unknown whether patients with a history of pancreatitis are at increased risk for the development of pancreatitis while using JENTADUETO.
5.3 Hypoglycemia with Concomitant Use with Insulin
5.3 Hypoglycemia with Concomitant Use with Insulin and Insulin Secretagogues Insulin secretagogues and insulin are known to cause hypoglycemia. The risk of hypoglycemia is increased when JENTADUETO is used in combination with an insulin secretagogue (e.g., sulfonylurea) or insulin [see Adverse Reactions (6.1)]. Therefore, a lower dosage of the insulin secretagogue or insulin may be required to reduce the risk of hypoglycemia when used in combination with JENTADUETO.
5.4 Hypersensitivity Reactions
5.4 Hypersensitivity Reactions There have been postmarketing reports of serious hypersensitivity reactions in patients treated with linagliptin. These reactions include anaphylaxis, angioedema, and exfoliative skin conditions. Onset of these reactions occurred predominantly within the first 3 months after initiation of treatment with linagliptin, with some reports occurring after the first dose.
If a serious hypersensitivity reaction is suspected, discontinue JENTADUETO, assess for other potential causes for the event, and institute alternative treatment for diabetes mellitus. Angioedema has also been reported with other dipeptidyl peptidase-4 (DPP-4) inhibitors. Use caution in a patient with a history of angioedema to another DPP-4 inhibitor because it is unknown whether such patients will be predisposed to angioedema with JENTADUETO.
5.5 Vitamin B12 Deficiency
5.5 Vitamin B12 Deficiency In metformin clinical trials of 29-week duration, a decrease to subnormal levels of previously normal serum vitamin B12 levels was observed in approximately 7% of metformin-treated patients. Such decrease, possibly due to interference with B12 absorption from the B12 -intrinsic factor complex, may be associated with anemia but appears to be rapidly reversible with discontinuation of metformin or vitamin B12 supplementation.
Certain individuals (those with inadequate vitamin B12 or calcium intake or absorption) appear to be predisposed to developing subnormal vitamin B12 levels. Measure hematologic parameters on an annual basis and vitamin B12 at 2 to 3 year intervals in patients on JENTADUETO and manage any abnormalities [see Adverse Reactions (6.1)].
5.6 Severe and Disabling Arthralgia
5.6 Severe and Disabling Arthralgia There have been postmarketing reports of severe and disabling arthralgia in patients taking linagliptin. The time to onset of symptoms following initiation of drug therapy varied from one day to years. Patients experienced relief of symptoms upon discontinuation of the medication. A subset of patients experienced a recurrence of symptoms when restarting the same drug or a different DPP-4 inhibitor.
Consider DPP-4 inhibitors as a possible cause for severe joint pain and discontinue drug if appropriate.
5.7 Bullous Pemphigoid
5.7 Bullous Pemphigoid Bullous pemphigoid was reported in 7 (0.2%) patients treated with linagliptin compared to none in patients treated with placebo in the CARMELINA trial [see Clinical Studies (14.2)], and 3 of these patients were hospitalized due to bullous pemphigoid. Postmarketing cases of bullous pemphigoid requiring hospitalization have been reported with DPP-4 inhibitor use.
In reported cases, patients typically recovered with topical or systemic immunosuppressive treatment and discontinuation of the DPP-4 inhibitor. Tell patients to report development of blisters or erosions while receiving JENTADUETO. If bullous pemphigoid is suspected, JENTADUETO should be discontinued and referral to a dermatologist should be considered for diagnosis and appropriate treatment.
5.8 Heart Failure
5.8 Heart Failure An association between DPP-4 inhibitor treatment and heart failure has been observed in cardiovascular outcomes trials for two other members of the DPP-4 inhibitor class. These trials evaluated patients with type 2 diabetes mellitus and atherosclerotic cardiovascular disease. Consider the risks and benefits of JENTADUETO prior to initiating treatment in patients at risk for heart failure, such as those with a prior history of heart failure and a history of renal impairment, and observe these patients for signs and symptoms of heart failure during therapy.
Advise patients of the characteristic symptoms of heart failure and to immediately report such symptoms. If heart failure develops, evaluate and manage according to current standards of care and consider discontinuation of JENTADUETO.
Drug interactions
Drug interactions (US label) US FDA label
7 DRUG INTERACTIONS Table 2 describes clinically relevant interactions with JENTADUETO. Table 2 Clinically Relevant Interactions with JENTADUETO Carbonic Anhydrase Inhibitors Clinical Impact Topiramate or other carbonic anhydrase inhibitors (e.g., zonisamide, acetazolamide or dichlorphenamide) frequently cause a decrease in serum bicarbonate and induce non-anion gap, hyperchloremic metabolic acidosis.
Concomitant use of these drugs with JENTADUETO may increase the risk of lactic acidosis. Intervention Consider more frequent monitoring of these patients. Drugs that Reduce Metformin Clearance Clinical Impact Concomitant use of drugs that interfere with common renal tubular transport systems involved in the renal elimination of metformin (e.g., organic cationic transporter-2 [OCT2] / multidrug and toxin extrusion [MATE] inhibitors such as ranolazine, vandetanib, dolutegravir, and cimetidine) could increase systemic exposure to metformin and may increase the risk for lactic acidosis [see Clinical Pharmacology (12.3)].
Intervention Consider the benefits and risks of concomitant use. Alcohol Clinical Impact Alcohol is known to potentiate the effect of metformin on lactate metabolism. Intervention Warn patients against excessive alcohol intake while receiving JENTADUETO. Insulin or Insulin Secretagogues Clinical Impact The risk of hypoglycemia is increased when JENTADUETO is used in combination with an insulin secretagogue (e.g., sulfonylurea) or insulin.
Intervention Coadministration of JENTADUETO with an insulin secretagogue (e.g., sulfonylurea) or insulin may require lower dosages of the insulin secretagogue or insulin to reduce the risk of hypoglycemia. Drugs Affecting Glycemic Control Clinical Impact Certain drugs tend to produce hyperglycemia and may lead to loss of glycemic control.
These drugs include the thiazides and other diuretics, corticosteroids, phenothiazines, thyroid products, estrogens, oral contraceptives, phenytoin, nicotinic acid, sympathomimetics, calcium channel blocking drugs, and isoniazid. Intervention When such drugs are administered to a patient receiving JENTADUETO, the patient should be closely observed to maintain adequate glycemic control.
When such drugs are withdrawn from a patient receiving JENTADUETO, the patient should be observed closely for hypoglycemia. Inducers of P-glycoprotein or CYP3A4 Enzymes Clinical Impact Rifampin decreased linagliptin exposure, suggesting that the efficacy of linagliptin may be reduced when administered in combination with a strong P-gp or CYP3A4 inducer.
Intervention Use of alternative treatments is strongly recommended when linagliptin is to be administered with a strong P-gp or CYP3A4 inducer. Carbonic Anhydrase Inhibitors: May increase risk of lactic acidosis. Consider more frequent monitoring. (7) Drugs that Reduce Metformin Clearance: May increase risk of lactic acidosis.
Consider benefits and risks of concomitant use. (7) Alcohol: Can potentiate the effect of metformin on lactate metabolism. Warn patients against excessive alcohol intake. (7) Strong P-glycoprotein/CYP3A4 Inducer: Efficacy may be reduced when administered in combination (e.g., rifampin). Use of alternative treatments is strongly recommended.
(7)
Metabolism and transporters (CYP, P-gp, OATP; US label) US FDA label
Linagliptin In vitro Assessment of Drug Interactions Linagliptin is a weak to moderate inhibitor of CYP isozyme CYP3A4, but does not inhibit other CYP isozymes and is not an inducer of CYP isozymes, including CYP1A2, 2A6, 2B6, 2C8, 2C9, 2C19, 2D6, 2E1, and 4A11.
Linagliptin is a P-glycoprotein (P-gp) substrate, and inhibits P-gp mediated transport of digoxin at high concentrations.
Based on these results and in vivo drug interaction studies, linagliptin is considered unlikely to cause interactions with other P-gp substrates at therapeutic concentrations.
In vivo Assessment of Drug Interactions Strong inducers of CYP3A4 or P-gp (e.g., rifampin) decrease exposure to linagliptin to subtherapeutic and likely ineffective concentrations [see Drug Interactions (7) ] .
In vivo studies indicated evidence of a low propensity for causing drug interactions with substrates of CYP3A4, CYP2C9, CYP2C8, P-gp, and organic cationic transporter (OCT).
Drugs that Reduce Metformin Clearance Clinical Impact Concomitant use of drugs that interfere with common renal tubular transport systems involved in the renal elimination of metformin (e.g., organic cationic transporter-2 [OCT2] / multidrug and toxin extrusion [MATE] inhibitors such as ranolazine, vandetanib, dolutegravir, and cimetidine) could increase systemic exposure to metformin and may increase the risk for lactic acidosis [see Clinical Pharmacology (12.3) ] .
Inducers of P-glycoprotein or CYP3A4 Enzymes Clinical Impact Rifampin decreased linagliptin exposure, suggesting that the efficacy of linagliptin may be reduced when administered in combination with a strong P-gp or CYP3A4 inducer.
Intervention Use of alternative treatments is strongly recommended when linagliptin is to be administered with a strong P-gp or CYP3A4 inducer.
Adverse reactions
- The following serious adverse reactions are described below or elsewhere in the prescribing information: Lactic Acidosis [see Warnings and Precautions (5.1)] Pancreatitis [see Warnings and Precautions (5.2)] Hypoglycemia with Concomitant Use with Insulin and Insulin Secretagogues [see Warnings and Precautions (5.3)] Hypersensitivity Reactions [see Warnings and Precautions (5.4)] Vitamin B12 Deficiency [see Warnings and Precautions (5.5)] Severe and Disabling Arthralgia [see Warnings and Precautions (5.6)] Bullous Pemphigoid [see Warnings and Precautions (5.7)] Heart Failure [see Warnings and Precautions (5.8)] Most common adverse reactions (incidence ≥5% and more often than placebo) were nasopharyngitis and diarrhea (6.1)
- To report SUSPECTED ADVERSE REACTIONS, contact Boehringer Ingelheim Pharmaceuticals, Inc. at 1-800-542-6257 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1 Clinical Trials Experience
6.1 Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Linagliptin/Metformin The safety of concomitantly administered linagliptin (daily dosage 5 mg) and metformin (mean daily dosage of approximately 1,800 mg) has been evaluated in 2,816 patients with type 2 diabetes mellitus treated for ≥12 weeks in clinical trials.
Three placebo-controlled trials with linagliptin + metformin were conducted: 2 studies were 24 weeks in duration, 1 trial was 12 weeks in duration. In the 3 placebo-controlled clinical studies, adverse reactions which occurred in ≥5% of patients receiving linagliptin + metformin (n=875) and were more common than in patients given placebo + metformin (n=539) included nasopharyngitis (5.7% vs 4.3%).
In a 24-week factorial design trial, adverse reactions reported in ≥5% of patients receiving linagliptin + metformin and were more common than in patients given placebo are shown in Table 1. Table 1 Adverse Reactions Reported in ≥5% of Patients Treated with Linagliptin + Metformin and Greater than with Placebo in a 24-week Factorial-Design Trial Adverse Reactions Placebo (%) n=72 Linagliptin Monotherapy (%) n=142 Metformin Monotherapy (%) n=291 Combination of Linagliptin with Metformin (%) n=286 Nasopharyngitis 1.4 5.6 2.7
6.3 Diarrhea 2
6.3 Diarrhea 2.8 3.5 3.8
6.3 Other
6.3 Other adverse reactions reported in clinical studies with treatment of linagliptin + metformin were hypersensitivity (e.g., urticaria, angioedema, or bronchial hyperreactivity), cough, decreased appetite, nausea, vomiting, pruritus, and pancreatitis. Linagliptin Adverse reactions reported in ≥2% of patients treated with linagliptin 5 mg and more commonly than in patients treated with placebo included: nasopharyngitis (7.0% vs 6.1%), diarrhea (3.3% vs 3.0%), and cough (2.1% vs 1.4%).
Rates for other adverse reactions for linagliptin 5 mg vs placebo when linagliptin was used in combination with specific antidiabetic agents were: urinary tract infection (3.1% vs 0%) and hypertriglyceridemia (2.4% vs 0%) when linagliptin was used as add-on to sulfonylurea; hyperlipidemia (2.7% vs 0.8%) and weight increased (2.3% vs 0.8%) when linagliptin was used as add-on to pioglitazone; and constipation (2.1% vs 1%) when linagliptin was used as add-on to basal insulin therapy. Other adverse reactions reported in clinical studies with treatment of linagliptin monotherapy were hypersensitivity (e.g., urticaria, angioedema, localized skin exfoliation, or bronchial hyperreactivity) and myalgia.
In the clinical trial program, pancreatitis was reported in 15.2 cases per 10,000 patient year exposure while being treated with linagliptin compared with 3.7 cases per 10,000 patient year exposure while being treated with comparator (placebo and active comparator, sulfonylurea). Three additional cases of pancreatitis were reported following the last administered dose of linagliptin.
Metformin The most common (>5%) adverse reactions due to initiation of metformin therapy are diarrhea, nausea/vomiting, flatulence, abdominal discomfort, indigestion, asthenia, and headache. Other Adverse Reactions Hypoglycemia Linagliptin/Metformin In a 24-week factorial design trial, hypoglycemia was reported in 4 (1.4%) of 286 subjects treated with linagliptin + metformin, 6 (2.1%) of 291 subjects treated with metformin, and 1 (1.4%) of 72 subjects treated with placebo.
The incidence of hypoglycemia with plasma glucose <54 mg/dL was 8.1% in the linagliptin group (N=792) compared to 5.3% in the placebo group (N=263) when administered in combination with metformin and sulfonylurea in a 24-week trial. Linagliptin The incidence of severe hypoglycemia (requiring assistance) was 1.7% in the linagliptin group (N=631) compared to 1.1% in the placebo group (N=630) when administered in combination with basal insulin in a 52-week trial.
Laboratory Test Abnormalities in Clinical Trials of Linagliptin or Metformin Linagliptin Increase in Uric Acid: Changes in laboratory values that occurred more frequently in the linagliptin group and ≥1% more than in the placebo group were increases in uric acid (1.3% in the placebo group, 2.7% in the linagliptin group). Increase in Lipase: In a placebo-controlled clinical trial with linagliptin in type 2 diabetes mellitus patients with micro- or macroalbuminuria, a mean increase of 30% in lipase concentrations from baseline to 24 weeks was observed in the linagliptin arm compared to a mean decrease of 2% in the placebo arm.
Lipase levels above 3 times upper limit of normal were seen in 8.2% compared to 1.7% patients in the linagliptin and placebo arms, respectively. Increase in Amylase: In a cardiovascular safety trial comparing linagliptin versus glimepiride in patients with type 2 diabetes mellitus, amylase levels above 3 times upper limit of normal were seen in 1.0% compared to 0.5% of patients in the linagliptin and glimepiride arms, respectively.
The clinical significance of elevations in lipase and amylase with linagliptin is unknown in the absence of potential signs and symptoms of pancreatitis [see Warnings and Precautions (5.2)]. Metformin Decrease in Vitamin B12: In metformin clinical trials of 29-week duration, a decrease to subnormal levels of previously normal serum vitamin B12 levels was observed in approximately 7% of patients.
6.2 Postmarketing Experience
6.2 Postmarketing Experience The following adverse reactions have been identified during postapproval use. Because these reactions are reported voluntarily from a population of uncertain size, it is generally not possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Linagliptin Gastrointestinal Disorders: Acute pancreatitis, including fatal pancreatitis [see Indications and Usage (1)], mouth ulceration, stomatitis Immune System Disorders: Hypersensitivity reactions including anaphylaxis, angioedema, and exfoliative skin conditions Musculoskeletal and Connective Tissue Disorders: Rhabdomyolysis, severe and disabling arthralgia Skin and Subcutaneous Tissue Disorders: Bullous pemphigoid, rash Metformin Hepatobiliary Disorders: Cholestatic, hepatocellular, and mixed hepatocellular liver injury
Adverse reaction frequency tables (US label) US FDA label
| Adverse Reactions | Placebo (%) n=72 | Linagliptin Monotherapy (%) n=142 | Metformin Monotherapy (%) n=291 | Combination of Linagliptin with Metformin (%) n=286 |
|---|---|---|---|---|
| Nasopharyngitis | 1.4 | 5.6 | 2.7 | 6.3 |
| Diarrhea | 2.8 | 3.5 | 3.8 | 6.3 |
Pregnancy considerations
Pregnancy (US label) US FDA label
8.1 Pregnancy Risk Summary The limited data with JENTADUETO and linagliptin use in pregnant women are not sufficient to inform a JENTADUETO-associated or linagliptin-associated risk for major birth defects and miscarriage. Published studies with metformin use during pregnancy have not reported a clear association with metformin and major birth defect or miscarriage risk [see Data].
There are risks to the mother and fetus associated with poorly controlled diabetes in pregnancy [see Clinical Considerations]. In animal reproduction studies, no adverse developmental effects were observed when the combination of linagliptin and metformin was administered to pregnant rats during the period of organogenesis at doses similar to the maximum recommended clinical dose, based on exposure [see Data].
The estimated background risk of major birth defects is 6% to 10% in women with pre-gestational diabetes with a HbA1c >7 and has been reported to be as high as 20% to 25% in women with HbA1c >10. The estimated background risk of miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, preeclampsia, spontaneous abortions, preterm delivery, and delivery complications. Poorly controlled diabetes increases the fetal risk for major birth defects, stillbirth, and macrosomia related morbidity.
Data Human Data Published data from postmarketing studies have not reported a clear association with metformin and major birth defects, miscarriage, or adverse maternal or fetal outcomes when metformin was used during pregnancy. However, these studies cannot definitely establish the absence of any metformin-associated risk because of methodological limitations, including small sample size and inconsistent comparator groups.
Animal Data Linagliptin and metformin, the components of JENTADUETO, were coadministered to pregnant Wistar Han rats during the period of organogenesis. No adverse developmental outcome was observed at doses similar to the maximum recommended clinical dose, based on exposure. At higher doses associated with maternal toxicity, the metformin component of the combination was associated with an increased incidence of fetal rib and scapula malformations at ≥9-times a 2,000 mg clinical dose, based on exposure.
Linagliptin No adverse developmental outcome was observed when linagliptin was administered to pregnant Wistar Han rats and Himalayan rabbits during the period of organogenesis at doses up to 240 mg/kg/day and 150 mg/kg/day, respectively. These doses represent approximately 943-times (rats) and 1,943-times (rabbits) the 5 mg maximum clinical dose, based on exposure.
No adverse functional, behavioral, or reproductive outcome was observed in offspring following administration of linagliptin to Wistar Han rats from gestation day 6 to lactation day 21 at a dose 49-times the maximum recommended human dose, based on exposure. Linagliptin crosses the placenta into the fetus following oral dosing in pregnant rats and rabbits.
Metformin HCl Metformin HCl did not cause adverse developmental effects when administered to pregnant Sprague Dawley rats and rabbits at doses up to 600 mg/kg/day during the period of organogenesis. This represents an exposure of approximately 2- and 6-times a clinical dose of 2,000 mg, based on body surface area (mg/m 2) for rats and rabbits, respectively.
Mechanism of action
12.1 Mechanism of Action JENTADUETO JENTADUETO contains: linagliptin, a dipeptidyl peptidase-4 (DPP-4) inhibitor, and metformin, a biguanide. Linagliptin Linagliptin is an inhibitor of DPP-4, an enzyme that degrades the incretin hormones glucagon-like peptide-1 (GLP-1) and glucose-dependent insulinotropic polypeptide (GIP).
Thus, linagliptin increases the concentrations of active incretin hormones, stimulating the release of insulin in a glucose-dependent manner and decreasing the levels of glucagon in the circulation. Both incretin hormones are involved in the physiological regulation of glucose homeostasis. Incretin hormones are secreted at a low basal level throughout the day and levels rise immediately after meal intake.
GLP-1 and GIP increase insulin biosynthesis and secretion from pancreatic beta cells in the presence of normal and elevated blood glucose levels. Furthermore, GLP-1 also reduces glucagon secretion from pancreatic alpha cells, resulting in a reduction in hepatic glucose output. Metformin HCl Metformin is an antihyperglycemic agent which improves glucose tolerance in patients with type 2 diabetes mellitus, lowering both basal and postprandial plasma glucose.
Metformin decreases hepatic glucose production, decreases intestinal absorption of glucose, and improves insulin sensitivity by increasing peripheral glucose uptake and utilization. With metformin therapy, insulin secretion remains unchanged while fasting insulin levels and day-long plasma insulin response may decrease.
US FDA labelPharmacodynamics
Pharmacodynamics (US label) US FDA label
12.2 Pharmacodynamics Linagliptin Linagliptin binds to DPP-4 in a reversible manner and increases the concentrations of incretin hormones. Linagliptin glucose-dependently increases insulin secretion and lowers glucagon secretion, thus resulting in a better regulation of the glucose homeostasis. Linagliptin binds selectively to DPP-4 and selectively inhibits DPP-4, but not DPP-8 or DPP-9 activity in vitro at concentrations approximating therapeutic exposures.
Cardiac Electrophysiology In a randomized, placebo-controlled, active-comparator, 4-way crossover study, 36 healthy subjects were administered a single oral dose of linagliptin 5 mg, linagliptin 100 mg (20 times the recommended dose), moxifloxacin, and placebo. No increase in QTc was observed with either the recommended dose of 5 mg or the 100 mg dose.
At the 100 mg dose, peak linagliptin plasma concentrations were approximately 38-fold higher than the peak concentrations following a 5 mg dose.
Pharmacokinetics
Following oral administration, plasma concentrations of linagliptin decline in at least a biphasic manner with a long terminal half-life (>100 hours), related to the saturable binding of linagliptin to DPP-4.
The effective half-life for accumulation of linagliptin, as determined from oral administration of multiple doses of linagliptin 5 mg, is approximately 12 hours.
Elimination Linagliptin: Linagliptin has a terminal half-life of about 200 hours at steady-state, though the accumulation half-life is about 11 hours.
Renal clearance at steady-state was approximately 70 mL/min.
Metformin HCl: Metformin has a plasma elimination half-life of approximately 6.2 hours.
Pharmacokinetics (US label) US FDA label
12.3 Pharmacokinetics JENTADUETO Administration of linagliptin 2.5 mg/metformin HCl 1,000 mg fixed-dose combination with food resulted in no change in overall exposure of linagliptin. There was no change in metformin AUC; however, mean peak serum concentration of metformin was decreased by 18% when administered with food.
A delayed time-to-peak serum concentrations by 2 hours was observed for metformin under fed conditions. These changes are not likely to be clinically significant. Absorption Linagliptin The absolute bioavailability of linagliptin is approximately 30%. Following oral administration, plasma concentrations of linagliptin decline in at least a biphasic manner with a long terminal half-life (>100 hours), related to the saturable binding of linagliptin to DPP-4.
However, the prolonged elimination does not contribute to the accumulation of the drug. The effective half-life for accumulation of linagliptin, as determined from oral administration of multiple doses of linagliptin 5 mg, is approximately 12 hours. After once-daily dosing, steady-state plasma concentrations of linagliptin 5 mg are reached by the third dose, and C max and AUC increased by a factor of 1.3 at steady-state compared with the first dose.
Plasma AUC of linagliptin increased in a less than dose-proportional manner in the dose range of 1 to 10 mg. The pharmacokinetics of linagliptin is similar in healthy subjects and in patients with type 2 diabetes mellitus. Metformin HCl The absolute bioavailability of a metformin HCl 500 mg tablet given under fasting conditions is approximately 50% to 60%.
Studies using single oral doses of metformin tablets 500 mg to 1,500 mg, and 850 mg to 2,550 mg, indicate that there is a lack of dose proportionality with increasing doses, which is due to decreased absorption rather than an alteration in elimination. Distribution Linagliptin The mean apparent volume of distribution at steady-state following a single intravenous dose of linagliptin 5 mg to healthy subjects is approximately 1,110 L, indicating that linagliptin extensively distributes to the tissues.
Plasma protein binding of linagliptin is concentration-dependent decreasing from about 99% at 1 nmol/L to 75% to 89% at ≥30 nmol/L, reflecting saturation of binding to DPP-4 with increasing concentration of linagliptin. At high concentrations, where DPP-4 is fully saturated, 70% to 80% of linagliptin remains bound to plasma proteins and 20% to 30% is unbound in plasma.
Plasma binding is not altered in patients with renal or hepatic impairment. Metformin HCl The apparent volume of distribution (V/F) of metformin following single oral doses of immediate-release metformin HCl tablets 850 mg averaged 654±358 L. Metformin is negligibly bound to plasma proteins. Metformin partitions into erythrocytes, most likely as a function of time.
Elimination Linagliptin: Linagliptin has a terminal half-life of about 200 hours at steady-state, though the accumulation half-life is about 11 hours. Renal clearance at steady-state was approximately 70 mL/min. Metformin HCl: Metformin has a plasma elimination half-life of approximately 6.2 hours. In blood, the elimination half-life is approximately 17.6 hours, suggesting that the erythrocyte mass may be a compartment of distribution.
Metabolism Linagliptin: Following oral administration, the majority (about 90%) of linagliptin is excreted unchanged, indicating that metabolism represents a minor elimination pathway. A small fraction of absorbed linagliptin is metabolized to a pharmacologically inactive metabolite, which shows a steady-state exposure of 13.3% relative to linagliptin.
Metformin HCl: Intravenous single-dose studies in normal subjects demonstrate that metformin does not undergo hepatic metabolism (no metabolites have been identified in humans), nor biliary excretion. Excretion Linagliptin: Following administration of an oral [14 C] linagliptin dose to healthy subjects, approximately 85% of the administered radioactivity was eliminated via the enterohepatic system (80%) or urine (5%) within 4 days of dosing.
Metformin HCl: Following oral administration, approximately 90% of the absorbed drug is excreted via the renal route within the first 24 hours. Renal clearance is approximately 3.5 times greater than creatinine clearance, which indicates that tubular secretion is the major route of metformin elimination. Specific Populations Renal Impairment JENTADUETO: Studies characterizing the pharmacokinetics of linagliptin and metformin after administration of JENTADUETO in renally impaired patients have not been performed.
Linagliptin: Under steady-state conditions, linagliptin exposure in patients with mild renal impairment was comparable to healthy subjects. In patients with moderate renal impairment under steady-state conditions, mean exposure of linagliptin increased (AUC 𝜏,ss by 71% and C max by 46%) compared with healthy subjects. This increase was not associated with a prolonged accumulation half-life, terminal half-life, or an increased accumulation factor.
Renal excretion of linagliptin was below 5% of the administered dose and was not affected by decreased renal function. Patients with type 2 diabetes mellitus and severe renal impairment showed steady-state exposure approximately 40% higher than that of patients with type 2 diabetes mellitus and normal renal function (increase in AUC by 42% and C max by 35%).
For both type 2 diabetes mellitus groups, renal excretion was below 7% of the administered dose. These findings were further supported by the results of population pharmacokinetic analyses. Metformin HCl: In patients with decreased renal function, the plasma and blood half-life of metformin is prolonged and the renal clearance is decreased [see Contraindications (4) and Warnings and Precautions (5.1)].
Hepatic Impairment JENTADUETO: Studies characterizing the pharmacokinetics of linagliptin and metformin after administration of JENTADUETO in hepatically impaired patients have not been performed [see Warnings and Precautions (5.1)]. Linagliptin: In patients with mild hepatic impairment (Child-Pugh class A) steady-state exposure (AUC τ,ss) of linagliptin was approximately 25% lower and C max,ss was approximately 36% lower than in healthy subjects.
In patients with moderate hepatic impairment (Child-Pugh class B), AUC ss of linagliptin was about 14% lower and C max,ss was approximately 8% lower than in healthy subjects. Patients with severe hepatic impairment (Child-Pugh class C) had comparable exposure of linagliptin in terms of AUC 0-24 and approximately 23% lower C max compared with healthy subjects.
Reductions in the pharmacokinetic parameters seen in patients with hepatic impairment did not result in reductions in DPP-4 inhibition. Metformin HCl: No pharmacokinetic studies of metformin have been conducted in patients with hepatic impairment. Effects of Age, Body Mass Index (BMI), Gender, and Race Linagliptin: Based on the population pharmacokinetic analysis, age, BMI, gender, and race do not have a clinically meaningful effect on pharmacokinetics of linagliptin [see Use in Specific Populations (8.5)].
Metformin HCl: Metformin pharmacokinetic parameters did not differ significantly between normal subjects and patients with type 2 diabetes mellitus when analyzed according to gender. Similarly, in controlled clinical studies in patients with type 2 diabetes mellitus, the antihyperglycemic effect of metformin was comparable in males and females.
Limited data from controlled pharmacokinetic studies of metformin in healthy elderly subjects suggest that total plasma clearance of metformin is decreased, the half-life is prolonged, and C max is increased, compared with healthy young subjects. From these data, it appears that the change in metformin pharmacokinetics with aging is primarily accounted for by a change in renal function.
No studies of metformin pharmacokinetic parameters according to race have been performed. In controlled clinical studies of metformin HCl in patients with type 2 diabetes mellitus, the antihyperglycemic effect was comparable in Caucasians (n=249), Blacks (n=51), and Hispanics (n=24). Drug Interactions Pharmacokinetic drug interaction studies with JENTADUETO have not been performed; however, such studies have been conducted with the individual components of JENTADUETO (linagliptin and metformin HCl).
Linagliptin In vitro Assessment of Drug Interactions Linagliptin is a weak to moderate inhibitor of CYP isozyme CYP3A4, but does not inhibit other CYP isozymes and is not an inducer of CYP isozymes, including CYP1A2, 2A6, 2B6, 2C8, 2C9, 2C19, 2D6, 2E1, and 4A11. Linagliptin is a P-glycoprotein (P-gp) substrate, and inhibits P-gp mediated transport of digoxin at high concentrations.
Based on these results and in vivo drug interaction studies, linagliptin is considered unlikely to cause interactions with other P-gp substrates at therapeutic concentrations. In vivo Assessment of Drug Interactions Strong inducers of CYP3A4 or P-gp (e.g., rifampin) decrease exposure to linagliptin to subtherapeutic and likely ineffective concentrations [see Drug Interactions (7)].
In vivo studies indicated evidence of a low propensity for causing drug interactions with substrates of CYP3A4, CYP2C9, CYP2C8, P-gp, and organic cationic transporter (OCT). Table 3 describes the effect of coadministered drugs on systemic exposure of linagliptin. Table 3 Effect of Coadministered Drugs on Systemic Exposure of Linagliptin Coadministered Drug Dosing of Coadministered Drug* Dosing of Linagliptin* Geometric Mean Ratio (ratio with/without coadministered drug) No effect=1.0 AUC † C max *Multiple dose (steady-state) unless otherwise noted **For information regarding clinical recommendations [see Drug Interactions (7)]. # Single dose †AUC = AUC(0 to 24 hours) for single-dose treatments and AUC = AUC(TAU) for multiple-dose treatments QD=once daily BID=twice daily TID=three times daily Metformin 850 mg TID 10 mg QD 1.20 1.03 Glyburide 1.75 mg # 5 mg QD 1.02 1.01 Pioglitazone 45 mg QD 10 mg QD 1.13 1.07 Ritonavir 200 mg BID 5 mg # 2.01 2.96 Rifampin** 600 mg QD 5 mg QD 0.60 0.56 Table 4 describes the effect of linagliptin on systemic exposure of coadministered drugs.
Table 4 Effect of Linagliptin on Systemic Exposure of Coadministered Drugs Coadministered Drug Dosing of Coadministered Drug* Dosing of Linagliptin* Geometric Mean Ratio (ratio with/without coadministered drug) No effect=1.0 AUC † C max *Multiple dose (steady-state) unless otherwise noted # Single dose †AUC = AUC(INF) for single-dose treatments and AUC = AUC(TAU) for multiple-dose treatments **AUC=AUC(0-168) and C max =E max for pharmacodynamic end points INR=International Normalized Ratio PT=Prothrombin Time QD=once daily TID=three times daily Metformin 850 mg TID 10 mg QD metformin 1.01 0.89 Glyburide 1.75 mg # 5 mg QD glyburide 0.86 0.86 Pioglitazone 45 mg QD 10 mg QD pioglitazone 0.94 0.86 metabolite M-III 0.98 0.96 metabolite M-IV 1.04 1.05 Digoxin 0.25 mg QD 5 mg QD digoxin 1.02 0.94 Simvastatin 40 mg QD 10 mg QD simvastatin 1.34 1.10 simvastatin acid 1.33 1.21 Warfarin 10 mg # 5 mg QD R-warfarin 0.99 1.00 S-warfarin 1.03 1.01 INR 0.93** 1.04** PT 1.03** 1.15** Ethinylestradiol and levonorgestrel ethinylestradiol 0.03 mg and levonorgestrel 0.150 mg QD 5 mg QD ethinylestradiol 1.01 1.08 levonorgestrel 1.09 1.13 Metformin HCl Table 5 describes the effect of coadministered drugs on plasma metformin systemic exposure. Table 5 Effect of Coadministered Drugs on Plasma Metformin Systemic Exposure Coadministered Drug Dosing of Coadministered Drug* Dosing of Metformin* Geometric Mean Ratio (ratio with/without coadministered drug) No effect=1.0 AUC † C max *All metformin and coadministered drugs were given as single doses †AUC=AUC(INF) ‡Ratio of arithmetic means **At steady-state with topiramate 100 mg every 12 hours and metformin 500 mg every 12 hours; AUC = AUC(0-12 hours) Glyburide 5 mg 850 mg metformin 0.91‡ 0.93‡ Furosemide 40 mg 850 mg metformin 1.09‡ 1.22‡ Nifedipine 10 mg 850 mg metformin 1.16 1.21 Propranolol 40 mg 850 mg metformin 0.90 0.94 Ibuprofen 400 mg 850 mg metformin 1.05‡ 1.07‡ Cationic drugs eliminated by renal tubular secretion may reduce metformin elimination [see Drug Interactions (7)].
Cimetidine 400 mg 850 mg metformin 1.40 1.61 Carbonic anhydrase inhibitors may cause metabolic acidosis [see Drug Interactions (7)]. Topiramate** 100 mg 500 mg metformin 1.25 1.17 Table 6 describes the effect of metformin on coadministered drug systemic exposure. Table 6 Effect of Metformin on Coadministered Drug Systemic Exposure Coadministered Drug Dosing of Coadministered Drug* Dosing of Metformin* Geometric Mean Ratio (ratio with/without metformin) No effect=1.0 AUC † C max *All metformin and coadministered drugs were given as single doses †AUC=AUC(INF) unless otherwise noted ‡Ratio of arithmetic means, p-value of difference <0.05 §AUC(0-24 hours) reported ¶Ratio of arithmetic means Glyburide 5 mg 850 mg glyburide 0.78‡ 0.63‡ Furosemide 40 mg 850 mg furosemide 0.87‡ 0.69‡ Nifedipine 10 mg 850 mg nifedipine 1.10§ 1.08 Propranolol 40 mg 850 mg propranolol 1.01§ 1.02 Ibuprofen 400 mg 850 mg ibuprofen 0.97¶ 1.01¶ Cimetidine 400 mg 850 mg cimetidine 0.95§ 1.01
Formulary and pricing (Philippines)
Check availability
Prices and stock vary by branch; renalcarematters.com does not sell medicines or receive payment from pharmacies.
Related guides & calculators
Guides and calculators on renalcarematters.com for this medicine, for patients and clinicians.
 GuideThe CKD Prescriber's PlaybookClinician-focused operational guide: exactly how to start, titrate, and adjust SGLT2 inhibitors, ACEi/ARB, GLP-1 agonists, diuretics, phosphate binders, and ESAs in CKD and nephrology practice. KDIGO 2024 aligned.
 GuideEating Smart with Diabetes — A Filipino Food GuideEvidence-based diabetic diet guide for Filipinos — glycemic index of rice, Filipino food GI chart, meal sequencing, 7-day meal plan, and palengke-friendly strategies for blood sugar control.
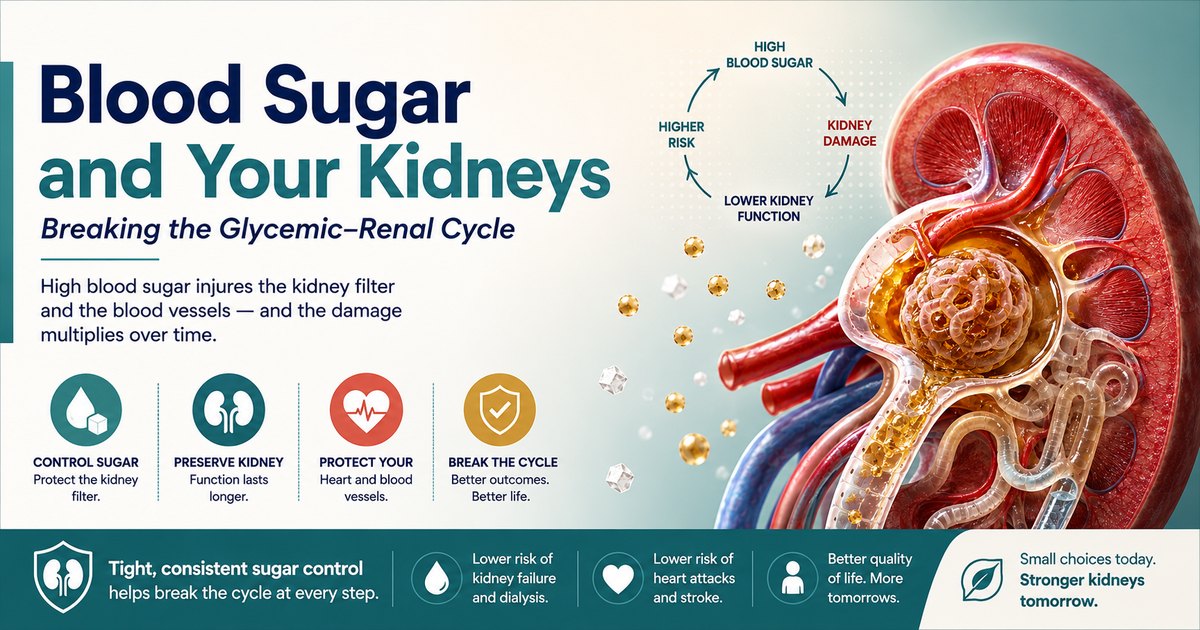 GuideBlood Sugar and Your Kidneys: Breaking the Glycemic-Renal CycleA dual-mode (patient + clinician) guide to glycemic management across the CKD spectrum. Why high sugar is 'syrup in the filter', your individualized HbA1c target, Filipino food and movement, and the SGLT2i/GLP-1RA medicines that protect sug
- CalculatorMetformin Safety Checker in CKD (eGFR hold/continue)eGFR-based metformin hold, continue, or discontinue guidance in CKD per the 2023 ADA Standards of Care and the FDA label, with dose-capping advice, transient-hold triggers (contrast, acute illness, surgery), monitoring, and references.
References
- U.S. Food and Drug Administration. Jentadueto · Boehringer Ingelheim Pharmaceuticals, Inc. [US FDA-approved label, version 46, August 19, 2026]. Via DailyMed/openFDA. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=f6dd9b86-0d18-95d4-2bc7-05591bfdd597
- Food and Drug Administration Philippines. Verification portal (product registrations). https://verification.fda.gov.ph
This page shows official label and registry text only; no renalcarematters.com clinical summary has been approved for it yet.
Last updated: .