WARNING: FETAL TOXICITY When pregnancy is detected, discontinue Diovan HCT as soon as possible. (5.1) Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus. (5.1) WARNING: FETAL TOXICITY See full prescribing information for complete boxed warning. When pregnancy is detected, discontinue Diovan HCT as soon as possible. (5.1) Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus. (5.1)
Use: Labeled indications
- Diovan HCT (valsartan and hydrochlorothiazide, USP) is indicated for the treatment of hypertension, to lower blood pressure.
- As initial therapy in patients likely to need multiple drugs to achieve their blood pressure goals
Full indications and usage US FDA label
1 INDICATIONS AND USAGE Diovan HCT (valsartan and hydrochlorothiazide, USP) is indicated for the treatment of hypertension, to lower blood pressure. Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular events, primarily strokes and myocardial infarctions. These benefits have been seen in controlled trials of antihypertensive drugs from a wide variety of pharmacologic classes, including hydrochlorothiazide and the angiotensin II receptor blocker (ARB) class to which valsartan principally belongs.
There are no controlled trials demonstrating risk reduction with Diovan HCT. Control of high blood pressure should be part of comprehensive cardiovascular risk management, including, as appropriate, lipid control, diabetes management, antithrombotic therapy, smoking cessation, exercise, and limited sodium intake. Many patients will require more than 1 drug to achieve blood pressure goals.
For specific advice on goals and management, see published guidelines, such as those of the National High Blood Pressure Education Program’s Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure (JNC). Numerous antihypertensive drugs, from a variety of pharmacologic classes and with different mechanisms of action, have been shown in randomized controlled trials to reduce cardiovascular morbidity and mortality, and it can be concluded that it is blood pressure reduction, and not some other pharmacologic property of the drugs, that is largely responsible for those benefits.
The largest and most consistent cardiovascular outcome benefit has been a reduction in the risk of stroke, but reductions in myocardial infarction and cardiovascular mortality have also been seen regularly. Elevated systolic or diastolic pressure causes increased cardiovascular risk, and the absolute risk increase per mmHg is greater at higher blood pressures, so that even modest reductions of severe hypertension can provide substantial benefit.
Relative risk reduction from blood pressure reduction is similar across populations with varying absolute risk, so the absolute benefit is greater in patients who are at higher risk independent of their hypertension (e.g., patients with diabetes or hyperlipidemia), and such patients would be expected to benefit from more aggressive treatment to a lower blood pressure goal. Some antihypertensive drugs have smaller blood pressure effects (as monotherapy) in black patients, and many antihypertensive drugs have additional approved indications and effects (e.g., on angina, heart failure, or diabetic kidney disease).
These considerations may guide selection of therapy. Add-On Therapy Diovan HCT may be used in patients whose blood pressure is not adequately controlled on monotherapy. Replacement Therapy Diovan HCT may be substituted for the titrated components. Initial Therapy Diovan HCT may be used as initial therapy in patients who are likely to need multiple drugs to achieve blood pressure goals.
The choice of Diovan HCT as initial therapy for hypertension should be based on an assessment of potential benefits and risks. Patients with stage 2 hypertension are at a relatively high risk for cardiovascular events (such as strokes, heart attacks, and heart failure), kidney failure, and vision problems, so prompt treatment is clinically relevant.
The decision to use a combination as initial therapy should be individualized and should be shaped by considerations such as baseline blood pressure, the target goal, and the incremental likelihood of achieving goal with a combination compared to monotherapy. Individual blood pressure goals may vary based upon the patient’s risk.
Data from the high dose multifactorial trial [see Clinical Studies (14.1)] provides estimates of the probability of reaching a target blood pressure with Diovan HCT compared to valsartan or hydrochlorothiazide monotherapy. The figures below provide estimates of the likelihood of achieving systolic or diastolic blood pressure control with Diovan HCT 320/25 mg, based upon baseline systolic or diastolic blood pressure.
The curve of each treatment group was estimated by logistic regression modeling. The estimated likelihood at the right tail of each curve is less reliable due to small numbers of subjects with high baseline blood pressures. Figure 1: Probability of Achieving Systolic Blood Pressure < 140 mmHg at Week 8 Figure 2: Probability of Achieving Diastolic Blood Pressure < 90 mmHg at Week 8 Figure 3: Probability of Achieving Systolic Blood Pressure < 130 mmHg at Week 8 Figure 4: Probability of Achieving Diastolic Blood Pressure < 80 mmHg at Week 8 For example, a patient with a baseline blood pressure of 160/100 mmHg has about a 41% likelihood of achieving a goal of < 140 mmHg (systolic) and 60% likelihood of achieving < 90 mmHg (diastolic) on valsartan alone and the likelihood of achieving these goals on HCTZ alone is about 50% (systolic) or 57% (diastolic).
The likelihood of achieving these goals on Diovan HCT rises to about 84% (systolic) or 80% (diastolic). The likelihood of achieving these goals on placebo is about 23% (systolic) or 36% (diastolic). Diovan HCT is the combination tablet of valsartan (Diovan), an angiotensin II receptor blocker (ARB) and hydrochlorothiazide (HCTZ), a diuretic.
Diovan HCT is indicated for the treatment of hypertension, to lower blood pressure: In patients not adequately controlled with monotherapy (1) As initial therapy in patients likely to need multiple drugs to achieve their blood pressure goals (1) Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular events, primarily strokes and myocardial infarctions. Figure 1: Probability of Achieving Systolic Blood Pressure < 140 mmHg at Week 8 Figure 2: Probability of Achieving Diastolic Blood Pressure < 90 mmHg at Week 8 Figure 3: Probability of Achieving Systolic Blood Pressure < 130 mmHg at Week 8 Figure 4: Probability of Achieving Diastolic Blood Pressure < 80 mmHg at Week 8
Contraindications
4 CONTRAINDICATIONS Diovan HCT (valsartan and hydrochlorothiazide, USP) is contraindicated in patients who are hypersensitive to any component of this product. Because of the hydrochlorothiazide component, this product is contraindicated in patients with anuria or hypersensitivity to other sulfonamide-derived drugs. Do not coadminister aliskiren with Diovan HCT in patients with diabetes [see Drug Interactions (7)]. Anuria; Hypersensitivity to any sulfonamide-derived drugs or any component; Do not coadminister aliskiren with Diovan HCT in patients with diabetes. (4)
US FDA labelDosing: Adult
Dose once daily. Titrate as needed to a maximum dose of 320/25mg. (2) May be used as add-on/switch therapy for patients not adequately controlled on any of the components (valsartan or HCTZ). (2) May be substituted for titrated components. (2.3)
2.1 General Considerations
2.1 General Considerations The usual starting dose is Diovan HCT 160/12.5 mg once daily. The dosage can be increased after 1 to 2 weeks of therapy to a maximum of one 320/25 tablet once daily as needed to control blood pressure [see Clinical Studies (14.2)]. Maximum antihypertensive effects are attained within 2 to 4 weeks after a change in dose.
2.2 Add-On Therapy
2.2 Add-On Therapy A patient whose blood pressure is not adequately controlled with valsartan (or another ARB) alone or hydrochlorothiazide alone may be switched to combination therapy with Diovan HCT. A patient who experiences dose-limiting adverse reactions on either component alone may be switched to Diovan HCT containing a lower dose of that component in combination with the other to achieve similar blood pressure reductions.
The clinical response to Diovan HCT should be subsequently evaluated and if blood pressure remains uncontrolled after 3 to 4 weeks of therapy, the dose may be titrated up to a maximum of 320/25 mg.
2.3 Replacement Therapy Diovan
2.3 Replacement Therapy Diovan HCT may be substituted for the titrated components.
2.4 Initial Therapy Diovan
2.4 Initial Therapy Diovan HCT is not recommended as initial therapy in patients with intravascular volume depletion [see Warnings and Precautions (5.2)].
2.5 Use with Other Antihypertensive Drugs Diovan
2.5 Use with Other Antihypertensive Drugs Diovan HCT may be administered with other antihypertensive agents.
Dosing: Altered kidney function
8.6 Renal Impairment Safety and effectiveness of Diovan HCT in patients with severe renal impairment (CrCl ≤ 30 mL/min) have not been established. No dose adjustment is required in patients with mild (CrCl 60 to 90 mL/min) or moderate (CrCl 30 to 60 mL/min) renal impairment.
Renal Insufficiency: There is no apparent correlation between renal function (measured by creatinine clearance) and exposure (measured by AUC) to valsartan in patients with different degrees of renal impairment. Valsartan has not been studied in patients with severe impairment of renal function (creatinine clearance < 10 mL/min).
Valsartan is not removed from the plasma by hemodialysis. In a study in individuals with impaired renal function, the mean elimination half-life of hydrochlorothiazide was doubled in individuals with mild/moderate renal impairment (30 < CrCl < 90 mL/min) and tripled in severe renal impairment (CrCl ≤ 30 mL/min), compared to individuals with normal renal function (CrCl > 90 mL/min) [see Use in Specific Populations (8.6)].
Kidney-specific guidance from renalcarematters.com: in preparation.
Dosing: Hepatic impairment
8.7 Hepatic Impairment Valsartan No dose adjustment is necessary for patients with mild-to-moderate liver disease. No dosing recommendations can be provided for patients with severe liver disease. Hydrochlorothiazide Minor alterations of fluid and electrolyte balance may precipitate hepatic coma in patients with impaired hepatic function or progressive liver disease.
US FDA labelDosing: Pediatric
Pediatric use (US label) US FDA label
8.4 Pediatric Use Safety and effectiveness of Diovan HCT in pediatric patients have not been established.
Dosing: Older adult
Geriatric use (US label) US FDA label
8.5 Geriatric Use In the controlled clinical trials of Diovan HCT, 764 (17.5%) patients treated with valsartan-hydrochlorothiazide were ≥ 65 years and 118 (2.7%) were ≥ 75 years. No overall difference in the efficacy or safety of valsartan-hydrochlorothiazide was observed between these patients and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
Dosage forms
Philippines
- Film-coated tablet: 80 mg/12.5 mg, 80 mg/25 mg, 160 mg + 12.5 mg, 160 mg/12.5 mg, 160 mg/25 mg, 320 mg + 12.5 mg, 320 mg + 25 mg, 320 mg/12.5 mg, 320 mg/25 mg
- Tablet: 80 mg/12. 5 mg, 160 mg/12.5 mg
Registered products in the Philippines
26 products registered with the Food and Drug Administration (FDA) Philippines list Hydrochlorothiazide + Valsartan as the generic name. Registration status changes; confirm a product's current status on the FDA portal before relying on it.
All registered products26
| Package insert | |||||||
|---|---|---|---|---|---|---|---|
Co-DiovanValsartan + Hydrochlorothiazide | 160 mg/12.5 Film-Coated TabletAlu/Alu Blister pack x 14's Box of 28's | RxVAT-exempt | Novartis Farma S.p.A.Italy | Importer: Novartis Healthcare Philippines, Inc. | DRP-7677 | Apr 29, 2029 | |
Co-DiovanValsartan + Hydrochlorothiazide | 320 mg/12.5 mg Film-Coated TabletAlu/Alu Blister Pack x 7’s (Box of 7’s) | RxVAT-exempt | Novartis Farma S.p.A.Italy | Novartis Healthcare Philippines, Inc. | DRP-7651 | Mar 11, 2028 | |
Co-DiovanValsartan + Hydrochlorothiazide | 320 mg/25 mg Film-Coated TabletAlu/Alu Blister Pack x 7’s (Box of 7’s) | RxVAT-exempt | Novartis Farma S.p.A.Italy | Importer: Novartis Healthcare Philippines, Inc. | DRP-7650 | Mar 11, 2028 | |
Co-DiovanValsartan + Hydrochlorothiazide | 80 mg/12.5 mg Film-Coated TabletAlu/Alu Blister Pack x 14's (Box of 28's) | RxVAT-exempt | Novartis Farma S.P.A.Italy | Importer: Novartis Healthcare Philippines, Inc. | DRP-371 | Apr 29, 2029 | |
Co-TaregValsartan + Hydrochlorothiazide | 160 mg/12.5 mg TabletAluminum with lacquered seal x 14's (Box of 28's) | RxVAT-exempt | Novartis Farma S.p.A.Italy | Importer: Sandoz Philippines Corporation | DRP-5180 | Aug 29, 2027 | |
Co-TaregValsartan + Hydrochlorothiazide | 80 mg/12. 5 mg TabletAluminum with lacquered seal x 14's Box of 28's | RxVAT-exempt | Novartis Farma S.P.A.Italy | Importer: Sandoz Philippines Corporation | DRP-5106 | Aug 29, 2027 | |
DuovalValsartan + Hydrochlorothiazide | 80 mg/12.5 mg Film-Coated TabletAlu/Alu Blister Pack x 14's (Box of 28's) | RxVAT-exempt | TABROS PHARMA (PVT.) LTDPakistan | Euroasia Pharmaceuticals, Inc. | DRP-7842 | Jan 29, 2035 | |
Duoval MaxValsartan + Hydrochlorothiazide | 160 mg/12.5 mg Film-Coated TabletAlu/Alu Blister Pack x 14's (Box of 28's) | RxVAT-exempt | Tabros Pharma (Pvt.) LimitedPakistan | Euroasia Pharmaceuticals, Inc | DR-XY44142 | Jan 29, 2030 | |
Torval H 160 / 12.5Valsartan + Hydrochlorothiazide | 160 mg/12.5 mg Film-Coated TabletAlu/Alu Blister Pack X 10's (Box of 30's) | RxVAT-exempt | Torrent Pharmaceuticals Ltd.India | Torrent Pharma Philippines, Inc. | DRP-3953 | May 17, 2027 | |
Torval H 320/12.5Valsartan + Hydrochlorothiazide | 320 mg / 12.5 mg Film-Coated TabletAlu/Alu Blister Pack x 10's (Box of 30's) | RxVAT-exempt | Torrent Pharmaceuticals Ltd.India | Torrent Pharma Philippines, Inc. | DR-XY46762 | Nov 11, 2029 | |
Torval H 320/25Valsartan + Hydrochlorothiazide | 320 mg / 25 mg Film-Coated TabletAlu/Alu Blister Pack x 10's (Box of 30's) | RxVAT-exempt | Torrent Pharmaceuticals Ltd.India | Torrent Pharma Philippines, Inc. | DR-XY46761 | Nov 11, 2029 | |
Torval H 80 / 12.5Valsartan + Hydrochlorothiazide | 80 mg / 12.5 mg Film-Coated TabletAlu/Alu Blister Pack X 10's (Box of 30's) | RxVAT-exempt | Torrent Pharmaceuticals LtdIndia | Torrent Pharma Philippines, Inc. | DRP-3956 | May 17, 2027 | |
VALATAN PLUSValsartan + Hydrochlorothiazide | 80 mg/ 12.5 mg Film-Coated TabletAlu/Alu Blister Pack x 6's (Box of 30's) | RxVAT-exempt | Healthcare Pharmaceuticals Ltd.Bangladesh | Labmate Pharma Inc.Importer: Sanimed Pharmaceuticals Inc. | DRP-7942 | Oct 28, 2029 | |
Valazyd HValsartan + Hydrochlorothiazide | 80 mg/ 12.5 mg Film-Coated TabletAlu/Alu Blister Pack x 10's (Box of 100's) | RxVAT-exempt | Cadila Healthcare LimitedIndia | Zydus Healthcare Philippines, Inc. | DRP-7323 | Feb 22, 2028 | |
Valazyd H 160/25Valsartan + Hydrochlorothiazide | 160 mg/25 mg Film-Coated TabletAlu/Alu Blister pack x 10's (Box of 100's); Alu/Alu Blister pack x 10's (Box of 10's as physician sample) | RxVAT-exempt | Cadila Healthcare LimitedIndia | Zydus Healthcare Philippines Inc. | DRP-7706 | Feb 19, 2028 | |
Valianz HCTValsartan + Hydrochlorothiazide | 80 mg / 12.5 mg Film-Coated TabletAlu/Alu Blister Pack x 10's (Box of 30's) | RxVAT-exempt | Lloyd Laboratories, Inc.Philippines | Trader: Innogen Pharmaceuticals, Inc. | DRP-15167 | Sep 3, 2028 | |
Valianz HCTValsartan + Hydrochlorothiazide | 80 mg/12.5 mg Film-Coated TabletAlu/Alu Blister Pack x 10's (Box of 30's) | RxVAT-exempt | Lloyd Laboratories, Inc.Philippines | Trader: Innogen Pharmaceuticals, Inc. | DR-XY42529 | Sep 3, 2028 | |
Valsajub HValsartan + Hydrochlorothiazide | 160 mg + 12.5 mg Film-Coated TabletAlu/Alu Blister Pack of 7's Box of 28's | RxVAT-exempt | JUBILANT GENERICS LIMITEDIndia | Healol Pharma Corporation | DRP-4409 | May 3, 2028 | |
Valsajub HValsartan + Hydrochlorothiazide | 160 mg/25 mg Film-Coated TabletAlu/Alu Blister Pack of 7's Box of 28's | RxVAT-exempt | JUBILANT GENERICS LIMITEDIndia | Healol Pharma Corporation | DRP-4408 | May 3, 2028 | |
Valsajub HValsartan + Hydrochlorothiazide | 320 mg + 12.5 mg Film-Coated TabletAlu/Alu Blister Pack x 10's (Box of 30's) | RxVAT-exempt | Jubilant Generics LimitedIndia | Healol Pharma Corporation | DRP-4405 | May 3, 2028 | |
Valsajub HValsartan + Hydrochlorothiazide | 320 mg + 25 mg Film-Coated TabletAlu/Alu Blister Pack x 10's (Box of 30's) | RxVAT-exempt | Jubilant Generics LimitedIndia | Healol Pharma Corporation | DRP-4406 | May 3, 2028 | |
Valsajub HValsartan + Hydrochlorothiazide | 80 mg/12.5 mg Film-Coated TabletAlu/Alu Blister Pack of 7's (Box of 28's) | RxVAT-exempt | JUBILANT GENERICS LIMITEDIndia | Healol Pharma Corporation | DRP-4407 | May 3, 2028 | |
Valstad PlusValsartan + Hydrochlorothiazide | 160 mg / 12.5 mg Film-coated TabletAlu/PVC/PVDC Blister Pack x 14's (Box of 28's) | RxVAT-exempt | Hemofarm ADSerbia | STADA Philippines Inc.Trader: STADA Arzneimittel AG | DRP-5677 | Sep 6, 2028 | |
Valstad PlusValsartan + Hydrochlorothiazide | 80 mg / 12.5 mg Film-Coated TabletAlu/PVC/PVDC Blister Pack x 14's (Box of 28's) | RxVAT-exempt | Hemofarm ADSerbia | STADA Philippines Inc.Trader: STADA Arzneimittel AG | DRP-5740 | Sep 6, 2028 | |
Valstan HCT 160/12.5Valsartan + Hydrochlorothiazide | 160 mg/12.5 mg Film Coated TabletAlu/Alu Blister Pack X 10's (Box of 30's) | RxVAT-exempt | Rhydburg PharmaceuticalsIndia Brady Pharma Inc. | Sahar International Trading Inc | DRP-6728 | Jun 21, 2031 | |
Valstan HCT 80/25Valsartan + Hydrochlorothiazide | 80 mg / 25 mg FIlm Coated TabletAlu/Alu Blister Pack x 10's (Box of 30's) | RxVAT-exempt | Rhydburg Pharmaceuticals Ltd.Uttarhand India | Sahar International Trading Inc.Importer: Sahar International Trading Inc | DR-XY45499 | Jul 8, 2031 |
Source: FDA Philippines product registration database. "Valid until" is the registration validity date listed by the FDA; a past date may mean a renewal is pending. Package insert links point to files published by the FDA.
United States (label)
Dosage forms and strengths (US label) US FDA label
3 DOSAGE FORMS AND STRENGTHS 80/12.5 mg tablets, imprinted CG/HGH (Side 1/Side 2) 160/12.5 mg tablets, imprinted CG/HHH 160/25 mg tablets, imprinted NVR/HXH 320/12.5 mg tablets, imprinted NVR/HIL 320/25 mg tablets, imprinted NVR/CTI Tablets (valsartan/HCTZ mg): 80/12.5, 160/12.5, 160/25, 320/12.5, 320/25 (3)
Warnings/Precautions
The boxed warning is shown at the top of this page.
- Hypotension: Correct volume depletion prior to initiation (5.2)
- Observe for signs of fluid or electrolyte imbalance (5.9)
- Monitor renal function and potassium in susceptible patients (5.3, 5.7)
- Exacerbation or activation of systemic lupus erythematosus (5.5)
- Acute angle-closure glaucoma (5.8)
5.1 Fetal Toxicity Diovan
5.1 Fetal Toxicity Diovan HCT can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Resulting oligohydramnios can be associated with fetal lung hypoplasia and skeletal deformations.
Potential neonatal adverse effects include skull hypoplasia, anuria, hypotension, renal failure, and death. Thiazides cross the placenta, and use of thiazides during pregnancy is associated with fetal or neonatal jaundice, thrombocytopenia, and possibly other adverse reactions that have occurred in adults. When pregnancy is detected, discontinue Diovan HCT as soon as possible [see Use in Specific Populations (8.1)].
5.2 Hypotension in Volume-
5.2 Hypotension in Volume- and/or Salt-Depleted Patients Excessive reduction of blood pressure was rarely seen (0.7%) in patients with uncomplicated hypertension treated with Diovan HCT in controlled trials. In patients with an activated renin-angiotensin system, such as volume- and/or salt-depleted patients receiving high doses of diuretics, symptomatic hypotension may occur.
This condition should be corrected prior to administration of Diovan HCT, or the treatment should start under close medical supervision. If hypotension occurs, place the patient in the supine position and, if necessary, give intravenous normal saline. A transient hypotensive response is not a contraindication to further treatment, which usually can be continued without difficulty once the blood pressure has stabilized.
5.3 Impaired Renal Function
5.3 Impaired Renal Function Changes in renal function including acute renal failure can be caused by drugs that inhibit the renin-angiotensin system and by diuretics. Patients whose renal function may depend in part on the activity of the renin-angiotensin system (e.g., patients with renal artery stenosis, chronic kidney disease, severe congestive heart failure, or volume depletion) may be at particular risk of developing acute renal failure on Diovan HCT.
Monitor renal function periodically in these patients. Consider withholding or discontinuing therapy in patients who develop a clinically significant decrease in renal function on Diovan HCT [see Drug Interactions (7)].
5.4 Hypersensitivity Reaction
5.4 Hypersensitivity Reaction Hypersensitivity reactions to hydrochlorothiazide may occur in patients with or without a history of allergy or bronchial asthma, but are more likely in patients with such a history.
5.5 Systemic Lupus Erythematosus
5.5 Systemic Lupus Erythematosus Thiazide diuretics have been reported to cause exacerbation or activation of systemic lupus erythematosus.
5.6 Lithium Interaction
5.6 Lithium Interaction Increases in serum lithium concentrations and lithium toxicity have been reported with concomitant use of valsartan or thiazide diuretics. Monitor lithium levels in patients receiving Diovan HCT and lithium [see Drug Interactions (7)].
5.7 Potassium Abnormalities
5.7 Potassium Abnormalities In the controlled trials of various doses of Diovan HCT, the incidence of hypertensive patients who developed hypokalemia (serum potassium < 3.5 mEq/L) was 3.0%; the incidence of hyperkalemia (serum potassium > 5.7 mEq/L) was 0.4%. Hydrochlorothiazide can cause hypokalemia and hyponatremia. Hypomagnesemia can result in hypokalemia which appears difficult to treat despite potassium repletion.
Drugs that inhibit the renin-angiotensin system can cause hyperkalemia. Monitor serum electrolytes periodically. If hypokalemia is accompanied by clinical signs (e.g., muscular weakness, paresis, or ECG alterations), Diovan HCT should be discontinued. Correction of hypokalemia and any coexisting hypomagnesemia is recommended prior to the initiation of thiazides.
Some patients with heart failure have developed increases in potassium with Diovan therapy. These effects are usually minor and transient, and they are more likely to occur in patients with pre-existing renal impairment. Dosage reduction and/or discontinuation of the diuretic and/or Diovan may be required [see Adverse Reactions (6.1)].
5.8 Acute Myopia and Secondary Angle-Closure Glaucoma
5.8 Acute Myopia and Secondary Angle-Closure Glaucoma Hydrochlorothiazide, a sulfonamide, can cause an idiosyncratic reaction, resulting in acute transient myopia and acute angle-closure glaucoma. Symptoms include acute onset of decreased visual acuity or ocular pain and typically occur within hours to weeks of drug initiation.
Untreated acute angle-closure glaucoma can lead to permanent vision loss. The primary treatment is to discontinue hydrochlorothiazide as rapidly as possible. Prompt medical or surgical treatments may need to be considered if the intraocular pressure remains uncontrolled. Risk factors for developing acute angle-closure glaucoma may include a history of sulfonamide or penicillin allergy.
5.9 Metabolic Disturbances
5.9 Metabolic Disturbances Hydrochlorothiazide may alter glucose tolerance and raise serum levels of cholesterol and triglycerides. Hydrochlorothiazide may raise the serum uric acid level due to reduced clearance of uric acid and may cause or exacerbate hyperuricemia and precipitate gout in susceptible patients. Hydrochlorothiazide decreases urinary calcium excretion and may cause elevations of serum calcium.
Monitor calcium levels in patients with hypercalcemia receiving Diovan HCT.
Drug interactions
Drug interactions (US label) US FDA label
7 DRUG INTERACTIONS Valsartan-Hydrochlorothiazide: Lithium: Increases in serum lithium concentrations and lithium toxicity have been reported during concomitant administration of lithium with angiotensin II receptor antagonists or thiazides. Monitor lithium levels in patients taking Diovan HCT. Valsartan: Agents Increasing Serum Potassium: Concomitant use of valsartan with other agents that block the renin-angiotensin system, potassium-sparing diuretics (e.g., spironolactone, triamterene, amiloride), potassium supplements, salt substitutes containing potassium or other drugs that may increase potassium levels (e.g., heparin) may lead to increases in serum potassium and in heart failure patients to increases in serum creatinine.
If co-medication is considered necessary, monitoring of serum potassium is advisable. Non-Steroidal Anti-Inflammatory Agents (NSAIDs), Including Selective Cyclooxygenase-2 Inhibitors (COX-2 Inhibitors): In patients who are elderly, volume-depleted (including those on diuretic therapy), or with compromised renal function, coadministration of NSAIDs, including selective COX-2 inhibitors, with angiotensin II receptor antagonists, including valsartan, may result in deterioration of renal function, including possible acute renal failure.
These effects are usually reversible. Monitor renal function periodically in patients receiving valsartan and NSAID therapy. The antihypertensive effect of angiotensin II receptor antagonists, including valsartan, may be attenuated by NSAIDs including selective COX-2 inhibitors. Dual Blockade of the Renin-Angiotensin System (RAS): Dual blockade of the RAS with angiotensin receptor blockers, ACE inhibitors, or aliskiren is associated with increased risks of hypotension, hyperkalemia, and changes in renal function (including acute renal failure) compared to monotherapy.
Most patients receiving the combination of two RAS inhibitors do not obtain any additional benefit compared to monotherapy. In general, avoid combined use of RAS inhibitors. Closely monitor blood pressure, renal function and electrolytes in patients on valsartan and other agents that affect the RAS. Do not coadminister aliskiren with valsartan in patients with diabetes.
Avoid use of aliskiren with valsartan in patients with renal impairment (GFR < 60 mL/min). Hydrochlorothiazide: When administered concurrently, the following drugs may interact with thiazide diuretics: Antidiabetic Drugs (oral agents and insulin) - Dosage adjustment of the antidiabetic drug may be required. Nonsteroidal Anti-inflammatory Drugs (NSAIDs and COX-2 selective inhibitors) - When Diovan HCT and nonsteroidal anti-inflammatory agents are used concomitantly, the patient should be observed closely to determine if the desired effect of the diuretic is obtained.
Carbamazepine – May lead to symptomatic hyponatremia. Ion Exchange Resins: Staggering the dosage of hydrochlorothiazide and ion exchange resins (e.g., cholestyramine, colestipol) such that hydrochlorothiazide is administered at least 4 hours before or 4 to 6 hours after the administration of resins would potentially minimize the interaction [see Clinical Pharmacology (12.3)].
Cyclosporine: Concomitant treatment with cyclosporine may increase the risk of hyperuricemia and gout-type complications. Antidiabetic drugs: Dosage adjustment of antidiabetic may be required. (7) Cholestyramine and colestipol: Reduced absorption of thiazides. (12.3) Lithium: Increased risk of lithium toxicity. Monitor serum lithium concentrations during concurrent use.
(7) Non-Steroidal Anti-Inflammatory Drugs (NSAIDs): May increase risk of renal impairment. Can reduce diuretic, natriuretic and antihypertensive effects of diuretics. (7) Dual inhibition of the renin-angiotensin system: Increased risk of renal impairment, hypotension, and hyperkalemia. (7)
Metabolism and transporters (CYP, P-gp, OATP; US label) US FDA label
In vitro metabolism studies involving recombinant CYP 450 enzymes indicated that the CYP 2C9 isoenzyme is responsible for the formation of valeryl-4-hydroxy valsartan.
Valsartan does not inhibit CYP 450 isozymes at clinically relevant concentrations.
CYP 450 mediated drug interaction between valsartan and coadministered drugs are unlikely because of the low extent of metabolism.
Transporters: The results from an in vitro study with human liver tissue indicate that valsartan is a substrate of the hepatic uptake transporter OATP1B1 and the hepatic efflux transporter MRP2.
Adverse reactions
- The most common reasons for discontinuation of therapy with Diovan HCT were headache and dizziness. The only adverse experience that occurred in ≥ 2% of patients treated with Diovan HCT and at a higher incidence than placebo was nasopharyngitis (2.4% vs. 1.9%). (6.1)
- To report SUSPECTED ADVERSE REACTIONS, contact Novartis Pharmaceuticals Corporation at 1-888-669-6682 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1 Clinical Trials Experience
6.1 Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reactions rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in practice. The adverse reaction information from clinical trials does, however, provide a basis for identifying the adverse events that appear to be related to drug use and for approximating rates.
Hypertension Diovan HCT (valsartan and hydrochlorothiazide, USP) has been evaluated for safety in more than 5700 patients, including over 990 treated for over 6 months, and over 370 for over 1 year. Adverse experiences have generally been mild and transient in nature and have only infrequently required discontinuation of therapy.
The overall incidence of adverse reactions with Diovan HCT was comparable to placebo. The overall frequency of adverse reactions was neither dose-related nor related to gender, age, or race. In controlled clinical trials, discontinuation of therapy due to side effects was required in 2.3% of valsartan-hydrochlorothiazide patients and 3.1% of placebo patients.
The most common reasons for discontinuation of therapy with Diovan HCT were headache and dizziness. The only adverse reaction that occurred in controlled clinical trials in at least 2% of patients treated with Diovan HCT and at a higher incidence in valsartan-hydrochlorothiazide (n = 4372) than placebo (n = 262) patients was nasopharyngitis (2.4% vs. 1.9%).
Dose-related orthostatic effects were seen in fewer than 1% of patients. In individual trials, a dose-related increase in the incidence of dizziness was observed in patients treated with Diovan HCT. Initial Therapy-Hypertension In a clinical study in patients with severe hypertension (diastolic blood pressure ≥ 110 mmHg and systolic blood pressure ≥ 140 mmHg), the overall pattern of adverse reactions reported through 6 weeks of follow-up was similar in patients treated with Diovan HCT as initial therapy and in patients treated with valsartan as initial therapy.
Comparing the groups treated with Diovan HCT (force-titrated to 320/25 mg) and valsartan (force-titrated to 320 mg), dizziness was observed in 6% and 2% of patients, respectively. Hypotension was observed in 1% of those patients receiving Diovan HCT and 0% of patients receiving valsartan. There were no reported cases of syncope in either treatment group.
Laboratory changes with Diovan HCT as initial therapy in patients with severe hypertension were similar to those reported with Diovan HCT in patients with less severe hypertension [see Clinical Studies (14.2), Drug Interactions (7)]. Valsartan: In trials in which valsartan was compared to an ACE inhibitor with or without placebo, the incidence of dry cough was significantly greater in the ACE inhibitor group (7.9%) than in the groups who received valsartan (2.6%) or placebo (1.5%).
In a 129-patient trial limited to patients who had had dry cough when they had previously received ACE inhibitors, the incidences of cough in patients who received valsartan, hydrochlorothiazide, or lisinopril were 20%, 19%, 69%, respectively (p < 0.001).
6.2 Postmarketing Experience
6.2 Postmarketing Experience The following additional adverse reactions have been reported in valsartan or valsartan/hydrochlorothiazide postmarketing experience. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Hypersensitivity: Angioedema has been reported. Some of these patients previously experienced angioedema with other drugs including ACE inhibitors. Diovan HCT should not be re-administered to patients who have had angioedema. Digestive: Elevated liver enzymes and reports of hepatitis Musculoskeletal: Rhabdomyolysis Renal: Impaired renal function Dermatologic: Alopecia, bullous dermatitis Vascular: Vasculitis Nervous System: Syncope Hydrochlorothiazide: The following additional adverse reactions have been reported in postmarketing experience with hydrochlorothiazide: Acute renal failure, renal disorder, aplastic anemia, erythema multiforme, pyrexia, muscle spasm, asthenia, acute angle-closure glaucoma, bone marrow failure, worsening of diabetes control, hypokalemia, blood lipids increased, hyponatremia, hypomagnesemia, hypercalcemia, hypochloremic alkalosis, impotence, and visual impairment.
Pathological changes in the parathyroid gland of patients with hypercalcemia and hypophosphatemia have been observed in a few patients on prolonged thiazide therapy. If hypercalcemia occurs, further diagnostic evaluation is necessary. Non-melanoma Skin Cancer: Hydrochlorothiazide is associated with an increased risk of non-melanoma skin cancer.
In a study conducted in the Sentinel System, increased risk was predominantly for squamous cell carcinoma (SCC) and in white patients taking large cumulative doses. The increased risk for SCC in the overall population was approximately 1 additional case per 16,000 patients per year, and for white patients taking a cumulative dose of ≥ 50,000 mg the risk increase was approximately 1 additional SCC case for every 6,700 patients per year.
Pregnancy considerations
Pregnancy (US label) US FDA label
8.1 Pregnancy Risk Summary Diovan HCT can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
Published reports include cases of anhydramnios and oligohydramnios in pregnant women treated with valsartan (see Clinical Considerations). When pregnancy is detected discontinue Diovan HCT as soon as possible. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section and post-partum hemorrhage).
Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death. Pregnant women with hypertension should be carefully monitored and managed accordingly. Fetal/Neonatal Adverse Reactions Valsartan Oligohydramnios in pregnant women who use drugs affecting the renin-angiotensin system in the second and third trimesters of pregnancy can result in the following: reduced fetal renal function leading to anuria and renal failure, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension and death.
Perform serial ultrasound examinations to assess the intra-amniotic environment. Fetal testing may be appropriate, based on the week of gestation. Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury. If oligohydramnios is observed, consider alternative drug treatment.
Closely observe neonates with histories of in utero exposure to Diovan HCT for hypotension, oliguria, and hyperkalemia. In neonates with a history of in utero exposure to Diovan HCT, if oliguria or hypotension occurs, support blood pressure and renal perfusion. Exchange transfusions or dialysis may be required as a means of reversing hypotension and replacing renal function.
Hydrochlorothiazide Thiazides can cross the placenta, and concentrations reached in the umbilical vein approach those in the maternal plasma. Hydrochlorothiazide, like other diuretics, can cause placental hypoperfusion. It accumulates in the amniotic fluid, with reported concentrations up to 19 times higher than in umbilical vein plasma.
Use of thiazides during pregnancy is associated with a risk of fetal or neonatal jaundice or thrombocytopenia. Since they do not prevent or alter the course of EPH (Edema, Proteinuria, Hypertension) gestosis (pre-eclampsia), these drugs should not be used to treat hypertension in pregnant women. The use of hydrochlorothiazide for other indications (e.g., heart disease) in pregnancy should be avoided.
Data Animal Data Valsartan plus Hydrochlorothiazide There was no evidence of teratogenicity in mice, rats, or rabbits treated orally with valsartan at doses of up to 600, 100, and 10 mg/kg/day [9, 3.5 and 0.5 times the maximum recommended human dose (MRHD)], respectively, in combination with hydrochlorothiazide at doses up to 188, 31, and 3 mg/kg/day (38, 13 and 2 times the MRHD). Fetotoxicity was observed in association with maternal toxicity in rats at valsartan/hydrochlorothiazide doses of ≥ 200/63 mg/kg/day and in rabbits at valsartan/hydrochlorothiazide doses of 10/3 mg/kg/day.
Evidence of fetotoxicity in rats consisted of decreased fetal weight and fetal variations of sternebrae, vertebrae, ribs, and/or renal papillae. Evidence of fetotoxicity in rabbits included increased numbers of late resorptions with resultant increases in total resorptions, post-implantation losses, and decreased number of live fetuses.
Mechanism of action
12.1 Mechanism of Action Angiotensin II is formed from angiotensin I in a reaction catalyzed by angiotensin-converting enzyme (ACE, kininase II). Angiotensin II is the principal pressor agent of the renin-angiotensin system, with effects that include vasoconstriction, stimulation of synthesis and release of aldosterone, cardiac stimulation, and renal reabsorption of sodium.
Valsartan blocks the vasoconstrictor and aldosterone-secreting effects of angiotensin II by selectively blocking the binding of angiotensin II to the AT 1 receptor in many tissues, such as vascular smooth muscle and the adrenal gland. Its action is therefore independent of the pathways for angiotensin II synthesis. There is also an AT 2 receptor found in many tissues, but AT 2 is not known to be associated with cardiovascular homeostasis.
Valsartan has much greater affinity (about 20,000-fold) for the AT 1 receptor than for the AT 2 receptor. The primary metabolite of valsartan is essentially inactive with an affinity for the AT 1 receptor about one 200th that of valsartan itself. Blockade of the renin-angiotensin system with ACE inhibitors, which inhibit the biosynthesis of angiotensin II from angiotensin I, is widely used in the treatment of hypertension.
ACE inhibitors also inhibit the degradation of bradykinin, a reaction also catalyzed by ACE. Because valsartan does not inhibit ACE (kininase II), it does not affect the response to bradykinin. Whether this difference has clinical relevance is not yet known. Valsartan does not bind to or block other hormone receptors or ion channels known to be important in cardiovascular regulation.
Blockade of the angiotensin II receptor inhibits the negative regulatory feedback of angiotensin II on renin secretion, but the resulting increased plasma renin activity and angiotensin II circulating levels do not overcome the effect of valsartan on blood pressure. Hydrochlorothiazide is a thiazide diuretic. Thiazides affect the renal tubular mechanisms of electrolyte reabsorption, directly increasing excretion of sodium and chloride in approximately equivalent amounts.
Indirectly, the diuretic action of hydrochlorothiazide reduces plasma volume, with consequent increases in plasma renin activity, increases in aldosterone secretion, increases in urinary potassium loss, and decreases in serum potassium. The renin-aldosterone link is mediated by angiotensin II, so coadministration of an angiotensin II receptor antagonist tends to reverse the potassium loss associated with these diuretics.
The mechanism of the antihypertensive effect of thiazides is unknown.
US FDA labelPharmacodynamics
Pharmacodynamics (US label) US FDA label
12.2 Pharmacodynamics Valsartan: Valsartan inhibits the pressor effect of angiotensin II infusions. An oral dose of 80 mg inhibits the pressor effect by about 80% at peak with approximately 30% inhibition persisting for 24 hours. No information on the effect of larger doses is available. Removal of the negative feedback of angiotensin II causes a 2- to 3-fold rise in plasma renin and consequent rise in angiotensin II plasma concentration in hypertensive patients.
Minimal decreases in plasma aldosterone were observed after administration of valsartan; very little effect on serum potassium was observed. Hydrochlorothiazide: After oral administration of hydrochlorothiazide, diuresis begins within 2 hours, peaks in about 4 hours and lasts about 6 to 12 hours. Pharmacodynamic Drug Interactions Hydrochlorothiazide: Alcohol, barbiturates, or narcotics: Potentiation of orthostatic hypotension may occur.
Skeletal muscle relaxants: Possible increased responsiveness to muscle relaxants such as curare derivatives. Digitalis glycosides: Thiazide-induced hypokalemia or hypomagnesemia may predispose the patient to digoxin toxicity.
Pharmacokinetics
Valsartan shows bi-exponential decay kinetics following intravenous administration, with an average elimination half-life of about 6 hours.
Following oral administration, plasma hydrochlorothiazide concentrations decline bi-exponentially, with a mean distribution half-life of about 2 hours and an elimination half-life of about 10 hours.
Excretion Valsartan: Valsartan, when administered as an oral solution, is primarily recovered in feces (about 83% of dose) and urine (about 13% of dose).
Following intravenous administration, plasma clearance of valsartan is about 2 L/h and its renal clearance is 0.62 L/h (about 30% of total clearance).
Hydrochlorothiazide: About 70% of an orally administered dose of hydrochlorothiazide is eliminated in the urine as unchanged drug.
Pharmacokinetics (US label) US FDA label
12.3 Pharmacokinetics Valsartan: Valsartan peak plasma concentration is reached 2 to 4 hours after dosing. Valsartan shows bi-exponential decay kinetics following intravenous administration, with an average elimination half-life of about 6 hours. Absolute bioavailability for the capsule formulation is about 25% (range 10% to 35%).
Food decreases the exposure (as measured by area under the curve [AUC]) to valsartan by about 40% and peak plasma concentration (C max) by about 50%. AUC and C max values of valsartan increase approximately linearly with increasing dose over the clinical dosing range. Valsartan does not accumulate appreciably in plasma following repeated administration.
Hydrochlorothiazide: The estimated absolute bioavailability of hydrochlorothiazide after oral administration is about 70%. Peak plasma hydrochlorothiazide concentrations (C max) are reached within 2 to 5 hours after oral administration. There is no clinically significant effect of food on the bioavailability of hydrochlorothiazide.
Hydrochlorothiazide binds to albumin (40% to 70%) and distributes into erythrocytes. Following oral administration, plasma hydrochlorothiazide concentrations decline bi-exponentially, with a mean distribution half-life of about 2 hours and an elimination half-life of about 10 hours. Diovan HCT: Diovan HCT may be administered with or without food.
Distribution Valsartan: The steady state volume of distribution of valsartan after intravenous administration is small (17 L), indicating that valsartan does not distribute into tissues extensively. Valsartan is highly bound to serum proteins (95%), mainly serum albumin. Metabolism Valsartan: The primary metabolite, accounting for about 9% of dose, is valeryl 4-hydroxy valsartan.
In vitro metabolism studies involving recombinant CYP 450 enzymes indicated that the CYP 2C9 isoenzyme is responsible for the formation of valeryl-4-hydroxy valsartan. Valsartan does not inhibit CYP 450 isozymes at clinically relevant concentrations. CYP 450 mediated drug interaction between valsartan and coadministered drugs are unlikely because of the low extent of metabolism.
Hydrochlorothiazide: Is not metabolized. Excretion Valsartan: Valsartan, when administered as an oral solution, is primarily recovered in feces (about 83% of dose) and urine (about 13% of dose). The recovery is mainly as unchanged drug, with only about 20% of dose recovered as metabolites. Following intravenous administration, plasma clearance of valsartan is about 2 L/h and its renal clearance is 0.62 L/h (about 30% of total clearance).
Hydrochlorothiazide: About 70% of an orally administered dose of hydrochlorothiazide is eliminated in the urine as unchanged drug. Specific Populations Geriatric: Exposure (measured by AUC) to valsartan is higher by 70% and the half-life is longer by 35% in the elderly than in the young. A limited amount of data suggest that the systemic clearance of hydrochlorothiazide is reduced in both healthy and hypertensive elderly subjects compared to young healthy volunteers.
Gender: Pharmacokinetics of valsartan do not differ significantly between males and females. Race: Pharmacokinetic differences due to race have not been studied. Renal Insufficiency: There is no apparent correlation between renal function (measured by creatinine clearance) and exposure (measured by AUC) to valsartan in patients with different degrees of renal impairment.
Valsartan has not been studied in patients with severe impairment of renal function (creatinine clearance < 10 mL/min). Valsartan is not removed from the plasma by hemodialysis. In a study in individuals with impaired renal function, the mean elimination half-life of hydrochlorothiazide was doubled in individuals with mild/moderate renal impairment (30 < CrCl < 90 mL/min) and tripled in severe renal impairment (CrCl ≤ 30 mL/min), compared to individuals with normal renal function (CrCl > 90 mL/min) [see Use in Specific Populations (8.6)].
Hepatic Insufficiency: On average, patients with mild-to-moderate chronic liver disease have twice the exposure (measured by AUC values) to valsartan of healthy volunteers (matched by age, sex, and weight) [see Use in Specific Populations (8.7)]. Drug Interactions Valsartan No clinically significant pharmacokinetic interactions were observed when Diovan (valsartan) was coadministered with amlodipine, atenolol, cimetidine, digoxin, furosemide, glyburide, hydrochlorothiazide, or indomethacin.
The valsartan-atenolol combination was more antihypertensive than either component, but it did not lower the heart rate more than atenolol alone. Coadministration of valsartan and warfarin did not change the pharmacokinetics of valsartan or the time-course of the anticoagulant properties of warfarin. Transporters: The results from an in vitro study with human liver tissue indicate that valsartan is a substrate of the hepatic uptake transporter OATP1B1 and the hepatic efflux transporter MRP2.
Coadministration of inhibitors of the uptake transporter (rifampin, cyclosporine) or efflux transporter (ritonavir) may increase the systemic exposure to valsartan. Hydrochlorothiazide: Drugs that alter gastrointestinal motility: The bioavailability of thiazide-type diuretics may be increased by anticholinergic agents (e.g., atropine, biperiden), apparently due to a decrease in gastrointestinal motility and the stomach emptying rate.
Conversely, pro-kinetic drugs may decrease the bioavailability of thiazide diuretics. Cholestyramine: In a dedicated drug interaction study, administration of cholestyramine 2 hours before hydrochlorothiazide resulted in a 70% reduction in exposure to hydrochlorothiazide. Further, administration of hydrochlorothiazide 2 hours before cholestyramine resulted in 35% reduction in exposure to hydrochlorothiazide.
Antineoplastic agents (e.g., cyclophosphamide, methotrexate): Concomitant use of thiazide diuretics may reduce renal excretion of cytotoxic agents and enhance their myelosuppressive effects.
Formulary and pricing (Philippines)
Government price references
| Preparation | Price (PHP) | Unit | Type |
|---|---|---|---|
| Valsartan + Hydrochlorothiazide 80 mg + 12.5 mg Tablet | ₱11.49–₱12.04Reference ₱11.49 | per tablet | DPRI procurement range |
| 80 mg + 12.5 mg tablet | ₱16.75 | per tablet | PhilHealth GAMOT fixed fee |
PhilHealth GAMOT fixed fee paid to the accredited GAMOT pharmacy per unit dispensed Range = lowest-highest procurement price (highest usable only in GIDA areas); reference_price = 2021 DPRI ceiling (median)
These are government procurement and reimbursement references, not retail prices. Sources:
- DOH Drug Price Reference Index (DPRI) 2021, 9th edition (as of September 17, 2021); https://caro.doh.gov.ph/wp-content/uploads/2021/09/2021DPRI-as-of-9-17-2021.pdf, as of September 17, 2021
- PhilHealth Circular No. 2026-0018, Annex A.2 GAMOT Fixed Fee Schedule (249 preparations; fees otherwise unchanged from PC2025-0013); https://www.philhealth.gov.ph/circulars/2026/PC-2026-0018.pdf, as of October 13, 2026
Formulary and coverage
| Philippine National Formulary | Listed as Valsartan + Hydrochlorothiazide |
| PNF listing | Oral: 80 mg valsartan + 12.5 mg hydrochlorothiazide tablet |
| PhilHealth GAMOT | Yes (listed since July 28, 2025) |
Sources:
- PNF Essential Medicines List, 8th ed. (as of November 2, 2022), DOH; https://www.philhealth.gov.ph/partners/providers/pdf/PNF-EML_11022022.pdf, as of November 2, 2022
- PhilHealth Circular No. 2026-0018, Expanding Access to Outpatient First-line Anti-TB Drugs through PhilHealth GAMOT, Annex A.i GAMOT List (81 molecules); https://www.philhealth.gov.ph/circulars/2026/PC-2026-0018.pdf
Check availability
Prices and stock vary by branch; renalcarematters.com does not sell medicines or receive payment from pharmacies.
Related guides
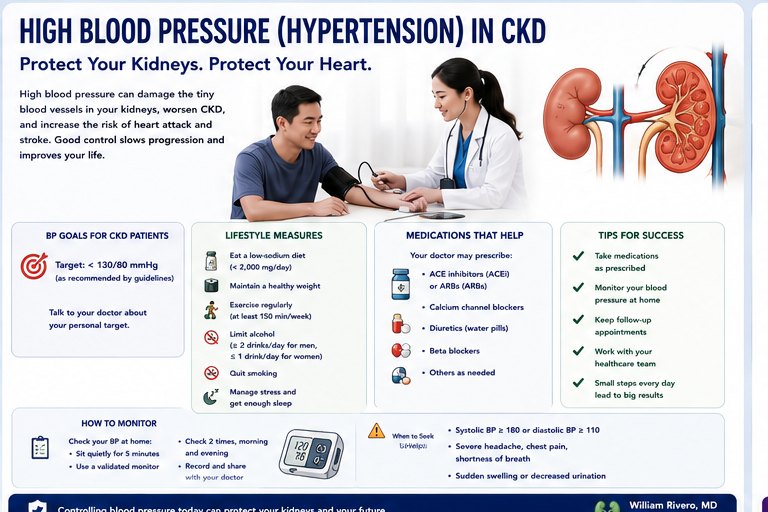
Guides on renalcarematters.com for this medicine, for patients and clinicians.
References
- U.S. Food and Drug Administration. Diovan HCT · Novartis Pharmaceuticals Corporation [US FDA-approved label, version 34, February 13, 2026]. Via DailyMed/openFDA. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=d76a0419-05ee-437e-884c-65807aea9569
- Food and Drug Administration Philippines. Verification portal (product registrations). https://verification.fda.gov.ph
- PNF Essential Medicines List, 8th ed. (as of November 2, 2022), DOH; https://www.philhealth.gov.ph/partners/providers/pdf/PNF-EML_11022022.pdf
- PhilHealth Circular No. 2026-0018, Expanding Access to Outpatient First-line Anti-TB Drugs through PhilHealth GAMOT, Annex A.i GAMOT List (81 molecules); https://www.philhealth.gov.ph/circulars/2026/PC-2026-0018.pdf
- PhilHealth Circular No. 2026-0018, Annex A.2 GAMOT Fixed Fee Schedule (249 preparations; fees otherwise unchanged from PC2025-0013); https://www.philhealth.gov.ph/circulars/2026/PC-2026-0018.pdf
- DOH Drug Price Reference Index (DPRI) 2021, 9th edition (as of September 17, 2021); https://caro.doh.gov.ph/wp-content/uploads/2021/09/2021DPRI-as-of-9-17-2021.pdf
This page shows official label and registry text only; no renalcarematters.com clinical summary has been approved for it yet.
Last updated: .