Use: Labeled indications
- In combination with a statin, or alone when additional low-density lipoprotein cholesterol (LDL-C) lowering therapy is not possible, as an adjunct to diet to reduce elevated LDL-C in adults with primary hyperlipidemia…
- In combination with a statin, or alone when additional low density lipoprotein cholesterol (LDL-C) lowering therapy is not possible, as an adjunct to diet to reduce elevated LDL-C in adults with primary hyperlipidemia…
Full indications and usage US FDA label
1 INDICATIONS AND USAGE ZETIA ® is indicated: In combination with a statin, or alone when additional low-density lipoprotein cholesterol (LDL-C) lowering therapy is not possible, as an adjunct to diet to reduce elevated LDL-C in adults with primary hyperlipidemia, including heterozygous familial hypercholesterolemia (HeFH). In combination with a statin as an adjunct to diet to reduce elevated LDL-C in pediatric patients 10 years of age and older with HeFH.
In combination with fenofibrate as an adjunct to diet to reduce elevated LDL-C in adults with mixed hyperlipidemia. In combination with a statin, and other LDL-C lowering therapies, to reduce elevated LDL-C levels in adults and in pediatric patients 10 years of age and older with homozygous familial hypercholesterolemia (HoFH).
As an adjunct to diet for the reduction of elevated sitosterol and campesterol levels in adults and in pediatric patients 9 years of age and older with homozygous familial sitosterolemia. When ZETIA is used in combination with a statin, fenofibrate, or other LDL-C lowering therapies, refer to the Prescribing Information of these products for information on the safe and effective use.
ZETIA is indicated (1): In combination with a statin, or alone when additional low density lipoprotein cholesterol (LDL-C) lowering therapy is not possible, as an adjunct to diet to reduce elevated LDL-C in adults with primary hyperlipidemia, including heterozygous familial hypercholesterolemia (HeFH). In combination with a statin as an adjunct to diet to reduce elevated LDL-C in pediatric patients 10 years of age and older with HeFH.
In combination with fenofibrate as an adjunct to diet to reduce elevated LDL-C in adults with mixed hyperlipidemia. In combination with a statin, and other LDL-C lowering therapies, to reduce elevated LDL-C levels in adults and in pediatric patients 10 years of age and older with homozygous familial hypercholesterolemia (HoFH).
As an adjunct to diet for the reduction of elevated sitosterol and campesterol levels in adults and in pediatric patients 9 years of age and older with homozygous familial sitosterolemia. When ZETIA is used in combination with a statin, fenofibrate, or other LDL-C lowering therapies, refer to the Prescribing Information of these products for information on the safe and effective use (1).
Contraindications
4 CONTRAINDICATIONS ZETIA is contraindicated in patients with a known hypersensitivity to ezetimibe or any of the excipients in ZETIA. Hypersensitivity reactions including anaphylaxis, angioedema, rash, and urticaria have been reported [see Adverse Reactions (6.2)]. When used in combination with a statin, fenofibrate, or other LDL-C lowering therapy, ZETIA is contraindicated in patients for whom a statin, fenofibrate, or other LDL-C lowering therapy are contraindicated.
Refer to the Prescribing Information of these products for a list of their contraindications [see Warnings and Precautions (5.1)]. Hypersensitivity to ezetimibe or any excipient of ZETIA. (4) When used in combination with a statin, fenofibrate, or other LDL-C lowering therapy, ZETIA is contraindicated in patients for whom a statin, fenofibrate, or other LDL-C lowering therapy are contraindicated.
Refer to the Prescribing Information of these products for a list of their contraindications. (4)
US FDA labelDosing: Adult
Dosage and administration (US label) US FDA label
2 DOSAGE AND ADMINISTRATION The recommended dose of ZETIA is 10 mg orally once daily, administered with or without food. If as dose is missed, take the missed dose as soon as possible. Do not double the next dose. Assess LDL-C when clinically appropriate, as early as 4 weeks after initiating ZETIA. Administer ZETIA at least 2 hours before or 4 hours after administration of a bile acid sequestrant [see Drug Interactions (7)]. 10-mg orally once daily, with or without food (2) Administer ZETIA either ≥2 hours before or ≥4 hours after administration of a bile acid sequestrant.
(2) Assess LDL-C when clinically appropriate, as early as 4 weeks after initiating ZETIA. (2)
Dosing: Altered kidney function
8.6 Renal Impairment No dosage adjustment of ZETIA is necessary in patients with renal impairment.
Renal Impairment After a single 10-mg dose of ezetimibe in patients with severe renal disease (n=8; mean CrCl ≤30 mL/min/1.73 m²), the mean AUC values for total ezetimibe, ezetimibe-glucuronide, and ezetimibe were increased approximately 1.5-fold, compared to healthy subjects (n=9).
Kidney-specific guidance from renalcarematters.com: in preparation.
Dosing: Hepatic impairment
8.7 Hepatic Impairment ZETIA is not recommended for use in patients with moderate to severe hepatic impairment (Child-Pugh B or C) due to the unknown effects of the increased exposure to ezetimibe [see Clinical Pharmacology (12.3)].
US FDA labelDosing: Pediatric
Pediatric use (US label) US FDA label
8.4 Pediatric Use The safety and effectiveness of ZETIA in combination with a statin as an adjunct to diet to reduce LDL-C have been established in pediatric patients 10 years of age and older with HeFH. Use of ZETIA for this indication is based on a double-blind, placebo-controlled clinical trial in 248 pediatric patients (142 males and 106 postmenarchal females) 10 years of age and older with HeFH [see Clinical Studies (14)].
In this limited controlled trial, there was no significant effect on growth or sexual maturation in the adolescent males or females, or on menstrual cycle length in females. The safety and effectiveness of ZETIA in combination with a statin, and other LDL-C lowering therapies, to reduce LDL-C have been established in pediatric patients 10 years of age and older with HoFH.
Use of ZETIA for this indication is based on a 12-week double-blind, placebo-controlled clinical trial followed by an uncontrolled extension period in 7 pediatric patients 11 years of age and older with HoFH [see Clinical Studies (14)]. The safety and effectiveness of ZETIA as an adjunct to diet for the reduction of elevated sitosterol and campesterol levels have been established in adults and pediatric patients 9 years of age and older with homozygous familial sitosterolemia.
Use of ZETIA for this indication is based on an 8-week double-blind, placebo-controlled clinical trial in 4 patients 9 years of age and older with homozygous sitosterolemia with elevated plasma sitosterol levels (>5 mg/dL) [see Clinical Studies (14)]. The safety and effectiveness of ZETIA have not been established in pediatric patients younger than 10 years of age with HeFH or HoFH, in pediatric patients younger than 9 years of age with homozygous familial sitosterolemia, or in pediatric patients with other types of hyperlipidemia.
Dosing: Older adult
Geriatric use (US label) US FDA label
8.5 Geriatric Use Of the 2,396 patients who received ZETIA in clinical trials, 669 (28%) were 65 years of age and older, and 111 (5%) were 75 years of age and older. Of the 11,308 patients who received ZETIA in combination with a statin in clinical trials, 3587 (32%) were 65 years of age and older, and 924 (8%) were 75 years of age and older [see Clinical Studies (14)].
No overall differences in safety or effectiveness of ZETIA have been observed between patients 65 years of age and older and younger patients. No clinically meaningful differences in the pharmacokinetics of ezetimibe were observed in geriatric patients compared to younger adult patients [see Clinical Pharmacology (12.3)].
Dosage forms
Philippines
- Tablet: 10 mg
Registered products in the Philippines
11 products registered with the Food and Drug Administration (FDA) Philippines list Ezetimibe as the generic name. Registration status changes; confirm a product's current status on the FDA portal before relying on it.
All registered products11
| Package insert | |||||||
|---|---|---|---|---|---|---|---|
ExelzioEzetimibe | 10 mg TabletAlu/Alu Blister Pack x 10's (Box of 30's) | RxVAT-exempt | KRKA, d.d., Novo MestoSlovenia | UNILAB, Inc. | DRP-12893 | Oct 27, 2027 | |
EzeGetEzetimibe | 10 mg TabletAlu/Alu Blister Pack x 7's (Box of 70's) | RxVAT-exempt | Hetero Labs Limited (Unit III)India | 2MG IncorporatedImporter: Camber Pharmaceuticals, Inc. | DRP-11354-01 | Mar 3, 2027 | |
EzemibeEzetimibe | 10 mg tabletAlu-Alu blister pack x 10’s (Box of 30's) | RxVAT-exempt | Medisure Laborartories Pakistan (Pvt.) Ltd.Pakistan | EuroAsia Pharmaceuticals Inc. | DRP-10899 | Dec 13, 2031 | |
EzetrolEzetimibe | 10 mg TabletAclar/PVC/Alu Blister Pack x 10's (Box of 30's) | RxVAT-exempt | MSD International GmbH (Singapore Branch)Singapore | Organon (Philippines) Incorporated | DRP-18714 | Aug 25, 2031 | |
EzetrolEzetimibe | 10mg TabletAclar/PVC/Alu Blister Pack x 10's (Box of 30's); Aclar/PVC/Alu Blister Pack x 5's (Box of 5's as Physician's Sample); Aclar/PVC/Alu Blister Pack x 10's (Box of 10's as Physician's Sample) | RxVAT-exempt | MSD International GmbH (Puerto Rico Branch) LLCUSA | Importer: Organon (Philippines) Incorporated | DRP-6251 | Mar 10, 2029 | |
EzgenEzetimibe | 10 mg TabletAlu/Alu Blister Pack x 10's (Box of 30's) | RxVAT-exempt | Lloyd Laboratories Inc.Philippines | Trader: Innogen Pharamaceuticals, Inc | DRP-18291 | Jun 4, 2031 | |
EzidrilEzetimibe | 10 mg TabletAlu/Alu Blister Pack X 10'S | RxVAT-exempt | Lloyd Laboratories Inc.Philippines | Trader: Aldril Pharmaceuticals, Inc. | DRP-18290 | Jun 4, 2031 | |
EzitinEzetimibe | 10 mg TabletAlu/Alu blister pack x 7's (Box of 70's) | RxVAT-exempt | Hetero Labs LimitedIndia | Camber Pharmaceuticals, Inc. | DRP-11354 | Mar 3, 2027 | |
LedipsaEzetimibe | 10 mg tabletCold Form Alu-Alu Blister Pack x 15's (Box of 30's) | RxVAT-exempt | Lupin Limited - Unit 2India | Importer: Lupin Philippines Inc. | DR-XY45875 | May 10, 2027 | |
Saphzettige10Ezetimibe | 10 mg TabletAlu/Alu Blister Pack X 10's (Box of 30's and 100's) | RxVAT-exempt | Genom Biotech Pvt. Ltd.India | Nelpa Lifesciences, Inc. | DRP-18236 | Jun 2, 2031 | |
Zetlow-10Ezetimibe | 10 mg TabletAlu/Alu Blister x 7's (Box of 70's) | RxVAT-exempt | Hetero Labs Limited (Unit III)India | Torrent Pharma Philippines IncImporter: Camber Pharmaceuticals, Inc. | DRP-11354-02 | Mar 3, 2027 |
Source: FDA Philippines product registration database. "Valid until" is the registration validity date listed by the FDA; a past date may mean a renewal is pending. Package insert links point to files published by the FDA.
United States (label)
Dosage forms and strengths (US label) US FDA label
3 DOSAGE FORMS AND STRENGTHS Tablets: 10-mg white to off-white, capsule-shaped, and debossed with "414" on one side. Tablets: 10 mg (3)
Warnings/Precautions
- Risks Associated with Combination Treatment with a Statin, Fenofibrate, or Other LDL-C Lowering Therapies: Refer to the Prescribing Information of these products for a description of their risks including, but not limited to, the warnings and precautions. (5.1)
- Liver Enzyme Abnormalities and Monitoring: Increases in serum transaminases have been reported with use of ZETIA. Perform liver enzyme testing as clinically indicated and consider withdrawal of ZETIA if increases in ALT or AST ≥3 × ULN persist. (5.2)
- Skeletal Muscle Effects (e.g., Myopathy and Rhabdomyolysis): ZETIA may cause myopathy and rhabdomyolysis. In post-marketing reports, most patients who developed rhabdomyolysis were taking a statin or other agents known to be associated with an increased risk of rhabdomyolysis, such as fibrates. If myopathy is suspected, discontinue ZETIA and other concomitant medications, as appropriate. (5.3)
5.1 Risks Associated with Combination Treatment with a Statin, Fenofibrate, or Other LDL-C…
5.1 Risks Associated with Combination Treatment with a Statin, Fenofibrate, or Other LDL-C Lowering Therapies If ZETIA is administered with a statin, fenofibrate, or other LDL-C lowering therapies, refer to the Prescribing Information of these products for a description of their risks including, but not limited to, the warnings and precautions [see Contraindications (4)].
5.2 Liver Enzymes
5.2 Liver Enzymes Increases in serum transaminases have been reported with use of ZETIA [see Adverse Reactions (6.1)]. In controlled clinical combination studies of ZETIA initiated concurrently with a statin, the incidence of consecutive elevations (≥3 × ULN) in hepatic transaminase levels was 1.3% for patients treated with ZETIA administered with statins and 0.4% for patients treated with statins alone.
Perform liver enzyme testing as clinically indicated and consider withdrawal of ZETIA if increases in ALT or AST ≥3 × ULN persist.
5.3 Myopathy/Rhabdomyolysis
5.3 Myopathy/Rhabdomyolysis ZETIA may cause myopathy [muscle pain, tenderness, or weakness associated with elevated creatine kinase (CK)] and rhabdomyolysis [see Adverse Reactions (6.1)]. In post-marketing reports, most patients who developed rhabdomyolysis were taking a statin or other agents known to be associated with an increased risk of rhabdomyolysis, such as fibrates.
If myopathy is suspected, discontinue ZETIA and other concomitant medications, as appropriate.
Drug interactions
Drug interactions (US label) US FDA label
7 DRUG INTERACTIONS Table 3 includes a list of drugs with clinically important drug interactions when administered concomitantly with ZETIA and instructions for preventing or managing them. Table 3: Clinically Important Drug Interactions with ZETIA Cyclosporine Clinical Impact: Concomitant use of ZETIA and cyclosporine increases ezetimibe and cyclosporine concentrations.
The degree of increase in ezetimibe exposure may be greater in patients with severe renal insufficiency [see Clinical Pharmacology (12.3)]. Intervention: Monitor cyclosporine concentrations in patients receiving ZETIA and cyclosporine. In patients treated with cyclosporine, weigh the potential effects of the increased exposure to ezetimibe from concomitant use against the benefits of alterations in lipid levels provided by ZETIA.
Fibrates Clinical Impact: Both fenofibrate and ezetimibe may increase cholesterol excretion into the bile, leading to cholelithiasis. Co-administration of ZETIA with fibrates other than fenofibrate is not recommended [see Adverse Reactions (6.1)]. Intervention: If cholelithiasis is suspected in a patient receiving ZETIA and fenofibrate, gallbladder studies are indicated, and alternative lipid-lowering therapy should be considered.
Bile Acid Sequestrants Clinical Impact: Concomitant cholestyramine administration decreased the mean exposure of total ezetimibe. This may result in a reduction of efficacy [see Clinical Pharmacology (12.3)]. Intervention: In patients taking a bile acid sequestrant, administer ZETIA at least 2 hours before or 4 hours after the bile acid sequestrant [see Dosage and Administration (2)].
Cyclosporine: Combination increases exposure of ZETIA and cyclosporine. Cyclosporine concentrations should be monitored in patients taking ZETIA concomitantly. (7) Fibrates: Coadministration of ZETIA with fibrates other than fenofibrate is not recommended until use in patients is adequately studied. If cholelithiasis is suspected in a patient receiving ZETIA and fenofibrate, gallbladder studies are indicated, and alternative lipid-lowering therapy should be considered.
(7) Bile Acid Sequestrants: Cholestyramine combination decreases exposure of ZETIA. (7)
Adverse reactions
- The following serious adverse reactions are discussed in greater detail in other sections of the label: Liver enzyme abnormalities [see Warnings and Precautions (5.2)] Rhabdomyolysis and myopathy [see Warnings and Precautions (5.3)] Common adverse reactions in clinical trials: ZETIA administered alone (incidence ≥2% and greater than placebo): upper respiratory tract infection, diarrhea, arthralgia, sinusitis, pain in extremity, fatigue, and influenza. (6.1)
- ZETIA coadministered with a statin (incidence ≥2% and greater than statin alone): nasopharyngitis, myalgia, upper respiratory tract infection, arthralgia, diarrhea, back pain, influenza, pain in extremity, and fatigue. (6.1)
- To report SUSPECTED ADVERSE REACTIONS, contact Organon LLC, a subsidiary of Organon & Co., at 1-844-674-3200 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1 Clinical Trials Experience
6.1 Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in clinical practice. Monotherapy In 10 double-blind, placebo-controlled clinical trials, 2,396 patients with primary hyperlipidemia (age range 9 to 86 years; 50% female, 90% White, 5% Black or African American, 2% Asian, 3% other races; 3% identified as Hispanic or Latino ethnicity) and elevated LDL-C were treated with ZETIA 10 mg daily for a median treatment duration of 12 weeks (range 0 to 39 weeks).
Adverse reactions reported in ≥2% of patients treated with ZETIA and at an incidence greater than placebo in placebo-controlled studies of ZETIA are shown in Table 1. TABLE 1: Adverse Reactions Occurring ≥2% and Greater than Placebo in ZETIA-treated Patients Adverse Reaction Placebo (%) n = 1,159 ZETIA 10 mg (%) n = 2,396 Upper respiratory tract infection 2.5 4.3 Diarrhea 3.7 4.1 Arthralgia 2.2 3.0 Sinusitis 2.2 2.8 Pain in extremity 2.5 2.7 Fatigue 1.5 2.4 Influenza 1.5 2.0 Combination with a Statin In 28 double-blind, controlled (placebo or active-controlled) clinical trials, 11,308 patients with primary hyperlipidemia (age range 10 to 93 years, 48% female, 85% White, 7% Black or African American, 3% Asian, 5% other races; 4% identified as Hispanic or Latino ethnicity) and elevated LDL-C were treated with ZETIA 10 mg/day concurrently with or added to on-going statin therapy for a median treatment duration of 8 weeks (range 0 to 112 weeks).
The incidence of consecutive increased transaminases (≥3 × ULN) was higher in patients receiving ZETIA administered with statins (1.3%) than in patients treated with statins alone (0.4%). Adverse reactions reported in ≥2% of patients treated with ZETIA + statin and at an incidence greater than statin are shown in Table 2.
TABLE 2: Adverse Reactions Occurring ≥2% in ZETIA-treated Patients Coadministered with a Statin and at an Incidence Greater than Statin Adverse Reaction All Statins All Statins = all doses of all statins (%) n = 9,361 ZETIA + All Statins (%) n = 11,308 Nasopharyngitis 3.3 3.7 Myalgia 2.7 3.2 Upper respiratory tract infection 2.8 2.9 Arthralgia 2.4 2.6 Diarrhea 2.2 2.5 Back pain 2.3 2.4 Influenza 2.1 2.2 Pain in extremity 1.9 2.1 Fatigue 1.6 2.0 Combination with Fenofibrate This clinical trial involving 625 patients with mixed dyslipidemia (age range 20 to 76 years; 44% female, 79% White, 1% Black or African American, 20% other races; 11% identified as Hispanic or Latino ethnicity) treated for up to 12 weeks and 576 patients treated for up to an additional 48 weeks evaluated coadministration of ZETIA and fenofibrate. Incidence rates for clinically important elevations (≥3 × ULN, consecutive) in hepatic transaminase levels were 4.5% and 2.7% for fenofibrate monotherapy (n=188) and ZETIA coadministered with fenofibrate (n=183), respectively, adjusted for treatment exposure.
Corresponding incidence rates for cholecystectomy were 0.6% and 1.7% for fenofibrate monotherapy and ZETIA coadministered with fenofibrate, respectively [see Drug Interactions (7)].
6.2 Post-Marketing Experience
6.2 Post-Marketing Experience Because the reactions below are reported voluntarily from a population of uncertain size, it is generally not possible to reliably estimate their frequency or establish a causal relationship to drug exposure. The following additional adverse reactions have been identified during post-approval use of ZETIA: Blood Disorders: thrombocytopenia Gastrointestinal Disorders: abdominal pain; pancreatitis; nausea Hepatobiliary Disorders: elevations in liver transaminases, including elevations more than 5 X ULN; hepatitis; cholelithiasis; cholecystitis Immune System Disorders: Hypersensitivity reactions including: anaphylaxis, angioedema, rash, and urticaria Musculoskeletal Disorders: elevated creatine phosphokinase; myopathy/rhabdomyolysis Nervous System Disorders: dizziness; paresthesia; depression; headache Skin and Subcutaneous Tissue Disorders: erythema multiforme
Adverse reaction frequency tables (US label) US FDA label
| Adverse Reaction | Placebo (%) n = 1,159 | ZETIA 10 mg (%) n = 2,396 |
|---|---|---|
| Upper respiratory tract infection | 2.5 | 4.3 |
| Diarrhea | 3.7 | 4.1 |
| Arthralgia | 2.2 | 3.0 |
| Sinusitis | 2.2 | 2.8 |
| Pain in extremity | 2.5 | 2.7 |
| Fatigue | 1.5 | 2.4 |
| Influenza | 1.5 | 2.0 |
| Adverse Reaction | All StatinsAll Statins = all doses of all statins (%) n = 9,361 | ZETIA + All Statins (%) n = 11,308 |
|---|---|---|
| Nasopharyngitis | 3.3 | 3.7 |
| Myalgia | 2.7 | 3.2 |
| Upper respiratory tract infection | 2.8 | 2.9 |
| Arthralgia | 2.4 | 2.6 |
| Diarrhea | 2.2 | 2.5 |
| Back pain | 2.3 | 2.4 |
| Influenza | 2.1 | 2.2 |
| Pain in extremity | 1.9 | 2.1 |
| Fatigue | 1.6 | 2.0 |
Pregnancy considerations
Pregnancy (US label) US FDA label
8.1 Pregnancy Risk Summary There are insufficient data on ezetimibe use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. In animal reproduction studies, no adverse developmental effects were observed in pregnant rats and rabbits orally administered ezetimibe during the period of organogenesis at doses that resulted in up to 10 and 150 times, respectively, the human exposure at the MRHD, based on AUC (see Data).
ZETIA should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. When ZETIA is administered with a statin, refer to the Prescribing Information for the statin. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Animal Data In oral (gavage) embryo-fetal development studies of ezetimibe conducted in rats (gestation days 6-15) and rabbits (gestation days 7-19), there was no evidence of maternal toxicity or embryolethal effects at the doses tested (250, 500, 1,000 mg/kg/day). In rats, increased incidences of common fetal skeletal findings (extra pair of thoracic ribs, unossified cervical vertebral centra, shortened ribs) were observed at 1,000 mg/kg/day (~10 times the human exposure at 10 mg daily based on AUC 0-24hr for total ezetimibe).
In rabbits treated with ezetimibe, an increased incidence of extra thoracic ribs was observed at 1,000 mg/kg/day (150 times the human exposure at 10 mg daily based on AUC 0-24hr for total ezetimibe). The animal-to-human exposure multiple for total ezetimibe at the no-observed effect level was 6 times for rat and 134 times for rabbit.
Fetal exposure to ezetimibe (conjugated and unconjugated) was confirmed in subsequent placental transfer studies conducted using a maternal dose of 1,000 mg/kg/day. The fetal maternal plasma exposure ratio (total ezetimibe) was 1.5 for rats on gestation day 20 and 0.03 for rabbits on gestation day 22. The effect of ezetimibe on prenatal and postnatal development and maternal function was evaluated in pregnant rats at doses of 100, 300 or 1,000 mg/kg/day from gestation day 6 through lactation day 21.
No maternal toxicity or adverse developmental outcomes were observed up to and including the highest dose tested (17 times the human exposure at 10 mg daily based on AUC 0-24hr for total ezetimibe). Multiple-dose studies of ezetimibe given in combination with statins in rats and rabbits during organogenesis resulted in higher ezetimibe and statin exposures.
Reproductive findings occurred at lower doses in combination therapy compared to monotherapy.
Mechanism of action
12.1 Mechanism of Action Ezetimibe reduces blood cholesterol by inhibiting the absorption of cholesterol by the small intestine. The molecular target of ezetimibe has been shown to be the sterol transporter, Niemann-Pick C1-Like 1 (NPC1L1), which is involved in the intestinal uptake of cholesterol and phytosterols. Ezetimibe localizes at the brush border of the small intestine and inhibits the absorption of cholesterol, leading to a decrease in the delivery of intestinal cholesterol to the liver.
This causes a reduction of hepatic cholesterol stores and an increase in LDL receptors, resulting in clearance of cholesterol from the blood.
US FDA labelPharmacodynamics
Pharmacodynamics (US label) US FDA label
12.2 Pharmacodynamics ZETIA reduces total cholesterol (total-C), LDL-C, apolipoprotein (Apo) B, and non-high-density lipoprotein cholesterol (non-HDL-C) in patients with hyperlipidemia. In a 2-week clinical trial in 18 hypercholesterolemic patients, ZETIA inhibited intestinal cholesterol absorption by 54%, compared with placebo. ZETIA had no clinically meaningful effect on the plasma concentrations of the fat-soluble vitamins A, D, and E (in a trial of 113 patients) and did not impair adrenocortical steroid hormone production (in a trial of 118 patients).
Pharmacokinetics
Elimination Metabolism Ezetimibe is primarily metabolized in the small intestine and liver via glucuronide conjugation (a phase II reaction) with subsequent biliary and renal excretion.
Both ezetimibe and ezetimibe-glucuronide are eliminated from plasma with a half-life of approximately 22 hours for both ezetimibe and ezetimibe-glucuronide.
Excretion Following oral administration of 14 C-ezetimibe (20 mg) to human subjects, total ezetimibe (ezetimibe + ezetimibe-glucuronide) accounted for approximately 93% of the total radioactivity in plasma.
Pharmacokinetics (US label) US FDA label
12.3 Pharmacokinetics Absorption After oral administration, ezetimibe is absorbed and extensively conjugated to a pharmacologically active phenolic glucuronide (ezetimibe-glucuronide). After a single 10-mg dose of ZETIA to fasted adults, mean ezetimibe peak plasma concentrations (C max) of 3.4 to 5.5 ng/mL were attained within 4 to 12 hours (T max).
Ezetimibe-glucuronide mean C max values of 45 to 71 ng/mL were achieved between 1 and 2 hours (T max). There was no substantial deviation from dose proportionality between 5 and 20 mg. The absolute bioavailability of ezetimibe cannot be determined, as the compound is virtually insoluble in aqueous media suitable for injection.
Effect of Food Concomitant food administration (high-fat or non-fat meals) had no effect on the extent of absorption of ezetimibe when administered as ZETIA 10-mg tablets. The C max value of ezetimibe was increased by 38% with consumption of high-fat meals. Distribution Ezetimibe and ezetimibe-glucuronide are highly bound (>90%) to human plasma proteins.
Elimination Metabolism Ezetimibe is primarily metabolized in the small intestine and liver via glucuronide conjugation (a phase II reaction) with subsequent biliary and renal excretion. Minimal oxidative metabolism (a phase I reaction) has been observed in all species evaluated. In humans, ezetimibe is rapidly metabolized to ezetimibe-glucuronide.
Ezetimibe and ezetimibe-glucuronide are the major drug-derived compounds detected in plasma, constituting approximately 10 to 20% and 80 to 90% of the total drug in plasma, respectively. Both ezetimibe and ezetimibe-glucuronide are eliminated from plasma with a half-life of approximately 22 hours for both ezetimibe and ezetimibe-glucuronide.
Plasma concentration-time profiles exhibit multiple peaks, suggesting enterohepatic recycling. Excretion Following oral administration of 14 C-ezetimibe (20 mg) to human subjects, total ezetimibe (ezetimibe + ezetimibe-glucuronide) accounted for approximately 93% of the total radioactivity in plasma. After 48 hours, there were no detectable levels of radioactivity in the plasma.
Approximately 78% and 11% of the administered radioactivity were recovered in the feces and urine, respectively, over a 10-day collection period. Ezetimibe was the major component in feces and accounted for 69% of the administered dose, while ezetimibe-glucuronide was the major component in urine and accounted for 9% of the administered dose.
Specific Populations Geriatric Patients In a multiple-dose trial with ezetimibe given 10 mg once daily for 10 days, plasma concentrations for total ezetimibe were about 2-fold higher in older (≥65 years) healthy subjects compared to younger subjects. However, the difference in plasma concentrations is not clinically meaningful.
Gender In a multiple-dose trial with ezetimibe given 10 mg once daily for 10 days, plasma concentrations for total ezetimibe were slightly higher (<20%) in females than in males. Race Based on a meta-analysis of multiple-dose pharmacokinetic studies, there were no pharmacokinetic differences between Black and White subjects.
Studies in Asian subjects indicated that the pharmacokinetics of ezetimibe were similar to those seen in White subjects. Renal Impairment After a single 10-mg dose of ezetimibe in patients with severe renal disease (n=8; mean CrCl ≤30 mL/min/1.73 m²), the mean AUC values for total ezetimibe, ezetimibe-glucuronide, and ezetimibe were increased approximately 1.5-fold, compared to healthy subjects (n=9).
Hepatic Impairment After a single 10-mg dose of ezetimibe, the mean AUC for total ezetimibe was increased approximately 1.7-fold in patients with mild hepatic impairment (Child-Pugh score 5 to 6), compared to healthy subjects. The mean AUC values for total ezetimibe and ezetimibe were increased approximately 3- to 4-fold and 5- to 6-fold, respectively, in patients with moderate (Child-Pugh score 7 to 9) or severe hepatic impairment (Child-Pugh score 10 to 15).
In a 14-day, multiple-dose trial (10 mg daily) in patients with moderate hepatic impairment, the mean AUC values for total ezetimibe and ezetimibe were increased approximately 4-fold on Day 1 and Day 14 compared to healthy subjects [see Use in Specific Populations (8.7)]. Drug Interactions ZETIA had no significant effect on a series of probe drugs (caffeine, dextromethorphan, tolbutamide, and IV midazolam) known to be metabolized by cytochrome P450 (1A2, 2D6, 2C8/9 and 3A4) in a “cocktail” trial of twelve healthy adult males.
This indicates that ezetimibe is neither an inhibitor nor an inducer of these cytochrome P450 isozymes, and it is unlikely that ezetimibe will affect the metabolism of drugs that are metabolized by these enzymes. TABLE 4: Effect of Coadministered Drugs on Total Ezetimibe Coadministered Drug and Dosing Regimen Total Ezetimibe Based on 10-mg dose of ezetimibe.
Change in AUC Change in C max Cyclosporine-stable dose required (75-150 mg BID) Post-renal transplant patients with mild impaired or normal renal function. In a different trial, a renal transplant patient with severe renal insufficiency (creatinine clearance of 13.2 mL/min/1.73 m²) who was receiving multiple medications, including cyclosporine, demonstrated a 12-fold greater exposure to total ezetimibe compared to healthy subjects., See Drug Interactions (7). ↑240% ↑290% Fenofibrate, 200 mg QD, 14 days ↑48% ↑64% Gemfibrozil, 600 mg BID, 7 days ↑64% ↑91% Cholestyramine, 4 g BID, 14 days ↓55% ↓4% Aluminum & magnesium hydroxide combination antacid, single dose Supralox, 20 mL. ↓4% ↓30% Cimetidine, 400 mg BID, 7 days ↑6% ↑22% Glipizide, 10 mg, single dose ↑4% ↓8% Statins Lovastatin 20 mg QD, 7 days ↑9% ↑3% Pravastatin 20 mg QD, 14 days ↑7% ↑23% Atorvastatin 10 mg QD, 14 days ↓2% ↑12% Rosuvastatin 10 mg QD, 14 days ↑13% ↑18% Fluvastatin 20 mg QD, 14 days ↓19% ↑7% TABLE 5: Effect of Ezetimibe Coadministration on Systemic Exposure to Other Drugs Coadministered Drug and its Dosage Regimen Ezetimibe Dosage Regimen Change in AUC of Coadministered Drug Change in C max of Coadministered Drug Warfarin, 25-mg single dose on Day 7 10 mg QD, 11 days ↓2% (R-warfarin) ↓4% (S-warfarin) ↑3% (R-warfarin) ↑1% (S-warfarin) Digoxin, 0.5-mg single dose 10 mg QD, 8 days ↑2% ↓7% Gemfibrozil, 600 mg BID, 7 days See Drug Interactions (7). 10 mg QD, 7 days ↓1% ↓11% Ethinyl estradiol & Levonorgestrel, QD, 21 days 10 mg QD, days 8-14 of 21d oral contraceptive cycle Ethinyl estradiol 0% Levonorgestrel 0% Ethinyl estradiol ↓9% Levonorgestrel ↓5% Glipizide, 10 mg on Days 1 and 9 10 mg QD, days 2-9 ↓3% ↓5% Fenofibrate, 200 mg QD, 14 days 10 mg QD, 14 days ↑11% ↑7% Cyclosporine, 100-mg single dose Day 7 20 mg QD, 8 days ↑15% ↑10% Statins Lovastatin 20 mg QD, 7 days 10 mg QD, 7 days ↑19% ↑3% Pravastatin 20 mg QD, 14 days 10 mg QD, 14 days ↓20% ↓24% Atorvastatin 10 mg QD, 14 days 10 mg QD, 14 days ↓4% ↑7% Rosuvastatin 10 mg QD, 14 days 10 mg QD, 14 days ↑19% ↑17% Fluvastatin 20 mg QD, 14 days 10 mg QD, 14 days ↓39% ↓27%
Formulary and pricing (Philippines)
Check availability
Prices and stock vary by branch; renalcarematters.com does not sell medicines or receive payment from pharmacies.
Related guides
Guides on renalcarematters.com for this medicine, for patients and clinicians.
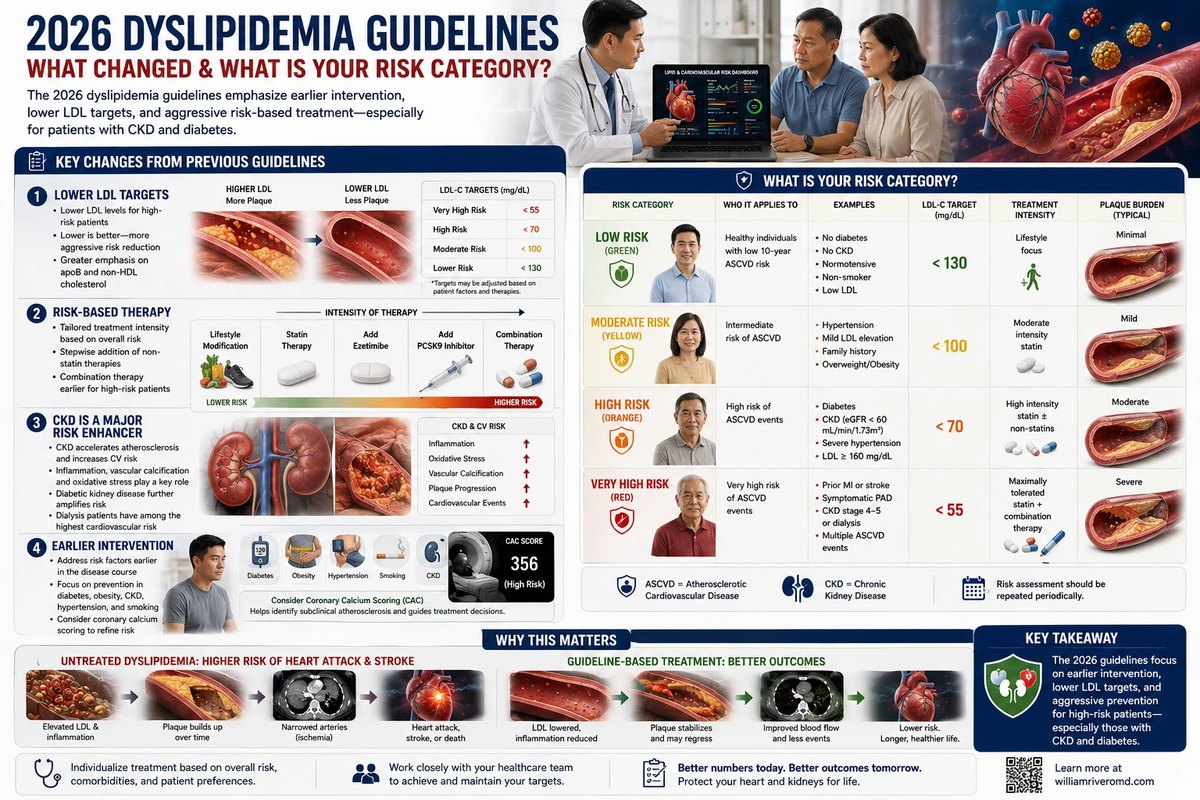 GuideDyslipidemia: 2026 Guidelines Update2026 cholesterol guidelines for CKD and dialysis patients — LDL targets, statin safety in kidney disease, non-statin options, and cardiovascular risk reduction.
 GuideVitamin B1 and Niacin in Kidney CareHow to recognize low vitamin B1 (thiamine) when eating fails, including belly pain and high lactate on dialysis, and why high-dose niacin no longer belongs beside a statin, with options for statin intolerance in kidney disease.
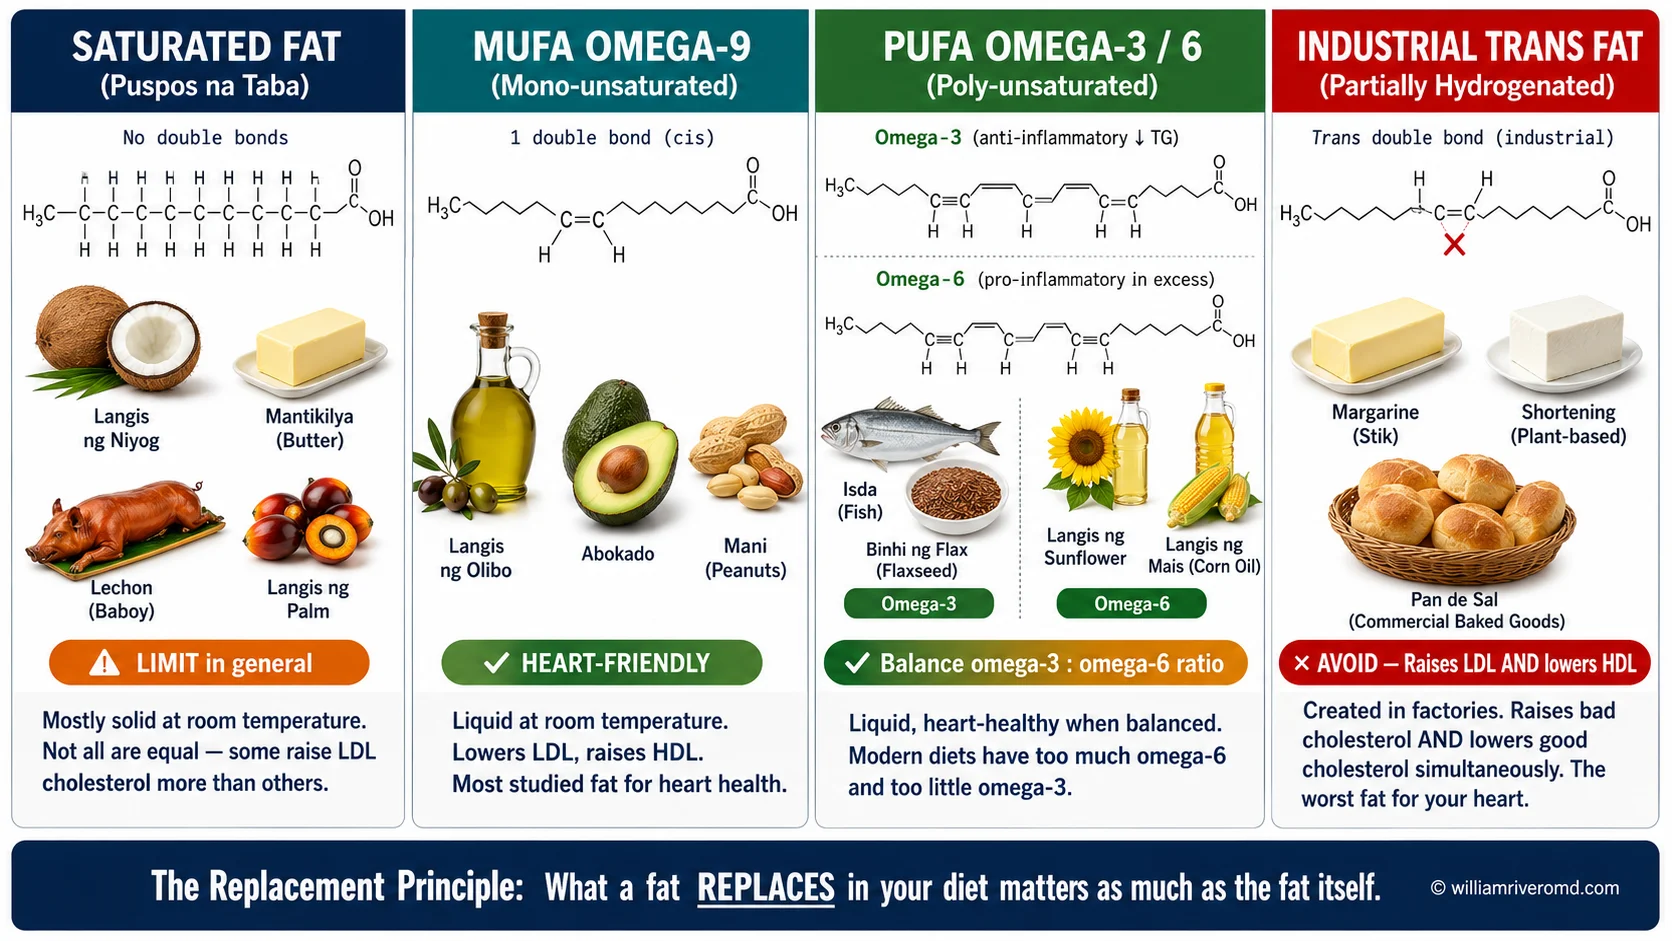 GuideCooking Oils & Fats: An Evidence-Based Patient GuideEvidence-based guide to cooking oils and fats for Filipino patients — CKD, diabetes, dyslipidemia, and general health. Rice bran oil, EVOO, coconut oil, and more. Dr. William Gregory M. Rivero, MD.
 GuideHeart & Kidney Connection — When Protecting One Saves BothWhy heart and kidney disease occur together — how each organ affects the other, cardiorenal syndrome, and strategies to protect both in Filipino patients.
References
- U.S. Food and Drug Administration. Zetia · Organon LLC [US FDA-approved label, version 8, November 25, 2025]. Via DailyMed/openFDA. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=174e45e0-45bb-48b7-9e60-8f6cfc1d22bb
- Food and Drug Administration Philippines. Verification portal (product registrations). https://verification.fda.gov.ph
This page shows official label and registry text only; no renalcarematters.com clinical summary has been approved for it yet.
Last updated: .