Use: Labeled indications
- As an adjunct to diet to reduce elevated low density lipoprotein cholesterol (LDL-C): In adults with primary hyperlipidemia.
Full indications and usage US FDA label
1 INDICATIONS AND USAGE VYTORIN VYTORIN ® is a combination of simvastatin and ezetimibe indicated: As an adjunct to diet to reduce elevated low density lipoprotein cholesterol (LDL-C): In adults with primary hyperlipidemia. In adults and pediatric patients aged 10 years and older with heterozygous familial hypercholesterolemia (HeFH).
As an adjunct to other LDL-C-lowering therapies to reduce elevated LDL-C in adults with homozygous familial hypercholesterolemia (HoFH). Simvastatin Simvastatin, when used as a component of VYTORIN, is indicated to reduce the risk of total mortality by reducing risk of coronary heart disease death, non-fatal myocardial infarction and stroke, and the need for coronary and non-coronary revascularization procedures in adults with established coronary heart disease, cerebrovascular disease, peripheral vascular disease, and/or diabetes, who are at high risk of coronary heart disease events.
VYTORIN is a combination of ezetimibe, a dietary cholesterol absorption inhibitor, and simvastatin, an HMG-CoA reductase inhibitor (statin) indicated: (1) As an adjunct to diet to reduce elevated low density lipoprotein cholesterol (LDL-C): In adults with primary hyperlipidemia. In adults and pediatric patients aged 10 years and older with heterozygous familial hypercholesterolemia (HeFH).
As an adjunct to other LDL-C lowering therapies to reduce LDL-C in adults with homozygous familial hypercholesterolemia (HoFH). Simvastatin Simvastatin, when used as a component of VYTORIN, is indicated to reduce the risk of total mortality by reducing risk of coronary heart disease death, non-fatal myocardial infarction and stroke, and the need for coronary and non-coronary revascularization procedures in adults with established coronary heart disease, cerebrovascular disease, peripheral vascular disease, and/or diabetes, who are at high risk of coronary heart disease events.
Contraindications
4 CONTRAINDICATIONS VYTORIN is contraindicated in the following conditions: Concomitant use of strong CYP3A4 inhibitors (select azole anti-fungals, macrolide antibiotics, anti-viral medications, and nefazodone) [see Drug Interactions (7.1)]. Concomitant use of cyclosporine, danazol, or danazol [see Drug Interactions (7.1)].
Acute liver failure or decompensated cirrhosis [see Warnings and Precautions (5.3)]. Hypersensitivity to simvastatin, ezetimibe, or any excipients in VYTORIN. Hypersensitivity reactions, including anaphylaxis, angioedema, and Stevens-Johnson syndrome, have been reported [see Adverse Reactions (6.2)]. Concomitant use of strong CYP3A4 inhibitors (select azole anti-fungals, macrolide antibiotics, anti-viral medications and nefazodone).
(4) Concomitant use of cyclosporine, danazol or gemfibrozil. (4) Acute liver failure or decompensated cirrhosis. (4) Hypersensitivity to simvastatin, ezetimibe or any excipient of VYTORIN. (4)
US FDA labelDosing: Adult
- Important Dosage and Administration Information: (2.1)
- Take VYTORIN orally once daily in the evening with or without food. Maximum recommended dosage is VYTORIN 10/40 mg once daily. VYTORIN 10/80 mg daily dosage is restricted to patients who have been taking VYTORIN 10/80 mg daily chronically (e.g., for 12 months or more) without evidence of muscle toxicity. For patients that require a high-intensity statin or are unable to achieve their LDL-C goal receiving VYTORIN 10/40 mg daily, prescribe alternative LDL-C-lowering treatment. If as dose is missed, take the missed dose as soon as possible. Do not double the next dose. Assess LDL-C when clinically appropriate, as early as 2 weeks after initiating VYTORIN, and adjust the dosage if necessary. Adults: Recommended dosage range of 10/10 mg to 10/40 mg once daily. (2.2)
- See full prescribing information for VYTORIN dosage modifications due to drug interactions. (2.3)
- Patients with Renal Impairment: Doses exceeding 10/20 mg should be used with caution and close monitoring in patients with moderate to severe renal impairment. (2.4)
2.1 Important Dosage and Administration Information
2.1 Important Dosage and Administration Information Take VYTORIN orally once daily in the evening with or without food. The maximum recommended dosage is VYTORIN 10/40 mg once daily. The VYTORIN 10/80 mg daily dosage is restricted to adult patients who have been taking VYTORIN 10/80 mg daily chronically (e.g., for 12 months or more) without evidence of muscle toxicity [see Warnings and Precautions (5.1)].
For patients that require a high-intensity statin or are unable to achieve their LDL-C goal receiving VYTORIN 10/40 mg daily, prescribe alternative LDL-C-lowering treatment. If as dose is missed, take the missed dose as soon as possible. Do not double the next dose. Assess LDL-C when clinically appropriate, as early as 4 weeks after initiating VYTORIN, and adjust the dosage if necessary.
2.2 Recommended Dosage in Adult Patients
2.2 Recommended Dosage in Adult Patients The recommended dosage range of VYTORIN 10/10 mg to 10/40 mg once a day.
2.3 Recommended Dosage in Pediatric Patients 10 Years of Age and Older with HeFH
2.3 Recommended Dosage in Pediatric Patients 10 Years of Age and Older with HeFH The recommended dosage range of VYTORIN 10/10 mg to 10/40 mg once a day.
2.4 Recommended Dosage in Patients with Renal Impairment
2.4 Recommended Dosage in Patients with Renal Impairment Renal impairment is a risk factor for statin-associated myopathy. Doses of VYTORIN exceeding 10/20 mg should be used with caution and close monitoring in patients with moderate to severe renal impairment [see Warnings and Precautions (5.1) and Use in Specific Populations (8.6)].
There are no dosage adjustment recommendations for patients with mild renal impairment.
2.5 Dosage Modifications Due to Drug Interactions
2.5 Dosage Modifications Due to Drug Interactions Concomitant use of VYTORIN with the following drugs requires dosage modification of VYTORIN [see Warnings and Precautions (5.1) and Drug Interactions (7.1)]. Patients taking Lomitapide Reduce the dosage of VYTORIN by 50%. Do not exceed VYTORIN 10/20 mg once daily (or 10/40 mg once daily for patients who have previously taken VYTORIN 10/80 mg daily chronically while taking lomitapide) [see Dosage and Administration (2.1)].
Patients taking Verapamil, Diltiazem, or Dronedarone Do not exceed VYTORIN 10/10 mg once daily. Patients taking Amiodarone, Amlodipine, or Ranolazine Do not exceed VYTORIN 10/20 mg once daily. Patients taking Bile Acid Sequestrants In patients taking a bile acid sequestrant, administer VYTORIN at least 2 hours before or 4 hours after the bile acid sequestrant.
Dosing: Altered kidney function
2.4 Recommended Dosage in Patients with Renal Impairment Renal impairment is a risk factor for statin-associated myopathy. Doses of VYTORIN exceeding 10/20 mg should be used with caution and close monitoring in patients with moderate to severe renal impairment [see Warnings and Precautions (5.1) and Use in Specific Populations (8.6)]. There are no dosage adjustment recommendations for patients with mild renal impairment.
8.6 Renal Impairment Renal impairment is a risk factor for myopathy and rhabdomyolysis. Monitor all patients with renal impairment for development of myopathy. Doses of VYTORIN exceeding 10/20 mg should be used with caution and close monitoring in patients with moderate to severe renal impairment [see Dosage and Administration (2.4) and Warnings and Precautions (5.1)].
In the SHARP trial of 9270 patients with moderate to severe renal impairment (6247 non-dialysis patients with median serum creatinine 2.5 mg/dL and median estimated glomerular filtration rate 25.6 mL/min/1.73 m², and 3023 dialysis patients), the incidence of serious adverse events, adverse events leading to discontinuation of trial treatment, or adverse events of special interest (musculoskeletal adverse events, liver enzyme abnormalities, incident cancer) was similar between patients ever assigned to VYTORIN 10/20 mg (n=4650) or placebo (n=4620) during a median follow-up of 4.9 years.
Renal Impairment Ezetimibe After a single 10-mg dose of ezetimibe in patients with severe renal disease (n=8; mean CrCl ≤30 mL/min/1.73 m²), the mean AUC for total ezetimibe and ezetimibe increased approximately 1.5-fold, compared to healthy subjects (n=9). Simvastatin Pharmacokinetic studies with another statin having a similar principal route of elimination to that of simvastatin have suggested that for a given dose level higher systemic exposure may be achieved in patients with severe renal impairment (as measured by creatinine clearance).
Kidney-specific guidance from renalcarematters.com: in preparation.
Dosing: Hepatic impairment
8.7 Hepatic Impairment VYTORIN is contraindicated in patients with acute liver failure or decompensated cirrhosis. [See Contraindications (4) and Warnings and Precautions (5.3).]
US FDA labelDosing: Pediatric
Pediatric use (US label) US FDA label
8.4 Pediatric Use The safety and effectiveness of ezetimibe in combination with a statin as an adjunct to diet to reduce LDL-C have been established in pediatric patients 10 years of age and older with HeFH. Use of VYTORIN for this indication is based on a double-blind, placebo-controlled clinical trial in 248 pediatric patients (142 males and 106 postmenarchal females) 10 years of age and older with HeFH [see Clinical Studies (14)].
In this limited controlled trial, there was no significant effect on growth or sexual maturation in the adolescent males or females, or on menstrual cycle length in females. The safety and effectiveness of VYTORIN have not been established in pediatric patients younger than 10 years of age with HeFH, or in pediatric patients with other types of hyperlipidemia.
Dosing: Older adult
Geriatric use (US label) US FDA label
8.5 Geriatric Use Advanced age (≥65 years) is a risk factor for VYTORIN-associated myopathy and rhabdomyolysis. Dose selection for an elderly patient should be cautious, recognizing the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy and the higher risk of myopathy.
Monitor geriatric patients receiving VYTORIN for the increased risk of myopathy [see Warnings and Precautions (5.1)]. Of the 10,189 patients who received VYTORIN in clinical studies, 3242 (32%) were 65 and older (this included 844 (8%) who were 75 and older). No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in responses between the elderly and younger patients but greater sensitivity of some older individuals cannot be ruled out.
Administration
2.1 Important Dosage and Administration Information Take VYTORIN orally once daily in the evening with or without food. The maximum recommended dosage is VYTORIN 10/40 mg once daily. The VYTORIN 10/80 mg daily dosage is restricted to adult patients who have been taking VYTORIN 10/80 mg daily chronically (e.g., for 12 months or more) without evidence of muscle toxicity [see Warnings and Precautions (5.1) ] . For patients that require a high-intensity statin or are unable to achieve their LDL-C goal receiving VYTORIN 10/40 mg daily, prescribe alternative LDL-C-lowering treatment. If as dose is missed, take the missed dose as soon as possible. Do not double the next dose. Assess LDL-C when clinically appropriate, as early as 4 weeks after initiating VYTORIN, and adjust the dosage if necessary.
US FDA labelDosage forms
Philippines
- Tablet: 10 mg/10 mg, 10 mg/20 mg, 10 mg/40 mg, 80 mg/10 mg
Registered products in the Philippines
5 products registered with the Food and Drug Administration (FDA) Philippines list Ezetimibe + Simvastatin as the generic name. Registration status changes; confirm a product's current status on the FDA portal before relying on it.
All registered products5
| Package insert | |||||||
|---|---|---|---|---|---|---|---|
Stadavas PlusSimvastatin + Ezetimibe | 80 mg/ 10 mg TabletOPA/Al/PVC-A1 Blister Pack x 10's (Box of 100's) | RxVAT-exempt | Watson Pharma Pvt. Ltd.India | STADA Philippines Inc | DR-XY48441 | Oct 28, 2027 | |
VytocorEzetimibe + Simvastatin | 10 mg/40 mg TabletWhite opaque PVC/PE/PVDC-Alu Blister Pack x 10's (Box of 30's) | RxVAT-exempt | Duopharma (M) Sdn. Bhd.Malaysia | DB (Philippines), Inc. | DR-XY48725 | May 11, 2028 | |
VytorinEzetimibe + Simvastatin | 10 mg/40 mg TabletPVC/Aclar with Aluminum lidding Blister Pack x 10's (Box of 30's) | RxVAT-exempt | MSD International GmbH (Singapore Branch)Singapore 637766 | Importer: Organon (Philippines) Incorporated | DRP-6254 | Sep 6, 2031 | |
VytorinEzetimibe + Simvastatin | 10mg/10mg TabletAlu-Alu Blister Pack x 10's (Box of 30's) | RxVAT-exempt | MSD International GmbH (Singapore Branch)Singapore 637766 | Importer: Organon (Philippines) Incorporated | DRP-6253 | Sep 13, 2031 | |
VytorinEzetimibe + Simvastatin | 10mg/20mg TabletPVC/Aclar with aluminum lidding blister pack x 10's (Box of 30's); PVC/Aclar with aluminum lidding blister pack x 5's (as Physician's Sample) (Box of 5's) | RxVAT-exempt | MSD International GmbH (Singapore Branch)Singapore 637766 | Organon (Philippines) Incorporated | DRP-6252 | Sep 6, 2031 |
Source: FDA Philippines product registration database. "Valid until" is the registration validity date listed by the FDA; a past date may mean a renewal is pending. Package insert links point to files published by the FDA.
United States (label)
Dosage forms and strengths (US label) US FDA label
3 DOSAGE FORMS AND STRENGTHS VYTORIN tablets: 10/10, (ezetimibe 10 mg and simvastatin 10 mg tablets) are white to off-white capsule-shaped and debossed with “311” on one side. 10/20, (ezetimibe 10 mg and simvastatin 20 mg tablets) are white to off-white capsule-shaped and debossed with “312” on one side. 10/40, (ezetimibe 10 mg and simvastatin 40 mg tablets) are white to off-white capsule-shaped and debossed with “313” on one side. 10/80, (ezetimibe 10 mg and simvastatin 80 mg tablets) are white to off-white capsule-shaped and debossed with “315” on one side. Tablets (ezetimibe mg/simvastatin mg): 10/10, 10/20, 10/40, 10/80 (3)
Warnings/Precautions
- Myopathy and Rhabdomyolysis: Risk factors include age 65 years or greater, uncontrolled hypothyroidism, renal impairment, concomitant use with certain other drugs, and higher VYTORIN dosage. Chinese patients may be at higher risk for myopathy. Discontinue VYTORIN if markedly elevated CK levels occur or myopathy is diagnosed or suspected. Temporarily discontinue VYTORIN in patients experiencing an acute or serious condition at high risk of developing renal failure secondary to rhabdomyolysis. Inform patients of the risk of myopathy and rhabdomyolysis when starting or increasing VYTORIN dosage. Instruct patients to promptly report unexplained muscle pain, tenderness, or weakness, particularly if accompanied by malaise or fever. (5.1)
- Immune-Mediated Necrotizing Myopathy (IMNM): Rare reports of IMNM, an autoimmune myopathy, have been reported. Discontinue VYTORIN if IMNM is suspected. (5.2)
- Hepatic Dysfunction: Increases in serum transaminases have occurred, some persistent. Rare reports of fatal and non-fatal hepatic failure have occurred. Consider testing liver enzyme before initiating therapy and as clinically indicated thereafter. If serious hepatic injury with clinical symptoms and/or hyperbilirubinemia or jaundice occurs, promptly discontinue VYTORIN. (5.3)
5.1 Myopathy and Rhabdomyolysis
5.1 Myopathy and Rhabdomyolysis VYTORIN may cause myopathy and rhabdomyolysis. Acute kidney injury secondary to myoglobinuria and rare fatalities have occurred as a result of rhabdomyolysis in patients treated with statins, including VYTORIN. In clinical trials of 24,747 simvastatin-treated patients with a median follow-up of 4 years, the incidence of myopathy, defined as unexplained muscle weakness, pain, or tenderness accompanied by creatinine kinase (CK) increases greater than ten times the upper limit of normal (10 X ULN), were approximately 0.03%, 0.08%, and 0.61% in patients treated with simvastatin 20 mg, 40 mg, and 80 mg daily, respectively.
In another clinical trial of 12,064 simvastatin-treated patients (with a history of myocardial infarction) with a mean follow-up of 6.7 years, the incidences of myopathy in patients taking simvastatin 20 mg and 80 mg daily were approximately 0.02% and 0.9%, respectively. The incidences of rhabdomyolysis (defined as myopathy with a CK >40 X ULN) in patients taking simvastatin 20 mg and 80 mg daily were approximately 0% and 0.4%, respectively [see Adverse Reactions (6.1)].
In the Trial of Heart and Renal Protection (SHARP), 9270 patients with chronic kidney disease were allocated to receive VYTORIN 10/20 mg daily (n=4650) or placebo (n=4620). During a median follow-up period of 4.9 years, the incidence of myopathy (defined as unexplained muscle weakness or pain with a serum creatine kinase [CK] >10 times upper limit of normal [ULN]) was 0.2% for VYTORIN and 0.1% for placebo: the incidence of rhabdomyolysis (defined as myopathy with a CK > 40 times ULN) was 0.09% for VYTORIN and 0.02% for placebo.
In postmarketing experience with ezetimibe, cases of myopathy and rhabdomyolysis have been reported. Most patients who developed rhabdomyolysis were taking a statin prior to initiating ezetimibe. However, rhabdomyolysis has been reported with ezetimibe monotherapy and with the addition of ezetimibe to agents known to be associated with increased risk of rhabdomyolysis, such as fibric acid derivatives.
VYTORIN and a fenofibrate, if taking concomitantly, should both be immediately discontinued if myopathy is diagnosed or suspected. Risk Factors for Myopathy Risk factors for myopathy include age 65 years or greater, uncontrolled hypothyroidism, renal impairment, concomitant use with certain other drugs (including other lipid-lowering therapies), and higher VYTORIN dosage; Chinese patients on VYTORIN may be at higher risk for myopathy [see Contraindications (4), Drug Interactions (7.1), and Use in Specific Populations (8.8)].
The risk of myopathy is increased by elevated plasma levels of simvastatin and simvastatin acid. The risk is also greater in patients taking VYTORIN 80 mg daily compared with patients taking lower VYTORIN dosages and compared with patients using other statins with similar or greater LDL-C-lowering efficacy [see Adverse Reactions (6.1)].
Steps to Prevent or Reduce the Risk of Myopathy and Rhabdomyolysis The concomitant use of strong CYP3A4 inhibitors with VYTORIN is contraindicated. If short-term treatment with strong CYP3A4 inhibitors is required, temporarily suspend VYTORIN during the duration of strong CYP3A4 inhibitor treatment. The concomitant use of VYTORIN with gemfibrozil, cyclosporine, or danazol is also contraindicated [see Contraindications (4) and Drug Interactions (7.1)].
VYTORIN dosage modifications are recommended for patients taking lomitapide, verapamil, diltiazem, dronedarone, amiodarone, amlodipine or ranolazine [see Dosage and Administration (2.5)]. VYTORIN use should be temporarily suspended in patients taking daptomycin. Lipid modifying doses (≥1 gram/day) of niacin, fibrates, colchicine, and grapefruit juice may also increase the risk of myopathy and rhabdomyolysis [see Drug Interactions (7.1)].
Use the 80 mg daily dosage of VYTORIN only in patients who have been taking simvastatin 80 mg daily chronically without evidence of muscle toxicity [see Dosage and Administration (2.1)]. If patients treated with VYTORIN 80 mg are prescribed an interacting drug that increases the risk for myopathy and rhabdomyolysis, switch to an alternate statin [see Drug Interactions (7.1)].
Discontinue VYTORIN if markedly elevated CK levels occur or if myopathy is either diagnosed or suspected. Muscle symptoms and CK increases may resolve if VYTORIN is discontinued. Temporarily discontinue VYTORIN in patients experiencing an acute or serious condition at high risk of developing renal failure secondary to rhabdomyolysis, e.g., sepsis; shock; severe hypovolemia; major surgery; trauma; severe metabolic, endocrine, or electrolyte disorders; or uncontrolled epilepsy.
Inform patients of the risk of myopathy and rhabdomyolysis when starting or increasing the VYTORIN dosage and advise patients receiving VYTORIN 80 mg of the increased risk of myopathy and rhabdomyolysis. Instruct patients to promptly report any unexplained muscle pain, tenderness or weakness, particularly if accompanied by malaise or fever.
5.2 Immune-Mediated Necrotizing Myopathy
5.2 Immune-Mediated Necrotizing Myopathy There have been rare reports of immune-mediated necrotizing myopathy (IMNM), an autoimmune myopathy, associated with statin use, including reports of recurrence when the same or a different statin was administered. IMNM is characterized by proximal muscle weakness and elevated serum creatine kinase that persist despite discontinuation of statin treatment; positive anti-HMG CoA reductase antibody; muscle biopsy showing necrotizing myopathy without significant inflammation; and improvement with immunosuppressive agents.
Additional neuromuscular and serologic testing may be necessary. Treatment with immunosuppressive agents may be required. Discontinue VYTORIN if IMNM is suspected.
5.3 Hepatic Dysfunction
5.3 Hepatic Dysfunction Increases in serum transaminases have been reported with use of VYTORIN [see Adverse Reactions (6.1)]. In most cases, these changes appeared soon after initiation, were transient, were not accompanied by symptoms, and resolved or improved on continued therapy or after a brief interruption in therapy.
Marked persistent increases of hepatic transaminases have also occurred with VYTORIN. There have been rare postmarketing reports of fatal and non-fatal hepatic failure in patients taking statins, including VYTORIN. In three placebo-controlled, 12-week trials, the incidence of consecutive elevations (≥3 X ULN) in serum transaminases was 1.7% overall for patients treated with VYTORIN and appeared to be dose-related with an incidence of 2.6% for patients treated with VYTORIN 10/80.
In controlled long-term (48-week) extensions, which included both newly-treated and previously-treated patients, the incidence of consecutive elevations (≥3 X ULN) in serum transaminases was 1.8% overall and 3.6% for patients treated with VYTORIN 10/80. These elevations in transaminases were generally asymptomatic, not associated with cholestasis, and returned to baseline after discontinuation of therapy or with continued treatment.
In SHARP, 9270 patients with chronic kidney disease were allocated to receive VYTORIN 10/20 mg daily (n=4650), or placebo (n=4620). During a median follow-up period of 4.9 years, the incidence of consecutive elevations of transaminases (>3 X ULN) was 0.7% for VYTORIN and 0.6% for placebo. Patients who consume substantial quantities of alcohol and/or have a history of liver disease may be at increased risk for hepatic injury.
Consider liver enzyme testing before VYTORIN initiation and when clinically indicated thereafter. VYTORIN is contraindicated in patients with acute liver failure or decompensated cirrhosis [see Contraindications (4)]. If serious hepatic injury with clinical symptoms and/or hyperbilirubinemia or jaundice occurs, promptly discontinue VYTORIN.
5.4 Increases in HbA1c and Fasting Serum Glucose Levels
5.4 Increases in HbA1c and Fasting Serum Glucose Levels Increases in HbA1c and fasting serum glucose levels have been reported with statins, including VYTORIN. Optimize lifestyle measures, including regular exercise, maintaining a healthy body weight, and making healthy food choices.
Drug interactions
- VYTORIN See full prescribing information for details regarding concomitant use of VYTORIN with other drugs or grapefruit juice that increase the risk of myopathy and rhabdomyolysis. (2.3, 7.1)
- Cholestyramine: Combination decreases exposure of ezetimibe. (2.3, 7.2)
- Coumarin Anticoagulants: Obtain INR before VYTORIN initiation and monitor INR during VYTORIN dosage initiation or adjustment. (7.3)
- Digoxin: During VYTORIN initiation, monitor digoxin levels. (7.3)
- Fenofibrates: Combination increases exposure of ezetimibe. If cholelithiasis is suspected in a patient receiving ezetimibe and a fenofibrate, gallbladder studies are indicated and alternative lipid-lowering therapy should be considered. (7.3, 12.3)
7.1 Drug
7.1 Drug Interactions that Increase the Risk of Myopathy and Rhabdomyolysis with VYTORIN VYTORIN is a substrate of CYP3A4 and of the transport protein OATP1B1. VYTORIN plasma levels can be significantly increased with concomitant administration of inhibitors of CYP3A4 and OATP1B1. Table 2 includes a list of drugs that increase the risk of myopathy and rhabdomyolysis when used concomitantly with VYTORIN and instructions for preventing or managing them [see Warnings and Precautions (5.1) and Clinical Pharmacology (12.3)].
Table 2: Drug Interactions that Increase the Risk of Myopathy and Rhabdomyolysis with VYTORIN Strong CYP3A4 inhibitors Clinical Impact: Simvastatin is a substrate of CYP3A4. Concomitant use of strong CYP3A4 inhibitors with VYTORIN increases simvastatin exposure and increases the risk of myopathy and rhabdomyolysis, particularly with higher VYTORIN dosages.
Intervention: Concomitant use of strong CYP3A4 inhibitors with VYTORIN is contraindicated [see Contraindications (4)]. If treatment with a CYP3A4 inhibitor is unavoidable, suspend VYTORIN during the course of strong CYP3A4 inhibitor treatment. Examples: Select azole anti-fungals (e.g., itraconazole, ketoconazole, posaconazole, and voriconazole), select macrolide antibiotics (e.g., erythromycin and clarithromycin, telithromycin), select HIV protease inhibitors (e.g., nelfinavir, ritonavir, and darunavir/ritonavir), select HCV protease inhibitors (e.g., boceprevir and telaprevir), cobicistat-containing products, and nefazodone.
Cyclosporine, Danazol, or Gemfibrozil Clinical Impact: The risk of myopathy and rhabdomyolysis is increased with concomitant use of cyclosporine, danazol, or gemfibrozil with VYTORIN. Gemfibrozil may cause myopathy when given alone. Intervention: Concomitant use of cyclosporine, danazol, or gemfibrozil with VYTORIN is contraindicated [see Contraindications (4)].
Amiodarone, Dronedarone, Ranolazine, or Calcium Channel Blockers Clinical Impact: The risk of myopathy and rhabdomyolysis is increased by concomitant use of amiodarone, dronedarone, ranolazine, or calcium channel blockers with VYTORIN. Intervention: For patients taking verapamil, diltiazem, or dronedarone, do not exceed VYTORIN 10/10 mg daily.
For patients taking amiodarone, amlodipine, or ranolazine, do not exceed VYTORIN 10/20 mg daily [see Dosage and Administration (2.3)]. Lomitapide Clinical Impact: Simvastatin exposure is approximately doubled with concomitant use of lomitapide and the risk of myopathy and rhabdomyolysis is increased. Intervention: Reduce the dose of VYTORIN by 50% if initiating lomitapide.
Do not exceed VYTORIN 10/20 mg daily (or VYTORIN 10/40 mg daily for patients who have previously taken VYTORIN 10/80 mg daily chronically) while taking lomitapide [see Dosage and Administration (2.1, 2.3)]. Daptomycin Clinical Impact: Cases of rhabdomyolysis have been reported with simvastatin administered with daptomycin.
Both VYTORIN and daptomycin can cause myopathy and rhabdomyolysis when given alone and the risk of myopathy and rhabdomyolysis may be increased by coadministration. Intervention: If treatment with daptomycin is required, consider temporarily suspending VYTORIN during the course of daptomycin treatment. Niacin Clinical Impact: Cases of myopathy and rhabdomyolysis have been observed with concomitant use of lipid modifying dosages of niacin-containing products (≥1 gram/day niacin) with VYTORIN.
The risk of myopathy is greater in Chinese patients. In a clinical trial (median follow-up 3.9 years) of patients at high risk of CVD and with well-controlled LDL-C levels on simvastatin 40 mg/day with or without ezetimibe 10 mg/day, there was no incremental benefit on cardiovascular outcomes with the addition of lipid-modifying doses of niacin Intervention: Concomitant use of VYTORIN with lipid-modifying dosages of niacin is not recommended in Chinese patients [see Use in Specific Populations (8.8)].
For non-Chinese patients, consider if the benefit of using lipid-modifying doses of niacin concomitantly with VYTORIN outweighs the increased risk of myopathy and rhabdomyolysis. If concomitant use is decided, monitor patients for signs and symptoms of myopathy, particularly during initiation of therapy and during upward dose titration of either drug.
Fibrates (other than Gemfibrozil) Clinical Impact: Fibrates may cause myopathy when given alone. The risk of myopathy and rhabdomyolysis is increased with concomitant use of fibrates with VYTORIN. Intervention: Consider if the benefit of using fibrates concomitantly with VYTORIN outweighs the increased risk of myopathy and rhabdomyolysis.
If concomitant use is decided, monitor patients for signs and symptoms of myopathy, particularly during initiation of therapy and during upward dose titration of either drug. Colchicine Clinical Impact: Cases of myopathy and rhabdomyolysis have been reported with concomitant use of colchicine with VYTORIN. Intervention: Consider if the benefit of using colchicine concomitantly with VYTORIN outweighs the increased risk of myopathy and rhabdomyolysis.
If concomitant use is decided, monitor patients for signs and symptoms of myopathy, particularly during initiation of therapy and during upward dose titration of either drug. Grapefruit Juice Clinical Impact: Grapefruit juice can raise the plasma levels of simvastatin and may increase the risk of myopathy and rhabdomyolysis.
Intervention: Avoid grapefruit juice when taking VYTORIN.
7.2 Drug
7.2 Drug Interactions that Decrease the Efficacy of VYTORIN Table 3 presents drug interactions that may decrease the efficacy of VYTORIN and instructions for preventing or managing them. Table 3: Drug Interactions that Decrease the Efficacy of VYTORIN Bile Acid Sequestrants Clinical Impact: Concomitant cholestyramine administration decreased the mean exposure of total ezetimibe approximately 55%.
The incremental LDL-C reduction due to adding VYTORIN to cholestyramine may be reduced by this interaction [see Clinical Pharmacology (12.3)]. Intervention: In patients taking a bile acid sequestrant, administer VYTORIN at least 2 hours before or at least 4 hours after cholestyramine [see Dosage and Administration (2.3)].
7.3 VYTORIN’s Effect on Other Drugs
7.3 VYTORIN’s Effect on Other Drugs Table 4 presents VYTORIN’s effect on other drugs and instructions for preventing or managing them. Table 4: VYTORIN Effects on Other Drugs Coumarin Anticoagulants Clinical Impact: VYTORIN may potentiate the effect of coumarin anticoagulants and increase the INR. The concomitant use of simvastatin (20 to 40 mg) and coumarin anticoagulants increased the INR from a baseline of 1.7 to 1.8 in healthy subjects and from 2.6 to 3.4 in patients with hyperlipidemia.
There are postmarketing reports of clinically evident bleeding and/or increased INR in patients taking concomitant statins (with or without ezetimibe) and coumarin anticoagulants. Intervention: In patients taking coumarin anticoagulants, obtain an INR before starting VYTORIN and frequently enough after initiation, dose titration, or discontinuation to ensure that no significant alteration in INR occurs.
Once the INR is stable, monitor INR at regularly recommended intervals. Digoxin Clinical Impact: Concomitant use of digoxin with VYTORIN may result in elevated plasma digoxin concentrations [see Clinical Pharmacology (12.3)]. Intervention: Monitor digoxin levels in patients taking digoxin when VYTORIN is initiated. Fenofibrates Clinical Impact: Both ezetimibe and fenofibrates may increase cholesterol excretion into the bile, leading to cholelithiasis.
Intervention: If cholelithiasis is suspected in a patient receiving VYTORIN and a fenofibrate, gallbladder studies are indicated and alternative lipid-lowering therapy should be considered [see the product labeling for fenofibrate and fenofibric acid].
Metabolism and transporters (CYP, P-gp, OATP; US label) US FDA label
In a trial of 12 healthy volunteers, simvastatin at the 80-mg dose had no effect on the metabolism of the probe cytochrome P450 isoform 3A4 (CYP3A4) substrates midazolam and erythromycin.
This indicates that simvastatin is not an inhibitor of CYP3A4 and, therefore, is not expected to affect the plasma levels of other drugs metabolized by CYP3A4.
Simvastatin acid is a substrate of the transport protein OATP1B1.
Concomitant administration of medicinal products that are inhibitors of the transport protein OATP1B1 may lead to increased plasma concentrations of simvastatin acid and an increased risk of myopathy.
For example, cyclosporine has been shown to increase the AUC of statins; although the mechanism is not fully understood, the increase in AUC for simvastatin acid is presumably due, in part, to inhibition of CYP3A4 and/or OATP1B1 [see Drug Interactions (7) ] .
Simvastatin is a substrate for CYP3A4.
Inhibitors of CYP3A4 can raise the plasma levels of HMG-CoA reductase inhibitory activity and increase the risk of myopathy.
( 7.3 , 12.3 ) 7.1 Drug Interactions that Increase the Risk of Myopathy and Rhabdomyolysis with VYTORIN VYTORIN is a substrate of CYP3A4 and of the transport protein OATP1B1.
Adverse reactions
- The following serious adverse reactions are discussed in greater detail in other sections of the label: Myopathy and Rhabdomyolysis [see Warnings and Precautions (5.1)] Immune-Mediated Necrotizing Myopathy [see Warnings and Precautions (5.2)] Hepatic Dysfunction [see Warnings and Precautions (5.3)] Increases in HbA1c and Fasting Serum Glucose Levels [see Warnings and Precautions (5.4)] Common (incidence ≥2% and greater than placebo) adverse reactions in clinical trials: headache, increased ALT, myalgia, upper respiratory tract infection, and diarrhea. (6.1)
- To report SUSPECTED ADVERSE REACTIONS, contact Organon LLC, a subsidiary of Organon & Co., at 1-844-674-3200 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1 Clinical Trials Experience
6.1 Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. VYTORIN In the VYTORIN (ezetimibe and simvastatin) placebo-controlled clinical trials database of 1420 patients (age range 20-83 years, 52% female, 87% White, 3% Black or African American, 3% Asians, 5% other races identified as Hispanic or Latino ethnicity) with a median treatment duration of 27 weeks, 5% of patients on VYTORIN and 2.2% of patients on placebo discontinued due to adverse reactions.
The most commonly reported adverse reactions (incidence ≥2% and greater than placebo) in controlled clinical trials were: headache (5.8%), increased ALT (3.7%), myalgia (3.6%), upper respiratory tract infection (3.6%), and diarrhea (2.8%). The most common adverse reactions in the group treated with VYTORIN that led to treatment discontinuation and occurred at a rate greater than placebo were: increased ALT (0.9%), myalgia (0.6%), increased AST (0.4%), and back pain (0.4%).
VYTORIN has been evaluated for safety in more than 10,189 patients in clinical trials. Table 1 summarizes the frequency of clinical adverse reactions reported in ≥2% of patients treated with VYTORIN (n=1420) and at an incidence greater than placebo from four placebo-controlled trials. Table 1 Includes two placebo-controlled combination studies in which the active ingredients equivalent to VYTORIN were coadministered and two placebo-controlled studies in which VYTORIN was administered.: Adverse Reactions Reported ≥2% of Patients Treated with VYTORIN at an Incidence Greater than Placebo Regardless of Causality % Placebo N = 371 % Ezetimibe 10 mg N = 302 % Simvastatin All doses.
N = 1234 % VYTORIN N = 1420 Headache 5.4 6.0 5.9 5.8 Upper respiratory tract infection 2.7 5.0 5.0 3.6 Myalgia 2.4 2.3 2.6 3.6 Diarrhea 2.2 5.0 3.7 2.8 Pain in extremity 1.3 3.0 2.0 2.3 Influenza 0.8 1.0 1.9 2.3 Study of Heart and Renal Protection In SHARP, 9270 patients were allocated to VYTORIN 10/20 mg daily (n=4650) or placebo (n=4620) for a median follow-up period of 4.9 years. The proportion of patients who permanently discontinued trial treatment as a result of either an adverse event or abnormal safety blood result was 10.4% vs. 9.8% among patients allocated to VYTORIN and placebo, respectively.
Comparing those allocated to VYTORIN vs. placebo, the incidence of myopathy (defined as unexplained muscle weakness or pain with a serum CK >10 times ULN) was 0.2% vs. 0.1% and the incidence of rhabdomyolysis (defined as myopathy with a CK >40 times ULN) was 0.09% vs. 0.02%, respectively. Consecutive elevations of transaminases (>3 X ULN) occurred in 0.7% vs. 0.6%, respectively.
Patients were asked about the occurrence of unexplained muscle pain or weakness at each trial visit: 21.5% vs. 20.9% patients ever reported muscle symptoms in the VYTORIN and placebo groups, respectively. Cancer was diagnosed during the trial in 9.4% vs. 9.5% of patients assigned to VYTORIN and placebo, respectively. Ezetimibe Other adverse reactions reported with ezetimibe in placebo-controlled studies, regardless of causality assessment: Musculoskeletal system disorders: arthralgia; Infections and infestations: sinusitis; Body as a whole – general disorders: fatigue.
Simvastatin In a clinical outcome trial in which 12,064 adult patients with a history of myocardial infarction were treated with simvastatin (mean follow-up 6.7 years), the incidence of myopathy (defined as unexplained muscle weakness or pain with a serum creatine kinase [CK] >10 times (1200 U/L) upper limit of normal [ULN]) in patients taking simvastatin 20 mg and 80 mg daily was approximately 0.02% and 0.9% respectively. The incidence of rhabdomyolysis (defined as myopathy with a CK >40 times ULN) in patients taking simvastatin 20 mg and 80 mg daily was approximately 0% and 0.4%.
The incidence of myopathy and rhabdomyolysis, was highest during the first year and then notably decreased during the subsequent years of treatment. In this trial, patients were carefully monitored and some interacting medicinal products were excluded. Other adverse reactions reported with simvastatin in placebo-controlled clinical trials: atrial fibrillation; vertigo; abdominal pain, constipation, dyspepsia, flatulence, gastritis; eczema, rash; diabetes mellitus; bronchitis, sinusitis, urinary tract infections; asthenia, edema/swelling; and insomnia.
Laboratory Tests Marked persistent increases of hepatic serum transaminases have been noted [see Warnings and Precautions (5.3)]. Elevated alkaline phosphatase and γ-glutamyl transpeptidase have been reported. About 5% of patients taking simvastatin had elevations of CK levels of 3 or more times the normal value on one or more occasions.
This was attributable to the noncardiac fraction of CK [see Warnings and Precautions (5.1)].
6.2 Postmarketing Experience
6.2 Postmarketing Experience The following adverse reactions have been identified during post-approval use of VYTORIN. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Body as Whole: fever, chills, malaise, asthenia Blood and Lymphatic System Disorders: anemia, thrombocytopenia, leukopenia, hemolytic anemia, positive ANA, ESR increase, eosinophilia Gastrointestinal Disorders: pancreatitis, nausea, vomiting Hepatobiliary Disorders: cholelithiasis, cholecystitis, elevations in liver transaminases including elevations more than 5 X ULN, hepatitis/jaundice, fatal and non-fatal hepatic failure Immune System Disorders: hypersensitivity syndrome including: anaphylaxis, angioedema, lupus erythematous-like syndrome, dermatomyositis, vasculitis Musculoskeletal and Connective Tissue Disorders: muscle cramps, immune-mediated necrotizing myopathy, rhabdomyolysis, myalgia, arthralgia, polymyalgia rheumatica, arthritis, elevated creatine phosphokinase Nervous System Disorders: dizziness, depression, paresthesia, peripheral neuropathy, rare reports of cognitive impairment (e.g., memory loss, forgetfulness, amnesia, memory impairment, confusion) associated with statin use.
Cognitive impairment was generally nonserious, and reversible upon statin discontinuation, with variable times to symptom onset (1 day to years) and symptom resolution (median of 3 weeks). There have been rare reports of new-onset or exacerbation of myasthenia gravis, including ocular myasthenia, and reports of recurrence when the same or a different statin was administered.
Skin and Subcutaneous Tissue Disorders: rash, pruritus, alopecia, a variety of skin changes (e.g., nodules, discoloration, dryness of skin/mucous membranes, changes to hair/nails), purpura, lichen planus, urticaria, photosensitivity, flushing, toxic epidermal necrolysis, erythema multiforme, including Stevens-Johnson syndrome. Respiratory and Thoracic: interstitial lung disease, dyspnea Reproductive System Disorders: erectile dysfunction
Adverse reaction frequency tables (US label) US FDA label
| % Placebo N = 371 | % Ezetimibe 10 mg N = 302 | % SimvastatinAll doses. N = 1234 | % VYTORIN N = 1420 | |
|---|---|---|---|---|
| Headache | 5.4 | 6.0 | 5.9 | 5.8 |
| Upper respiratory tract infection | 2.7 | 5.0 | 5.0 | 3.6 |
| Myalgia | 2.4 | 2.3 | 2.6 | 3.6 |
| Diarrhea | 2.2 | 5.0 | 3.7 | 2.8 |
| Pain in extremity | 1.3 | 3.0 | 2.0 | 2.3 |
| Influenza | 0.8 | 1.0 | 1.9 | 2.3 |
Pregnancy considerations
Pregnancy (US label) US FDA label
8.1 Pregnancy VYTORIN Risk Summary Discontinue VYTORIN when pregnancy is recognized. Alternatively, consider the ongoing therapeutic needs of the individual patient. VYTORIN decreases synthesis of cholesterol and possibly other biologically active substances derived from cholesterol; therefore, VYTORIN may cause fetal harm when administered to pregnant patients based on the mechanism of action [see Clinical Pharmacology (12.1)].
In addition, treatment of hyperlipidemia is not generally necessary during pregnancy. Atherosclerosis is a chronic process and the discontinuation of lipid-lowering drugs during pregnancy should have little impact on the outcome of long-term therapy of primary hyperlipidemia for most patients. Available data from case series and prospective and retrospective observational cohort studies over decades of use with statins in pregnant women have not identified a drug-associated risk of major congenital malformations.
Published data from prospective and retrospective observational cohort studies with VYTORIN use in pregnant women are insufficient to determine if there is a drug-associated risk of miscarriage (see Data). In animal reproduction studies, no adverse developmental effects were observed in pregnant rats or rabbits orally administered simvastatin during the period of organogenesis at doses that resulted in 2.5 and 2 times, respectively, the human exposure at the maximum recommended human dosage of 80 mg/day, based on body surface area (mg/m 2).
In animal reproduction studies, no adverse developmental effects were observed in pregnant rats and rabbits orally administered ezetimibe during the period of organogenesis at doses that resulted in up to 10 and 150 times, respectively, the human exposure at the MRHD, based on AUC (see Data). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Human Data Ezetimibe There are insufficient data on ezetimibe use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes.
Simvastatin A Medicaid cohort linkage trial of 1152 statin-exposed pregnant women compared to 886,996 controls did not find a significant teratogenic effect from maternal use of statins in the first trimester of pregnancy, after adjusting for potential confounders – including maternal age, diabetes mellitus, hypertension, obesity, and alcohol and tobacco use – using propensity score-based methods. The relative risk of congenital malformations between the group with statin use and the group with no statin use in the first trimester was 1.07 (95% confidence interval 0.85 to 1.37) after controlling for confounders, particularly pre-existing diabetes mellitus.
There were also no statistically significant increases in any of the organ-specific malformations assessed after accounting for confounders. In the majority of pregnancies, statin treatment was initiated prior to pregnancy and was discontinued at some point in the first trimester when pregnancy was identified. Trial limitations include reliance on physician coding to define the presence of a malformation, lack of control for certain confounders such as body mass index, use of prescription dispensing as verification for the use of a statin, and lack of information on non-live births.
Animal Data Ezetimibe In oral (gavage) embryo-fetal development studies of ezetimibe conducted in rats (gestation days 6-15) and rabbits (gestation days 7-19), there was no evidence of maternal toxicity or embryolethality at any dose tested (250, 500, 1000 mg/kg/day) at exposure equivalent to 10 to 150 times the clinical exposure, based on AUC, in rats and rabbits. In rats, increased incidences of common fetal skeletal findings (extra pair of thoracic ribs, unossified cervical vertebral centra, shortened ribs) were observed at 1000 mg/kg/day (~10 times the human exposure at 10 mg daily based on AUC 0-24hr for total ezetimibe).
In rabbits treated with ezetimibe, an increased incidence of extra thoracic ribs was observed at 1000 mg/kg/day (150 times the human exposure at 10 mg daily based on AUC 0-24hr for total ezetimibe). The animal-to-human exposure multiple for total ezetimibe at the no-observed effect level was 6 times for rat and 134 times for rabbit.
Fetal exposure to ezetimibe (conjugated and unconjugated) was confirmed in subsequent placental transfer studies conducted using a maternal dose of 1000 mg/kg/day. The fetal maternal plasma exposure ratio (total ezetimibe) was 1.5 for rats on gestation day 20 and 0.03 for rabbits on gestation day 22. The effect of ezetimibe on prenatal and postnatal development and maternal function was evaluated in pregnant rats at doses of 100, 300 or 1000 mg/kg/day (gestation day 6 through lactation day 21).
No maternal toxicity or adverse developmental outcomes were observed up to and including the highest dose tested (17 times the human exposure at 10 mg daily based on AUC 0-24hr for total ezetimibe). Multiple-dose studies of ezetimibe given in combination with statins in rats and rabbits during organogenesis resulted in higher ezetimibe and statin exposures.
Reproductive findings occurred at lower doses in combination therapy compared to monotherapy. Simvastatin Simvastatin was given to pregnant rats at doses of 6.25, 12.5 and 25 mg/kg/day (0.6 times, 1.3 times, and 2.5 times, respectively, the maximum recommended dosage of 80 mg/day when normalized to body surface area) from gestation days 6-17 and to pregnant rabbits from gestation days 6-18 at doses of 2.5, 5, and 10 mg/kg/day (0.5 times, 1 times, and 2 times, respectively, the maximum recommended dosage of 80 mg/day when normalized to body surface area).
For both species, there was no evidence of maternal toxicity, or embryolethality. In rats, mean fetal body weights in the 25 mg/kg/day group were decreased 5.4%. Similar fetal body weight effects were not observed in rabbits. Simvastatin doses of 6.25, 12.5 and 25 mg/kg/day (0.6 times, 1.3 times, and 2.5 times, respectively, the maximum recommended dosage of 80 mg/day when normalized to body surface area) were given to pregnant rats from gestation day 15 to lactation day 21.
Slight decreases in maternal body weight gain and pup postnatal day 0 weight were observed in the 25 mg/kg/day dose group. Mean body weight gain of pups during lactation was slightly decreased at doses ≥12.5 mg/kg/day. Post weaning weight, behavior, reproductive performance and fertility of the offspring were not affected at any dose tested.
Placental transfer of simvastatin was not evaluated in rats or rabbits. However, it has been shown that other drugs in this class cross the placenta.
Mechanism of action
12.1 Mechanism of Action VYTORIN Plasma cholesterol is derived from intestinal absorption and endogenous synthesis. VYTORIN contains ezetimibe and simvastatin, two lipid-lowering compounds with complementary mechanisms of action. Ezetimibe Ezetimibe reduces blood cholesterol by inhibiting the absorption of cholesterol by the small intestine.
The molecular target of ezetimibe has been shown to be the sterol transporter, Niemann-Pick C1-Like 1 (NPC1L1), which is involved in the intestinal uptake of cholesterol and phytosterols. Ezetimibe localizes at the brush border of the small intestine and inhibits the absorption of cholesterol, leading to a decrease in the delivery of intestinal cholesterol to the liver.
This causes a reduction of hepatic cholesterol stores and an increase in clearance of cholesterol from the blood. Simvastatin Simvastatin is a prodrug and is hydrolyzed to its active β-hydroxyacid form, simvastatin acid, after administration. Simvastatin acid and its metabolites are inhibitors of HMG-CoA reductase, the rate-limiting enzyme converts HMG-CoA to mevalonate, a precursor of cholesterol.
US FDA labelPharmacodynamics
Pharmacodynamics (US label) US FDA label
12.2 Pharmacodynamics VYTORIN reduces total cholesterol (total-C), LDL-C, apolipoprotein (Apo) B, and non-high-density lipoprotein cholesterol (non-HDL-C) in patients with hyperlipidemia. Ezetimibe In a 2-week clinical trial in 18 hypercholesterolemic patients, ezetimibe inhibited intestinal cholesterol absorption by 54%, compared with placebo.
Ezetimibe had no clinically meaningful effect on the plasma concentrations of the fat-soluble vitamins A, D, and E and did not impair adrenocortical steroid hormone production. Simvastatin Inhibition of HMG-CoA reductase by simvastatin acid accelerates the expression of LDL-receptors, followed by the uptake of LDL-C from blood to the liver, leading to a decrease in plasma LDL-C and total cholesterol.
Sustained inhibition of cholesterol synthesis in the liver also decreases levels of very-low density lipoproteins. The maximum LDL-C reduction of ZOCOR is usually achieved by 4 weeks and is maintained after that.
Pharmacokinetics
Elimination Metabolism Ezetimibe Ezetimibe is primarily metabolized in the small intestine and liver via glucuronide conjugation with subsequent biliary and renal excretion.
Both ezetimibe and ezetimibe-glucuronide are eliminated from plasma with a half-life of approximately 22 hours for both ezetimibe and ezetimibe-glucuronide.
Excretion Ezetimibe Following oral administration of 14 C-ezetimibe (20 mg) to human subjects, total ezetimibe (ezetimibe + ezetimibe-glucuronide) accounted for approximately 93% of the total radioactivity in plasma.
Simvastatin Following an oral dose of 14 C-labeled simvastatin in man, 13% of the dose was excreted in urine and 60% in feces.
Pharmacokinetics (US label) US FDA label
12.3 Pharmacokinetics The results of a bioequivalence trial in healthy subjects demonstrated that the VYTORIN (ezetimibe and simvastatin) 10 mg/10 mg to 10 mg/80 mg combination tablets are bioequivalent to coadministration of corresponding doses of ezetimibe (ZETIA ®) and simvastatin (ZOCOR ®) as individual tablets. Absorption Ezetimibe After oral administration, ezetimibe is absorbed and extensively conjugated to a pharmacologically active phenolic glucuronide (ezetimibe-glucuronide).
Mean maximum plasma concentrations (C max) occur within 1 to 2 hours for ezetimibe-glucuronide and 4 to 12 hours for ezetimibe. The absolute bioavailability of ezetimibe cannot be determined as the compound is virtually insoluble in aqueous media suitable for injection. Simvastatin The availability of the β-hydroxyacid to the systemic circulation following an oral dose of simvastatin was found to be less than 5% of the dose, consistent with extensive hepatic first-pass extraction.
Effect of Food on Oral Absorption Ezetimibe Concomitant food administration (high-fat or non-fat meals) had no effect on the extent of absorption of ezetimibe when administered as 10-mg tablets. The C max value of ezetimibe was increased by 38% with consumption of high-fat meals. Simvastatin Relative to the fasting state, the plasma profiles of both active and total inhibitors of HMG-CoA reductase were not affected when simvastatin was administered immediately before an American Heart Association recommended low-fat meal.
Distribution Ezetimibe Ezetimibe and ezetimibe-glucuronide are highly bound (>90%) to human plasma proteins. Simvastatin Both simvastatin and its β-hydroxyacid metabolite are highly bound (approximately 95%) to human plasma proteins. When radiolabeled simvastatin was administered to rats, simvastatin-derived radioactivity crossed the blood-brain barrier.
Elimination Metabolism Ezetimibe Ezetimibe is primarily metabolized in the small intestine and liver via glucuronide conjugation with subsequent biliary and renal excretion. Minimal oxidative metabolism has been observed in all species evaluated. In humans, ezetimibe is rapidly metabolized to ezetimibe-glucuronide. Ezetimibe and ezetimibe-glucuronide are the major drug-derived compounds detected in plasma, constituting approximately 10 to 20% and 80 to 90% of the total drug in plasma, respectively.
Both ezetimibe and ezetimibe-glucuronide are eliminated from plasma with a half-life of approximately 22 hours for both ezetimibe and ezetimibe-glucuronide. Plasma concentration-time profiles exhibit multiple peaks, suggesting enterohepatic recycling. Simvastatin Simvastatin is a lactone that is readily hydrolyzed in vivo to the corresponding β-hydroxyacid, a potent inhibitor of HMG-CoA reductase.
Inhibition of HMG-CoA reductase is a basis for an assay in pharmacokinetic studies of the β-hydroxyacid metabolites (active inhibitors) and, following base hydrolysis, active plus latent inhibitors (total inhibitors) in plasma following administration of simvastatin. The major active metabolites of simvastatin present in human plasma are the β-hydroxyacid of simvastatin and its 6'-hydroxy, 6'-hydroxymethyl, and 6'-exomethylene derivatives.
Excretion Ezetimibe Following oral administration of 14 C-ezetimibe (20 mg) to human subjects, total ezetimibe (ezetimibe + ezetimibe-glucuronide) accounted for approximately 93% of the total radioactivity in plasma. After 48 hours, there were no detectable levels of radioactivity in the plasma. Approximately 78% and 11% of the administered radioactivity were recovered in the feces and urine, respectively, over a 10-day collection period.
Ezetimibe was the major component in feces and accounted for 69% of the administered dose, while ezetimibe-glucuronide was the major component in urine and accounted for 9% of the administered dose. Simvastatin Following an oral dose of 14 C-labeled simvastatin in man, 13% of the dose was excreted in urine and 60% in feces.
Plasma concentrations of total radioactivity (simvastatin plus 14 C-metabolites) peaked at 4 hours and declined rapidly to about 10% of peak by 12 hours postdose. Specific Populations Geriatric Patients Ezetimibe In a multiple-dose trial with ezetimibe given 10 mg once daily for 10 days, plasma concentrations for total ezetimibe were about 2-fold higher in older (≥65 years) healthy subjects compared to younger subjects.
Simvastatin In a trial including 16 geriatric patients between 70 and 78 years of age who received simvastatin 40 mg/day, the mean plasma level of total inhibitors activity was increased approximately 45% compared with 18 patients between 18-30 years of age. [See Use in Specific Populations (8.5).] Gender Ezetimibe In a multiple-dose trial with ezetimibe given 10 mg once daily for 10 days, plasma concentrations for total ezetimibe were slightly higher (<20%) in females than in males. Race Ezetimibe Based on a meta-analysis of multiple-dose pharmacokinetic studies, there were no pharmacokinetic differences between Black or African American and White subjects.
Studies in Asian subjects indicated that the pharmacokinetics of ezetimibe was similar to those seen in White subjects. Hepatic Impairment Ezetimibe After a single 10-mg dose of ezetimibe, the mean exposure (based on area under the curve [AUC]) to total ezetimibe was increased approximately 1.7-fold in patients with mild hepatic impairment (Child-Pugh score 5 to 6), compared to healthy subjects.
The mean AUC values for total ezetimibe and ezetimibe increased approximately 3- to 4-fold and 5- to 6-fold, respectively, in patients with moderate (Child-Pugh score 7 to 9) or severe hepatic impairment (Child-Pugh score 10 to 15). In a 14-day, multiple-dose trial (10 mg daily) in patients with moderate hepatic impairment, the mean AUC for total ezetimibe and ezetimibe increased approximately 4-fold compared to healthy subjects.
Renal Impairment Ezetimibe After a single 10-mg dose of ezetimibe in patients with severe renal disease (n=8; mean CrCl ≤30 mL/min/1.73 m²), the mean AUC for total ezetimibe and ezetimibe increased approximately 1.5-fold, compared to healthy subjects (n=9). Simvastatin Pharmacokinetic studies with another statin having a similar principal route of elimination to that of simvastatin have suggested that for a given dose level higher systemic exposure may be achieved in patients with severe renal impairment (as measured by creatinine clearance).
Drug Interactions [See also Drug Interactions (7).] No clinically significant pharmacokinetic interaction was seen when ezetimibe was coadministered with simvastatin. No specific pharmacokinetic drug interaction studies with VYTORIN have been conducted other than the following trial with NIASPAN (Niacin extended-release tablets).
Niacin: The effect of VYTORIN (10/20 mg daily for 7 days) on the pharmacokinetics of NIASPAN extended-release tablets (1000 mg for 2 days and 2000 mg for 5 days following a low-fat breakfast) was studied in healthy subjects. The mean C max and AUC of niacin increased 9% and 22%, respectively. The mean C max and AUC of nicotinuric acid increased 10% and 19%, respectively (N=13).
In the same trial, the effect of NIASPAN on the pharmacokinetics of VYTORIN was evaluated (N=15). While concomitant NIASPAN decreased the mean C max of total ezetimibe (1%), and simvastatin (2%), it increased the mean C max of simvastatin acid (18%). In addition, concomitant NIASPAN increased the mean AUC of total ezetimibe (26%), simvastatin (20%), and simvastatin acid (35%).
Cases of myopathy/rhabdomyolysis have been observed with simvastatin coadministered with lipid-modifying doses (≥1 g/day niacin) of niacin-containing products. [See Warnings and Precautions (5.1) and Drug Interactions (7.1).] Cytochrome P450: Ezetimibe had no significant effect on a series of probe drugs (caffeine, dextromethorphan, tolbutamide, and IV midazolam) known to be metabolized by cytochrome P450 (1A2, 2D6, 2C8/9 and 3A4) in a “cocktail” trial of twelve healthy adult males. This indicates that ezetimibe is neither an inhibitor nor an inducer of these cytochrome P450 isozymes, and it is unlikely that ezetimibe will affect the metabolism of drugs that are metabolized by these enzymes.
In a trial of 12 healthy volunteers, simvastatin at the 80-mg dose had no effect on the metabolism of the probe cytochrome P450 isoform 3A4 (CYP3A4) substrates midazolam and erythromycin. This indicates that simvastatin is not an inhibitor of CYP3A4 and, therefore, is not expected to affect the plasma levels of other drugs metabolized by CYP3A4.
Simvastatin acid is a substrate of the transport protein OATP1B1. Concomitant administration of medicinal products that are inhibitors of the transport protein OATP1B1 may lead to increased plasma concentrations of simvastatin acid and an increased risk of myopathy. For example, cyclosporine has been shown to increase the AUC of statins; although the mechanism is not fully understood, the increase in AUC for simvastatin acid is presumably due, in part, to inhibition of CYP3A4 and/or OATP1B1 [see Drug Interactions (7)].
Simvastatin is a substrate for CYP3A4. Inhibitors of CYP3A4 can raise the plasma levels of HMG-CoA reductase inhibitory activity and increase the risk of myopathy. [See Warnings and Precautions (5.1) and Drug Interactions (7.1).] Ezetimibe Table 5 displays the effect of coadministered drugs on total ezetimibe. Table 5: Effect of Coadministered Drugs on Total Ezetimibe Coadministered Drug and Dosing Regimen Total Ezetimibe Based on 10 mg-dose of ezetimibe.
Change in AUC Change in C max Cyclosporine-stable dose required (75-150 mg BID) Post-renal transplant patients with mild impaired or normal renal function. In a different trial, a renal transplant patient with severe renal insufficiency (creatinine clearance of 13.2 mL/min/1.73 m²) who was receiving multiple medications, including cyclosporine, demonstrated a 12-fold greater exposure to total ezetimibe compared to healthy subjects., See 7.
Drug Interactions. ↑240% ↑290% Fenofibrate, 200 mg QD, 14 days ↑48% ↑64% Gemfibrozil, 600 mg BID, 7 days ↑64% ↑91% Cholestyramine, 4 g BID, 14 days ↓55% ↓4% Aluminum & magnesium hydroxide combination antacid, single dose Supralox, 20 mL. ↓4% ↓30% Cimetidine, 400 mg BID, 7 days ↑6% ↑22% Glipizide, 10 mg, single dose ↑4% ↓8% Statins Lovastatin 20 mg QD, 7 days ↑9% ↑3% Pravastatin 20 mg QD, 14 days ↑7% ↑23% Atorvastatin 10 mg QD, 14 days ↓2% ↑12% Rosuvastatin 10 mg QD, 14 days ↑13% ↑18% Fluvastatin 20 mg QD, 14 days ↓19% ↑7% Table 6 displays the effects of ezetimibe coadministration on systemic exposure to other drugs. Table 6: Effect of Ezetimibe Coadministration on Systemic Exposure to Other Drugs Coadministered Drug and its Dosage Regimen Ezetimibe Dosage Regimen Change in AUC of Coadministered Drug Change in C max of Coadministered Drug Warfarin, 25 mg single dose on Day 7 10 mg QD, 11 days ↓2% (R-warfarin) ↓4% (S-warfarin) ↑3% (R-warfarin) ↑1% (S-warfarin) Digoxin, 0.5 mg single dose 10 mg QD, 8 days ↑2% ↓7% Gemfibrozil, 600 mg BID, 7 days See 7.
Drug Interactions. 10 mg QD, 7 days ↓1% ↓11% Ethinyl estradiol & Levonorgestrel, QD, 21 days 10 mg QD, Days 8-14 of 21 day oral contraceptive cycle Ethinyl estradiol 0% Levonorgestrel 0% Ethinyl estradiol ↓9% Levonorgestrel ↓5% Glipizide, 10 mg on Days 1 and 9 10 mg QD, Days 2-9 ↓3% ↓5% Fenofibrate, 200 mg QD, 14 days 10 mg QD, 14 days ↑11% ↑7% Cyclosporine, 100 mg single dose Day 7 20 mg QD, 8 days ↑15% ↑10% Statins Lovastatin 20 mg QD, 7 days 10 mg QD, 7 days ↑19% ↑3% Pravastatin 20 mg QD, 14 days 10 mg QD, 14 days ↓20% ↓24% Atorvastatin 10 mg QD, 14 days 10 mg QD, 14 days ↓4% ↑7% Rosuvastatin 10 mg QD, 14 days 10 mg QD, 14 days ↑19% ↑17% Fluvastatin 20 mg QD, 14 days 10 mg QD, 14 days ↓39% ↓27% Simvastatin Table 7 displays the effects of coadminstration drugs or grapefruit juice on simvastatin systemic exposure [see Drug Interactions (7)]. Table 7: Effect of Coadministered Drugs or Grapefruit Juice on Simvastatin Systemic Exposure Coadministered Drug or Grapefruit Juice Dosing of Coadministered Drug or Grapefruit Juice Dosing of Simvastatin Geometric Mean Ratio (Ratio Results based on a chemical assay except results with propranolol as indicated. with / without coadministered drug) No Effect = 1.00 AUC C max Telithromycin Results could be representative of the following CYP3A4 inhibitors: ketoconazole, erythromycin, clarithromycin, HIV protease inhibitors, and nefazodone. 200 mg QD for 4 days 80 mg simvastatin acid Simvastatin acid refers to the β-hydroxyacid of simvastatin. 12 15 simvastatin 8.9 5.3 Nelfinavir 1250 mg BID for 14 days 20 mg QD for 28 days simvastatin acid simvastatin 6 6.2 Itraconazole 200 mg QD for 4 days 80 mg simvastatin acid 13.1 simvastatin 13.1 Posaconazole 100 mg (oral suspension) QD for 13 days 40 mg simvastatin acid 7.3 9.2 simvastatin 10.3 9.4 200 mg (oral suspension) QD for 13 days 40 mg simvastatin acid 8.5 9.5 simvastatin 10.6 11.4 Gemfibrozil 600 mg BID for 3 days 40 mg simvastatin acid 2.85 2.18 simvastatin 1.35 0.91 Grapefruit Juice The effect of amounts of grapefruit juice between those used in these two studies on simvastatin pharmacokinetics has not been studied.
(high dose) 200 mL of double-strength TID Double-strength: one can of frozen concentrate diluted with one can of water. Grapefruit juice was administered TID for 2 days, and 200 mL together with single dose simvastatin and 30 and 90 minutes following single dose simvastatin on Day 3. 60 mg single dose simvastatin acid 7 simvastatin 16 Grapefruit Juice (low dose) 8 oz (about 237 mL) of single-strength Single-strength: one can of frozen concentrate diluted with 3 cans of water.
Grapefruit juice was administered with breakfast for 3 days, and simvastatin was administered in the evening on Day 3. 20 mg single dose simvastatin acid 1.3 simvastatin 1.9 Verapamil SR 240 mg QD Days 1-7 then 240 mg BID on Days 8-10 80 mg on Day 10 simvastatin acid 2.3 2.4 simvastatin 2.5 2.1 Diltiazem 120 mg BID for 10 days 80 mg on Day 10 simvastatin acid 2.69 2.69 simvastatin 3.10 2.88 Diltiazem 120 mg BID for 14 days 20 mg on Day 14 simvastatin 4.6 3.6 Dronedarone 400 mg BID for 14 days 40 mg QD for 14 days simvastatin acid 1.96 2.14 simvastatin 3.90 3.75 Amiodarone 400 mg QD for 3 days 40 mg on Day 3 simvastatin acid 1.75 1.72 simvastatin 1.76 1.79 Amlodipine 10 mg QD for 10 days 80 mg on Day 10 simvastatin acid 1.58 1.56 simvastatin 1.77 1.47 Ranolazine SR 1000 mg BID for 7 days 80 mg on Day 1 and Days 6-9 simvastatin acid 2.26 2.28 simvastatin 1.86 1.75 Lomitapide 60 mg QD for 7 days 40 mg single dose simvastatin acid 1.7 1.6 simvastatin 2 2 Lomitapide 10 mg QD for 7 days 20 mg single dose simvastatin acid 1.4 1.4 simvastatin 1.6 1.7 Fenofibrate 160 mg QD for 14 days 80 mg QD on Days 8-14 simvastatin acid 0.64 0.89 simvastatin 0.89 0.83 Propranolol 80 mg single dose 80 mg single dose total inhibitor 0.79 ↓ from 33.6 to 21.1 ng∙eq/mL active inhibitor 0.79 ↓ from 7.0 to 4.7 ng∙eq/mL
Formulary and pricing (Philippines)
Check availability
Prices and stock vary by branch; renalcarematters.com does not sell medicines or receive payment from pharmacies.
Related guides
Guides on renalcarematters.com for this medicine, for patients and clinicians.
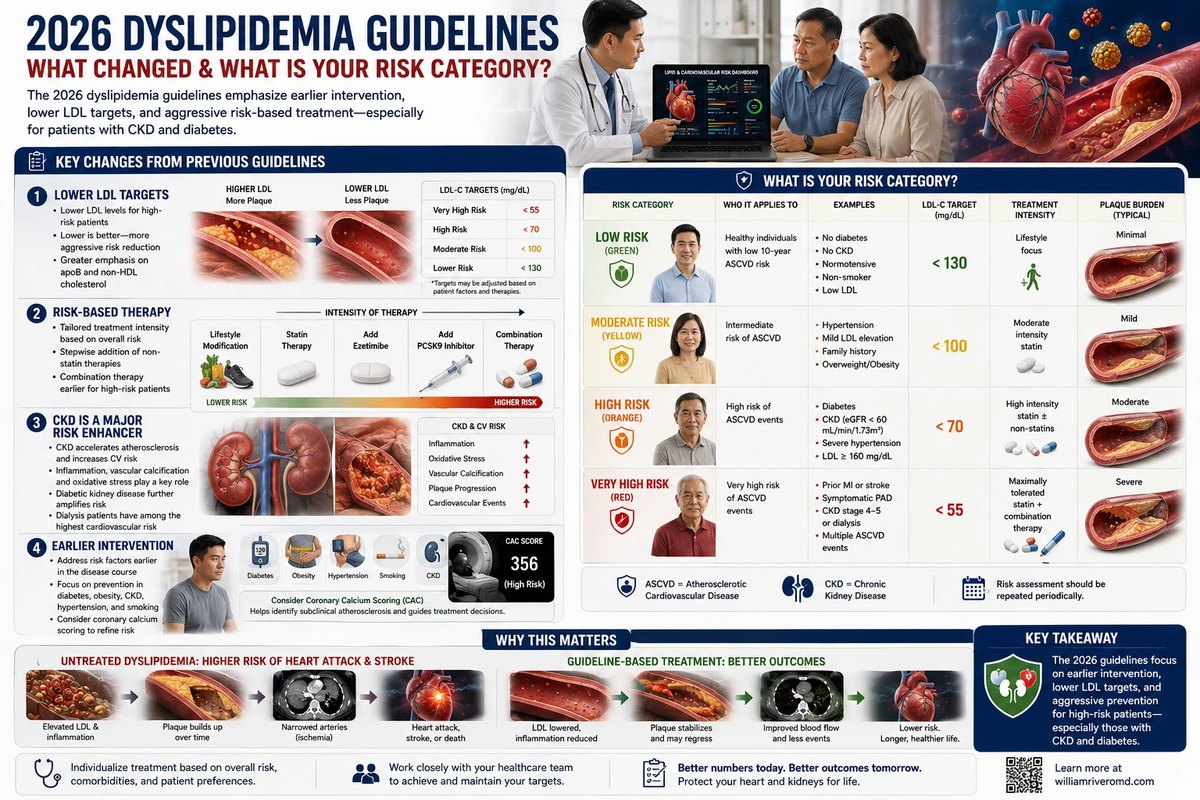 GuideDyslipidemia: 2026 Guidelines Update2026 cholesterol guidelines for CKD and dialysis patients — LDL targets, statin safety in kidney disease, non-statin options, and cardiovascular risk reduction.
 GuideVitamin B1 and Niacin in Kidney CareHow to recognize low vitamin B1 (thiamine) when eating fails, including belly pain and high lactate on dialysis, and why high-dose niacin no longer belongs beside a statin, with options for statin intolerance in kidney disease.
 GuideHeart & Kidney Connection — When Protecting One Saves BothWhy heart and kidney disease occur together — how each organ affects the other, cardiorenal syndrome, and strategies to protect both in Filipino patients.
References
- U.S. Food and Drug Administration. VYTORIN · Organon LLC [US FDA-approved label, version 9, January 21, 2026]. Via DailyMed/openFDA. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=89b860d2-de83-468e-b7e8-76aeec2edca2
- Food and Drug Administration Philippines. Verification portal (product registrations). https://verification.fda.gov.ph
This page shows official label and registry text only; no renalcarematters.com clinical summary has been approved for it yet.
Last updated: .