Use: Labeled indications
- SAPHNELO is indicated for the treatment of adult patients with moderate to severe systemic lupus erythematosus (SLE), who are receiving standard therapy.
Full indications and usage US FDA label
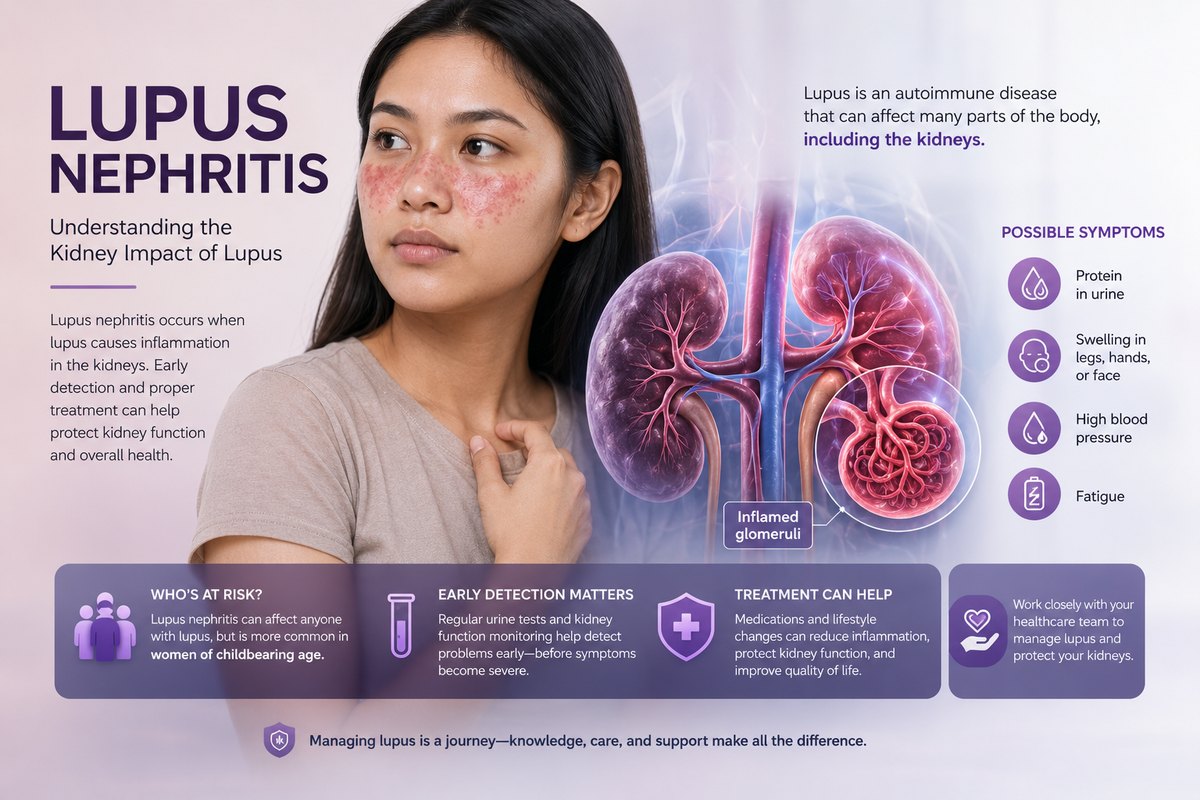
1 INDICATIONS AND USAGE SAPHNELO is indicated for the treatment of adult patients with moderate to severe systemic lupus erythematosus (SLE), who are receiving standard therapy. Limitations of Use The efficacy of SAPHNELO has not been evaluated in patients with severe active lupus nephritis or severe active central nervous system lupus.
Use of SAPHNELO is not recommended in these situations. SAPHNELO is a type I interferon (IFN) receptor antagonist indicated for the treatment of adult patients with moderate to severe systemic lupus erythematosus (SLE), who are receiving standard therapy. (1) Limitations of Use: The efficacy of SAPHNELO has not been evaluated in patients with severe active lupus nephritis or severe active central nervous system lupus.
Use of SAPHNELO is not recommended in these situations. (1)
Contraindications
4 CONTRAINDICATIONS SAPHNELO is contraindicated in patients with a history of anaphylaxis with anifrolumab-fnia [see Warnings and Precautions (5.2)]. SAPHNELO is contraindicated in patients with a history of anaphylaxis with anifrolumab-fnia. (4)
US FDA labelDosing: Adult
- • The recommended intravenous dosage is 300 mg every 4 weeks. (2.2)
- • The recommended subcutaneous dosage is 120 mg once every week. (2.2)
- • See Full Prescribing Information for complete preparation and administration information. (2.3, 2.4)
2.1 Important Administration Information
2.1 Important Administration Information SAPHNELO is intended for use under the guidance of a healthcare provider and may be administered as an intravenous infusion or as a subcutaneous injection. SAPHNELO vials are for intravenous use only and must be diluted prior to intravenous administration [see Dosage and Administration (2.3)].
SAPHNELO prefilled syringe and autoinjector (SAPHNELO PEN) are for subcutaneous use only [see Dosage and Administration (2.4)].
2.2 Recommended Dosage
2.2 Recommended Dosage The recommended dosage of SAPHNELO is:
- 300 mg, administered as an intravenous infusion over a 30‑minute period every 4 weeks; or
- 120 mg, administered as a subcutaneous injection once every week. Missed Dose If a planned intravenous infusion is missed, administer SAPHNELO as soon as possible. Maintain a minimum interval of 14 days between infusions. If a planned subcutaneous dose is missed, instruct the patient to administer SAPHNELO as soon as they remember. Thereafter, instruct the patient to start a new weekly schedule from the day the missed dose was administered or resume dosing on their usual day of administration, providing a minimum interval of 3 days between subcutaneous injections.
2.3 Intravenous Preparation and Administration Instructions
2.3 Intravenous Preparation and Administration Instructions SAPHNELO is supplied as a single-dose vial. Prepare the diluted infusion solution using aseptic technique, by the following procedure: 1. Visually inspect the vial for particulate matter and discoloration. SAPHNELO is a clear to opalescent, colorless to slightly yellow, solution.
Discard the vial if the solution is cloudy, discolored or visible particles are observed. Do not shake the vial. 2. Withdraw and discard 2 mL of solution from a 50 mL or 100 mL 0.9% Sodium Chloride Injection, USP infusion bag. 3. Withdraw 2 mL of solution from the vial of SAPHNELO and add it to the infusion bag. Mix the solution by gentle inversion.
Do not shake. 4. Each vial is intended for one time use only. Discard any unused portion remaining in the vial. 5. Administer the infusion solution immediately after preparation. 6. If the infusion solution is not administered immediately, store the diluted solution of SAPHNELO at room temperature 59°F to 77°F (15°C to 25°C) for up to 4 hours, or refrigerated 36°F to 46°F (2°C to 8°C) for up to 24 hours.
Do not freeze. Protect from light. If refrigerated, allow the diluted SAPHNELO solution to reach room temperature prior to administration. 7. Administer the infusion solution intravenously over a 30-minute period through an infusion line containing a sterile, low-protein binding 0.2 to 15 micron in-line or add-on filter. 8.
To ensure the complete dose of SAPHNELO has been administered, flush the entire infusion line with 25 mL of 0.9% Sodium Chloride Injection, USP at the end of the infusion. 9. Do not co-administer other medicinal products through the same infusion line. 10. Dispose of any unused medicinal product or waste material in accordance with local requirements.
2.4 Subcutaneous Preparation and Administration Instructions
2.4 Subcutaneous Preparation and Administration Instructions The SAPHNELO prefilled syringe and autoinjector (SAPHNELO PEN) are for subcutaneous use. 1. Comprehensive instructions for subcutaneous administration of SAPHNELO using the prefilled syringe or autoinjector are provided in the ‘Instructions for Use’. 2. Patients/caregivers may administer SAPHNELO prefilled syringe/SAPHNELO PEN after proper training in the subcutaneous injection technique and after the healthcare provider determines it is appropriate. 3.
Prior to administration, remove SAPHNELO from the refrigerator and allow it to come to room temperature for 60 minutes. 4. Visually inspect SAPHNELO for particulate matter and discoloration prior to administration. SAPHNELO is a clear to opalescent, colorless to slightly yellow, solution. Discard the prefilled syringe or autoinjector if the solution is cloudy, discolored or visible particles are observed. 5.
Administer the subcutaneous injection into the thigh or abdomen, avoiding the 5 cm (approximately 2 inches) area around the navel. The upper arm can also be used if a healthcare professional or caregiver administers the injection. 6. Do not inject into areas where the skin is tender, bruised, erythematous or hardened. When injecting in the same region, advise patients to use an injection site at least 3 cm (1‑inch) away from the last injection site. 7.
Dispose of any unused medicinal product or waste material in accordance with local requirements.
2.5 Switching Between Intravenous and Subcutaneous Administration
2.5 Switching Between Intravenous and Subcutaneous Administration When transitioning patients from intravenous administration to subcutaneous administration of SAPHNELO, administer the first subcutaneous injection approximately 2 weeks after the last intravenous infusion. When transitioning patients from subcutaneous administration to intravenous administration of SAPHNELO, administer the first intravenous infusion approximately 3 to 4 weeks after the last subcutaneous injection.
Dosing: Altered kidney function
Patients with Renal Impairment: No specific clinical trials have been conducted to investigate the effect of renal impairment on anifrolumab-fnia. Based on population PK analyses, anifrolumab-fnia clearance was comparable in SLE patients with mild (60-89 mL/min/1.73 m²) and moderate (30-59 mL/min/1.73 m²) decrease in eGFR values and patients with normal renal function (≥90 mL/min/1.73 m²). There were no SLE patients with a severe decrease in eGFR or end stage renal disease (<30 mL/min/1.73 m²); anifrolumab-fnia is not cleared renally.
Kidney-specific guidance from renalcarematters.com: in preparation.
Dosing: Pediatric
Pediatric use (US label) US FDA label
8.4 Pediatric Use The safety and efficacy of SAPHNELO in pediatric patients have not been established.
Dosing: Older adult
Geriatric use (US label) US FDA label
8.5 Geriatric Use Of the 952 patients with moderate to severe SLE exposed to SAPHNELO in clinical trials, 3% (n=33) were 65 and over. The number of patients aged 65 years of age and older was not sufficient to determine whether they respond differently from younger adult patients.
Administration
2.1 Important Administration Information SAPHNELO is intended for use under the guidance of a healthcare provider and may be administered as an intravenous infusion or as a subcutaneous injection. SAPHNELO vials are for intravenous use only and must be diluted prior to intravenous administration [see Dosage and Administration (2.3) ] . SAPHNELO prefilled syringe and autoinjector (SAPHNELO PEN) are for subcutaneous use only [see Dosage and Administration (2.4) ] .
2.3 Intravenous Preparation and Administration Instructions SAPHNELO is supplied as a single-dose vial. Prepare the diluted infusion solution using aseptic technique, by the following procedure: 1. Visually inspect the vial for particulate matter and discoloration. SAPHNELO is a clear to opalescent, colorless to slightly yellow, solution. Discard the vial if the solution is cloudy, discolored or visible particles are observed. Do not shake the vial. 2. Withdraw and discard 2 mL of solution from a 50 mL or 100 mL 0.9% Sodium Chloride Injection, USP infusion bag. 3. Withdraw 2 mL of solution from the vial of SAPHNELO and add it to the infusion bag. Mix the solution by gentle inversion. Do not shake. 4. Each vial is intended for one time use only. Discard any unused portion remaining in the vial. 5. Administer the infusion solution immediately after preparation. 6. If the infusion solution is not administered immediately, store the diluted solution of SAPHNELO at room temperature 59°F to 77°F (15°C to 25°C) for up to 4 hours, or refrigerated 36°F to 46°F (2°C to 8°C) for up to 24 hours. Do not freeze. Protect from light. If refrigerated, allow the diluted SAPHNELO solution to reach room temperature prior to administration. 7. Administer the infusion solution intravenously over a 30-minute period through an infusion line containing a sterile, low-protein binding 0.2 to 15 micron in-line or add-on filter. 8. To ensure the complete dose of SAPHNELO has been administered, flush the entire infusion line with 25 mL of 0.9% Sodium Chloride Injection, USP at the end of the infusion. 9. Do not co-administer other medicinal products through the same infusion line. 10. Dispose of any unused medicinal product or waste material in accordance with local requirements .
2.4 Subcutaneous Preparation and Administration Instructions The SAPHNELO prefilled syringe and autoinjector (SAPHNELO PEN) are for subcutaneous use. 1. Comprehensive instructions for subcutaneous administration of SAPHNELO using the prefilled syringe or autoinjector are provided in the ‘Instructions for Use’. 2. Patients/caregivers may administer SAPHNELO prefilled syringe/SAPHNELO PEN after proper training in the subcutaneous injection technique and after the healthcare provider determines it is appropriate. 3. Prior to administration, remove SAPHNELO from the refrigerator and allow it to come to room temperature for 60 minutes. 4. Visually inspect SAPHNELO for particulate matter and discoloration prior to administration. SAPHNELO is a clear to opalescent, colorless to slightly yellow, solution. Discard the prefilled syringe or autoinjector if the solution is cloudy, discolored or visible particles are observed. 5. Administer the subcutaneous injection into the thigh or abdomen, avoiding the 5 cm (approximately 2 inches) area around the navel. The upper arm can also be used if a healthcare professional or caregiver administers the injection. 6. Do not inject into areas where the skin is tender, bruised, erythematous or hardened. When injecting in the same region, advise patients to use an injection site at least 3 cm (1‑inch) away from the last injection site. 7. Dispose of any unused medicinal product or waste material in accordance with local requirements.
2.5 Switching Between Intravenous and Subcutaneous Administration When transitioning patients from intravenous administration to subcutaneous administration of SAPHNELO, administer the first subcutaneous injection approximately 2 weeks after the last intravenous infusion. When transitioning patients from subcutaneous administration to intravenous administration of SAPHNELO, administer the first intravenous infusion approximately 3 to 4 weeks after the last subcutaneous injection.
US FDA labelDosage forms
Philippines
- ) concentrate for solution for infusion: 300 mg/2 mL (150 mg/mL
Registered products in the Philippines
1 product registered with the Food and Drug Administration (FDA) Philippines list Anifrolumab as the generic name. Registration status changes; confirm a product's current status on the FDA portal before relying on it.
| Package insert | |||||||
|---|---|---|---|---|---|---|---|
SaphneloAnifrolumab | 300 mg/2 mL (150 mg/ml) Concentrate for Solution for Infusion (IV)2 mL net content Type I clear and colorless glass vial, sealed with tefloncoated chlorobutyl elastomer stopper. and secured by aluminium seal with flip-off plastic button (Box of 1 vial) . | Rx | AstraZeneca Nijmegen B.V.Netherlands | Importer: AstraZeneca Pharmaceuticals (Phils.), Inc. | BR-1466 | Feb 14, 2029 |
Source: FDA Philippines product registration database. "Valid until" is the registration validity date listed by the FDA; a past date may mean a renewal is pending. Package insert links point to files published by the FDA.
United States (label)
Dosage forms and strengths (US label) US FDA label
3 DOSAGE FORMS AND STRENGTHS Intravenous Infusion • Injection: 300 mg/2 mL (150 mg/mL) as a clear to opalescent, colorless to slightly yellow solution in a single-dose vial. Subcutaneous Injection • Injection: 120 mg/0.8 mL as a clear to opalescent, colorless to slightly yellow solution in a single-dose prefilled syringe or single-dose autoinjector (SAPHNELO PEN). Intravenous Infusion: • Injection: 300 mg/2 mL (150 mg/mL) in a single-dose vial. (3) Subcutaneous Injection: • Injection: 120 mg/0.8 mL in a single-dose prefilled syringe or single-dose autoinjector (SAPHNELO PEN). (3)
Warnings/Precautions
- • Serious Infections: Serious and sometimes fatal infections have occurred in patients receiving SAPHNELO. SAPHNELO increases the risk of respiratory infections and herpes zoster. Avoid initiating treatment during an active infection. Consider the individual benefit-risk if using in patients with severe or chronic infections. Consider interrupting therapy with SAPHNELO if patients develop a new infection during treatment. (5.1)
- • Hypersensitivity Reactions Including Anaphylaxis: Serious hypersensitivity reactions including anaphylaxis and angioedema have been reported. (5.2)
- • Malignancy: Consider the individual benefit-risk in patients with known risk factors for malignancy prior to prescribing SAPHNELO. (5.3)
- • Immunizations: Avoid use of live or live-attenuated vaccines in patients receiving SAPHNELO. (5.4)
- • Not Recommended for Use with Other Biologic Therapies. (5.5)
5.1 Serious Infections
5.1 Serious Infections Serious and sometimes fatal infections (including COVID‑19) have occurred in patients receiving immunosuppressive agents, including SAPHNELO. In controlled trials, fatal infections occurred more frequently in patients receiving SAPHNELO [see Adverse Reactions (6.1)]. In controlled trials, SAPHNELO increased the risk of respiratory infections and herpes zoster (disseminated herpes zoster events have been reported) [see Adverse Reactions (6.1)].
Avoid initiating treatment with SAPHNELO in patients with any clinically significant active infection until the infection is resolved or adequately treated. Consider the benefit and risk of administering SAPHNELO in patients with a chronic infection, a history of recurrent infections, or known risk factors for infection.
Instruct patients to seek medical advice if signs or symptoms of a clinically significant infection occur. If a patient develops an infection or is not responding to standard anti-infective therapy while on SAPHNELO, monitor the patient closely and consider interrupting SAPHNELO until the infection resolves.
5.2 Hypersensitivity Reactions Including Anaphylaxis
5.2 Hypersensitivity Reactions Including Anaphylaxis Serious hypersensitivity reactions (including anaphylaxis) have been reported following SAPHNELO administration [see Contraindication (4)]. Events of angioedema have also been reported [see Adverse Reactions (6.1)]. Other hypersensitivity reactions and infusion-related reactions have occurred following administration of SAPHNELO [see Adverse Reactions (6.1)].
Consider pre-medication before infusion of SAPHNELO for patients with a history of these reactions. SAPHNELO should be administered by healthcare providers prepared to manage hypersensitivity reactions, including anaphylaxis, and infusion-related reactions. If a serious infusion-related or hypersensitivity reaction (e.g., anaphylaxis) occurs, immediately interrupt the administration of SAPHNELO and initiate appropriate therapy.
5.3 Malignancy
5.3 Malignancy There is an increased risk of malignancies with the use of immunosuppressants. The impact of SAPHNELO treatment on the potential development of malignancies is not known. Consider the individual benefit-risk in patients with known risk factors for the development or reoccurrence of malignancy prior to prescribing SAPHNELO.
In patients who develop malignancies, consider the benefit-risk of continued treatment with SAPHNELO.
5.4 Immunizations
5.4 Immunizations Update immunizations, according to current immunization guidelines, prior to initiating SAPHNELO therapy. Avoid concurrent use of live or live-attenuated vaccines in patients treated with SAPHNELO.
5.5 Not Recommended for Concomitant Use with Other Biologic Therapies
5.5 Not Recommended for Concomitant Use with Other Biologic Therapies SAPHNELO has not been studied in combination with other biologic therapies, including B-cell-targeted therapies. Therefore, use of SAPHNELO is not recommended for use in combination with biologic therapies.
Drug interactions
Drug interactions (US label) US FDA label
7 DRUG INTERACTIONS No formal drug interaction trials have been conducted.
Adverse reactions
The following clinically significant adverse reactions are also discussed elsewhere in the labeling:
- Serious Infections [see Warnings and Precautions (5.1)]
- Hypersensitivity Reactions Including Anaphylaxis [see Warnings and Precautions (5.2)]
- Malignancy [see Warnings and Precautions (5.3)] Most common adverse drug reactions (incidence ≥5%) are nasopharyngitis, upper respiratory tract infections, bronchitis, infusion related reactions, herpes zoster and cough. (6) To report SUSPECTED ADVERSE REACTIONS, contact AstraZeneca at 1-800-236-9933 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1 Clinical Trials Experience
6.1 Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adverse Reactions with Intravenous Administration The safety of SAPHNELO was assessed in adult patients with moderate to severe SLE who received SAPHNELO 300 mg by intravenous infusion every 4 weeks (N=459) for 52 weeks, compared to placebo (N=466) in controlled clinical trials (Trials 1, 2 and 3) [see Clinical Studies (14.1)].
The population studied had a mean age of 41 years (range: 18 to 69), of which 93% were female, 60% White, 13% Black/African American, and 10% Asian. All patients received standard therapy. In the controlled-clinical trials, adverse reactions, irrespective of causality, were reported in 87% of patients receiving SAPHNELO and 79% of patients receiving placebo.
Adverse reactions that occurred at greater than or equal to 2% incidence are shown in Table 1. Table 1 Adverse Reactions Occurring in ≥2% of Adults with Moderate to Severe SLE Treated with Intravenous SAPHNELO for 52 weeks in Trials 1, 2 and 3 Adverse Reaction SAPHNELO (N=459) % Placebo (N=466) % Upper respiratory tract infection Upper respiratory tract infections (including Upper respiratory tract infections, Nasopharyngitis, Pharyngitis) 34 23 Bronchitis Bronchitis (including Bronchitis, Bronchitis viral, Tracheobronchitis) 11 5.2 Infusion‑related reactions 9.4 7.1 Herpes Zoster 6.1 1.3 Cough 5.0 3.2 Respiratory tract infection Respiratory tract infection (including Respiratory tract infection, Respiratory tract infection viral, Respiratory tract infection bacterial) 3.3 1.5 Hypersensitivity 2.8 0.6 Long-term Safety Patients who completed Trials 2 and 3 (Phase III feeder trials) were eligible to continue on treatment in a randomized, double-blind, placebo-controlled long-term extension (LTE) trial, for an additional 3 years.
The long-term safety of SAPHNELO was assessed in 257 patients who received SAPHNELO 300 mg every 4 weeks and 112 patients who received placebo in both a feeder trial and the LTE. Of these, 177 patients who received SAPHNELO (68.9%) and 52 patients who received placebo (46.4%) completed a total of 4 years on treatment. The overall long-term safety profile of SAPHNELO was consistent with Trials 1, 2 and 3.
Specific Adverse Reactions Infections: In the 52‑week controlled-clinical trials, infections were reported in a greater proportion of patients while on treatment with SAPHNELO compared to placebo (69.7% versus 55.4%, respectively). Herpes Zoster: In the 52‑week controlled-clinical trials, the incidence of herpes zoster in patients while on treatment with SAPHNELO was 6.1% and 1.3% in patients on placebo.
Cases with multidermatomal involvement and disseminated presentation have been reported. Of the 28 SAPHNELO-treated patients with herpes zoster, 2 experienced disseminated disease requiring hospitalization compared to none among placebo-treated patients. Hypersensitivity Reactions Including Anaphylaxis: During the SLE intravenous development program, there was one report of an anaphylactic reaction in a patient who received SAPHNELO 150 mg, and 4 reports of angioedema after 300 mg.
In general, the hypersensitivity reactions were predominantly mild or moderate in intensity and did not lead to discontinuation of SAPHNELO. In the 52‑week controlled‑clinical trials, hypersensitivity reactions occurred in 2.8% of patients while on treatment with SAPHNELO and 0.6% of patients on placebo. Serious hypersensitivity reactions were reported in 0.6% of patients receiving SAPHNELO, including angioedema (n=2).
Infusion‑related Reactions: Infusion‑related reactions were mild to moderate in intensity; the most common symptoms were headache, nausea, vomiting, fatigue, and dizziness. In the 52‑week controlled‑clinical trials, the incidence of infusion‑related reactions while on treatment was 9.4% in patients while on treatment with SAPHNELO and 7.1% in patients on placebo.
Malignancies: In 52‑week controlled-clinical trials, malignancies (excluding non‑melanoma skin cancers) were observed in 0.7% and 0.6% of SAPHNELO-treated and placebo-treated patients. Malignant neoplasm (including non‑melanoma skin cancers) was reported in 1.3% of SAPHNELO-treated patients, compared to 0.6% placebo-treated patients.
The malignancies that were reported in more than one patient treated with SAPHNELO included breast cancer and squamous cell carcinoma. Adverse Reactions with Subcutaneous Administration The safety profile of SAPHNELO administered subcutaneously in adult patients with moderate to severe SLE is derived from Trial 5 [see Clinical Studies (14.2)].
The data reflect SAPHNELO exposure in 185 patients who received SAPHNELO 120 mg by subcutaneous injection once every week, with a median duration of 52 weeks, as compared with comparable exposure to placebo in 182 patients. All patients received standard therapy. The population studied had a mean age of 43 years (range: 18 to 70), of which 92% were female, 74% White, 9% Asian, 8% American Indian or Alaska Native, and 5% Black/African American.
The safety profile observed for SAPHNELO administered subcutaneously was consistent with the known safety profile of SAPHNELO administered intravenously. Serious Infections in the Pool of Intravenous and Subcutaneous Trials In the pool of four placebo-controlled clinical trials in adults with moderate to severe SLE where SAPHNELO was administered either intravenously or subcutaneously (Trials 1, 2, 3, and 5), the incidence of serious infections while on treatment was 5.4% in patients treated with SAPHNELO compared to 4.9% in patients receiving placebo.
Fatal infections occurred while on treatment in 0.5% of SAPHNELO-treated patients and 0% in placebo-treated patients. The most frequent serious infection reported in patients treated with SAPHNELO was pneumonia. During the LTE of Trials 2 and 3, the most common serious infections were COVID‑19 and pneumonia.
6.2 Postmarketing Experience
6.2 Postmarketing Experience The following adverse reaction has been identified during post-approval use of SAPHNELO. Because the reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Arthralgia
Adverse reaction frequency tables (US label) US FDA label
| Adverse Reaction | SAPHNELO (N=459) % | Placebo (N=466) % |
| Upper respiratory tract infectionUpper respiratory tract infections (including Upper respiratory tract infections, Nasopharyngitis, Pharyngitis) | 34 | 23 |
| BronchitisBronchitis (including Bronchitis, Bronchitis viral, Tracheobronchitis) | 11 | 5.2 |
| Infusion‑related reactions | 9.4 | 7.1 |
| Herpes Zoster | 6.1 | 1.3 |
| Cough | 5.0 | 3.2 |
| Respiratory tract infectionRespiratory tract infection (including Respiratory tract infection, Respiratory tract infection viral, Respiratory tract infection bacterial) | 3.3 | 1.5 |
| Hypersensitivity | 2.8 | 0.6 |
Pregnancy considerations
Pregnancy (US label) US FDA label
8.1 Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to SAPHNELO during pregnancy. For more information about the registry or to report a pregnancy while on SAPHNELO, healthcare providers should contact AstraZeneca at 1‑877‑693‑9268 or https://anifrolumabpregnancyandbreastfeedingstudy.us/.
Risk Summary The limited human data with SAPHNELO use in pregnant women are insufficient to inform on drug‑associated risk for major birth defects, miscarriage, or adverse maternal or fetal outcome. Monoclonal IgG antibodies are known to be actively transported across the placenta as pregnancy progresses; therefore, anifrolumab‑fnia exposure to the fetus may be greater during the third trimester of pregnancy.
In an enhanced pre- and post-natal development study with pregnant cynomolgus monkeys that received intravenous administration of anifrolumab-fnia, there was no evidence of embryotoxicity or fetal malformations with exposures up to approximately 28‑times the exposure at the maximum recommended human dose (MRHD) on an Area Under Curve (AUC) basis (see Data). All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk: Pregnant women with SLE are at increased risk of adverse pregnancy outcomes, including worsening of the underlying disease, premature birth, miscarriage, and intrauterine growth restriction.
Maternal lupus nephritis increases the risk of hypertension and preeclampsia/eclampsia. Passage of maternal autoantibodies across the placenta may result in adverse neonatal outcomes, including neonatal lupus and congenital heart block. Data Animal Data: In an enhanced pre- and post-natal development study, pregnant cynomolgus monkeys received anifrolumab-fnia at intravenous doses of 30 or 60 mg/kg once every 2 weeks from confirmation of pregnancy at Gestation Day 20, throughout the gestation period, and continuing until 1‑month post-partum (approximately Lactation Day 28).
There was no evidence of anifrolumab-fnia related maternal toxicity, embryo-fetal toxicity, or post-natal developmental effects. No anifrolumab-fnia related effect on T-cell-dependent antibody response in the infants was noted up to Day 180 after birth. The no observed adverse effect level (NOAEL) for maternal and developmental toxicity was identified as 60 mg/kg (approximately 28‑times the MRHD on an AUC basis).
In the infants, mean serum concentrations of anifrolumab‑fnia on Day 30 after birth increased with dose and were approximately 4.2% to 9.7% of the respective maternal concentrations. The anifrolumab-fnia concentrations in the infant serum were up to approximately 22‑times the concentrations in the maternal milk, suggesting that anifrolumab-fnia had transferred via the placenta.
Mechanism of action
12.1 Mechanism of Action Anifrolumab-fnia is a human IgG1κ monoclonal antibody that binds to subunit 1 of the type I interferon receptor (IFNAR) with high specificity and affinity. This binding inhibits type I IFN signaling, thereby blocking the biologic activity of type I IFNs. Anifrolumab-fnia also induces the internalization of IFNAR1, thereby reducing the levels of cell surface IFNAR1 available for receptor assembly.
Blockade of receptor mediated type I IFN signaling inhibits IFN responsive gene expression as well as downstream inflammatory and immunological processes. Inhibition of type I IFN blocks plasma cell differentiation and normalizes peripheral T-cell subsets. Type I IFNs play a role in the pathogenesis of SLE. Approximately 60-80% of adult patients with active SLE express elevated levels of type I IFN inducible genes.
US FDA labelPharmacodynamics
Pharmacodynamics (US label) US FDA label
12.2 Pharmacodynamics In patients with moderate to severe SLE, following the administration of SAPHNELO, neutralization (≥80%) of a type I IFN gene signature was observed from Week 4 to Week 52 in blood samples of patients with elevated levels of type I IFN inducible genes and returned to baseline levels within 8 to 12 weeks following withdrawal of SAPHNELO at the end of the 52‑week treatment period. However, the clinical relevance of the type I IFN gene signature neutralization is unclear.
In SLE patients with positive anti-dsDNA antibodies at baseline (Trials 2 and 3), treatment with SAPHNELO led to numerical reductions in anti-dsDNA antibodies over time through Week 52. In patients with low complement levels (C3 and C4) at baseline (Trials 2 and 3), increases in complement levels were observed in patients receiving SAPHNELO through Week 52.
Pharmacokinetics
Pharmacokinetics (US label) US FDA label
12.3 Pharmacokinetics The pharmacokinetics (PK) of anifrolumab-fnia was studied in adult patients with SLE following intravenous doses ranging from one-third (100 mg) to 3.3 times (1000 mg) the approved intravenous dosage, 300 mg once every 4 weeks, and subcutaneous 120 mg weekly doses, as well as in healthy volunteers following a single intravenous dose at 300 mg and a single subcutaneous dose of 120 mg. Anifrolumab-fnia exhibits non-linear PK in the dose range of 100 mg to 1000 mg with more than dose-proportional increases in the exposure as measured by AUC, following intravenous administration.
The estimated time to reach steady state is approximately 112 days for both intravenous and subcutaneous administration. Following 300 mg intravenous administrations every 4 weeks, the accumulation ratio for C max was 1.11 and for C trough was 2.37. Following 120 mg subcutaneous administration weekly, the accumulation ratio for C max was 1.85 and C trough was 1.85.
Absorption The bioavailability of anifrolumab-fnia was estimated to be 73% following subcutaneous injection. The estimated maximum serum concentration (C max) of anifrolumab-fnia at steady state was 63.7 μg/mL. Distribution Based on population PK analysis, the estimated volume of distribution at steady state for a typical patient with SLE (68 kg) is 5.16 L.
Elimination From population PK analysis, anifrolumab-fnia exhibited non-linear PK due to IFNAR1-mediated drug clearance. The estimated systemic clearance (CL) for anifrolumab-fnia is 0.146 L/day. Based on population PK analysis of patients who received SAPHNELO for one year, serum concentrations of anifrolumab-fnia were below detection in 95% of patients approximately 16 weeks after the last dose.
Specific Populations There was no clinically meaningful difference in systemic clearance based on age, race, ethnicity, region, gender, IFN status or body weight, that requires dose adjustment. Age: Based on population PK analyses, age (range 18 to 70 years) did not affect anifrolumab-fnia clearance. Limited PK data are available for geriatric patients; 3% (n=33) of the patients included in the PK analysis were 65 years or older [see Use in Specific Populations (8.5)].
Patients with Renal Impairment: No specific clinical trials have been conducted to investigate the effect of renal impairment on anifrolumab-fnia. Based on population PK analyses, anifrolumab-fnia clearance was comparable in SLE patients with mild (60-89 mL/min/1.73 m²) and moderate (30-59 mL/min/1.73 m²) decrease in eGFR values and patients with normal renal function (≥90 mL/min/1.73 m²).
There were no SLE patients with a severe decrease in eGFR or end stage renal disease (<30 mL/min/1.73 m²); anifrolumab-fnia is not cleared renally. Patients with urine protein/creatinine ratio (UPCR) >2 mg/mg were excluded from the clinical trials. Based on population PK analyses, increased UPCR did not significantly affect anifrolumab-fnia clearance.
Patients with Hepatic Impairment: No specific clinical trials have been conducted to investigate the effect of hepatic impairment on anifrolumab-fnia. IgG1 monoclonal antibodies are predominantly eliminated via catabolism and are not expected to undergo hepatic metabolism; changes in hepatic function are not expected to influence anifrolumab-fnia clearance.
Based on population PK analyses, baseline hepatic function biomarkers (ALT and AST ≤2.0 × ULN, and total bilirubin) had no clinically relevant effect on anifrolumab-fnia clearance. Drug Interactions No formal drug-drug interaction trials have been conducted. Based on population PK analysis, concomitant use of oral corticosteroids, anti-malarials, immunosuppressants (azathioprine, methotrexate, mycophenolate mofetil, mycophenolic acid, and mizoribine), NSAIDs, ACE inhibitors, and HMG-CoA reductase inhibitors did not significantly affect the PK of anifrolumab-fnia.
Formulary and pricing (Philippines)
Check availability
Prices and stock vary by branch; renalcarematters.com does not sell medicines or receive payment from pharmacies.
Related guides
Guides on renalcarematters.com for this medicine, for patients and clinicians.
References
- U.S. Food and Drug Administration. SAPHNELO · AstraZeneca Pharmaceuticals LP [US FDA-approved label, version 16, September 25, 2026]. Via DailyMed/openFDA. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=d6203302-2128-41a7-b0b4-0e6c0704d4dc
- Food and Drug Administration Philippines. Verification portal (product registrations). https://verification.fda.gov.ph
This page shows official label and registry text only; no renalcarematters.com clinical summary has been approved for it yet.
Last updated: .