Use: Labeled indications
- The management of adults with signs and symptoms of primary or secondary gout (acute attacks, tophi, joint destruction, uric acid lithiasis, and/or nephropathy)
- The management of adult and pediatric patients with leukemia, lymphoma and solid tumor malignancies who are receiving cancer therapy which causes elevations of serum and urinary uric acid levels
- The management of adult patients with recurrent calcium oxalate calculi whose daily uric acid excretion exceeds 800 mg/day in male patients and 750 mg/day in female patients, despite lifestyle changes (such as reduction…
Full indications and usage US FDA label
1 INDICATIONS & USAGE Allopurinol tablet is indicated for: The management of adults with signs and symptoms of primary or secondary gout (acute attacks, tophi, joint destruction, uric acid lithiasis, and/or nephropathy) The management of adult and pediatric patients with leukemia, lymphoma and solid tumor malignancies who are receiving cancer therapy which causes elevations of serum and urinary uric acid levels The management of adult patients with recurrent calcium oxalate calculi whose daily uric acid excretion exceeds 800 mg/day in male patients and 750 mg/day in female patients, despite lifestyle changes (such as reduction of dietary sodium, non-dairy animal protein, oxylate rich foods, refined sugars and increases in oral fluids and fruits and vegetables) Limitations of Use Allopurinol tablet is not recommended for the treatment of asymptomatic hyperuricemia. Allopurinol tablet is a xanthine oxidase inhibitor indicated for the management of: Adult patients with signs and symptoms of primary or secondary gout (acute attacks, tophi, joint destruction, uric acid lithiasis, and/or nephropathy) (1) Adult and pediatric patients with leukemia, lymphoma and solid tumor malignancies who are receiving cancer therapy which causes elevations of serum and urinary uric acid levels (1) Adult patients with recurrent calcium oxalate calculi whose daily uric acid excretion exceeds 800 mg/day in male patients and 750 mg/day in female patients, despite lifestyle changes (1) Limitations of Use Allopurinol tablet is not recommended for the treatment of asymptomatic hyperuricemia.
(1)
Contraindications
- Hypersensitivity to allopurinol or any ingredient
Contraindications (US label) US FDA label
4 CONTRAINDICATIONS Allopurinol tablet is contraindicated in patients with a history of hypersensitivity reaction to allopurinol or to any of the ingredients of allopurinol tablets. Known hypersensitivity to allopurinol or to any of the ingredients of allopurinol tablets.
Dosing: Adult
- Gout: Start 100 mg daily; increase by 100 mg weekly to serum urate 6 mg/dL or less; maximum 800 mg daily
- Hyperuricemia from cancer therapy: 300 to 800 mg daily
- Recurrent calcium oxalate stones: 200 to 300 mg daily (normal kidney function)
- Gout: Prior to initiating treatment assess serum uric acid level, complete blood count, chemistry panel, liver and kidney function tests. Prophylactic treatment for gout flares is recommended. (2.1, 2.2)
- Patients with normal kidney function: Initial dosage is 100 mg orally daily. Increase by 100 mg weekly increments until serum uric acid of 6 mg/dl or less is reached (maximum 800 mg daily). (2.3)
- Patients with impaired kidney function: The initial dosage is 50 mg orally daily. Follow recommendations for titration in patients with renal impairment until target serum uric acid level is reached. (2.6)
- See complete information in the Full Prescribing Information (FPI). Hyperuricemia Associated with Cancer Therapy: The recommended dosage is: Adults: 300 mg to 800 mg orally daily. Pediatric patients: 100 mg/m 2 orally every 8 hours to 12 hours (10 mg/kg/day, maximum 800 mg/day) See complete information in the FPI. (2.4, 2.6)
- Recurrent Calcium Oxalate Calculi: The recommended initial dosage in patients with normal kidney function is 200 mg to 300 mg orally daily. (2.5)
- Dosage in Patients with Renal Impairment: See FPI for dosage modifications in patients with renal impairment. (2.6)
2.1 Recommended Testing Prior to Treatment Initiation
2.1 Recommended Testing Prior to Treatment Initiation Prior to initiating treatment with allopurinol tablets in patients with gout, assess the following baseline tests: serum uric acid level, complete blood count, chemistry panel, liver function tests (serum alanine aminotransferase [ALT], aspartate aminotransferase [AST], alkaline phosphatase, and total bilirubin), kidney function tests (serum creatinine and eGFR).
2.2 Recommended Prophylaxis for Gout Flares
2.2 Recommended Prophylaxis for Gout Flares Gout flares may occur after initiation of allopurinol tablets due to changing serum uric acid levels resulting in mobilization of urate from tissue deposits. Flare prophylaxis with colchicine or an anti-inflammatory agent according to practice guidelines is recommended upon initiation of allopurinol tablets.
While adjusting the dosage of allopurinol tablets in patients who are being treated with colchicine and/or anti-inflammatory agents, continue flare prophylaxis drugs until serum uric acid has been normalized and the patient has been free of gout flares for several months. If a gout flare occurs during allopurinol treatment, allopurinol tablets need not be discontinued.
Manage the gout flare concurrently, as appropriate for the individual patient [see Warnings and Precautions (5.2)].
2.3 Recommended Dosage for Gout
2.3 Recommended Dosage for Gout The initial recommended dosage for the management of gout is 100 mg orally daily, with weekly increments of 100 mg, until a serum uric acid level of 6 mg/dL or less is reached. Initiating treatment with lower dosages of allopurinol tablets and titrating slowly, decreases the risk of gout flares and drug induced serious adverse reactions.
In patients with renal impairment the initial dosage is 50 mg orally daily with lower dose increases until serum uric acid level of 6 mg/dL or less is reached. For complete dosage recommendations for patients with renal impairment see Table 1 [see Dosage and Administration (2.6)]. The minimal effective dosage is 100 mg to 200 mg daily and the maximal recommended dosage is 800 mg daily.
The appropriate dosage may be administered in divided doses or as a single equivalent dose with the 300 mg tablet. Doses in excess of 300 mg should be administered in divided doses. Monitor patient's kidney function during the early stages of administration of allopurinol tablets and decrease the dosage or withdraw the drug if persistent abnormalities in kidney function occur [see Dosage and Administration (2.6), Warnings and Precautions (5.3), Use in Specific Populations (8.6)].
The dosage of allopurinol tablets to achieve control of gout varies with the severity of the disease. In general, gout control is achieved with 200 mg to 300 mg daily in patients with mild gout, and with 400 mg to 600 mg daily in patients with moderate to severe tophaceous gout. Gout attacks usually become shorter and less severe after several months of therapy.
If a dose of allopurinol tablets is missed, there is no need to double the dose at the next scheduled time. Allopurinol tablets is generally better tolerated if taken following meals. A fluid intake sufficient to yield a daily urinary output of at least 2 liters and the maintenance of a neutral or preferably, slightly alkaline urine are desirable.
Inform patients of the possibility of gout flares [see Warnings and Precautions (5.2)]. Instruct them to remain on allopurinol tablets if this occurs and to increase fluid intake during therapy to prevent kidney stones. Concurrent Use of Uricosuric Agents Some patients, may benefit using uricosuric agents concurrently, to reduce serum uric acid to target levels.
When transferring a patient from a uricosuric agent to allopurinol tablets, reduce the dose of the uricosuric agent over a period of several weeks and increase the dose of allopurinol tablets gradually to the required dose needed to maintain target serum uric acid level.
2.4 Recommended Dosage for Hyperuricemia Associated with Cancer Therapy
2.4 Recommended Dosage for Hyperuricemia Associated with Cancer Therapy Initiate therapy with allopurinol tablets 24 hours to 48 hours before the start of chemotherapy known to cause tumor cell lysis. Administer fluids sufficient to yield a daily urinary output of at least 2 liters in adults (at least 100 mL/m 2 /hour in pediatric patients) with a neutral or, preferably, slightly alkaline urine.
The recommended dosage of allopurinol tablets is: Adult patients – 300 mg to 800 mg orally daily Pediatric patients - 100 mg/m 2 orally every 8 hours to 12 hours (10 mg/kg/day, maximum 800 mg/day). In patients with body surface area < 0.5 m², consider using an alternative allopurinol formulation. The dosage of allopurinol tablets to maintain normal or near-normal serum uric acid varies with the severity of the disease.
Monitor serum uric acid levels at least daily and administer allopurinol tablets at a dose and frequency to maintain the serum uric acid within the normal range. Discontinue allopurinol tablets when the risk of tumor lysis has abated (2 days to 3 days from start of chemotherapy). For complete dosage recommendations for patients with renal impairment, see Table 2 [see Dosage and Administration (2.6)].
2.5 Recommended Dosage for Management of Recurrent Calcium Oxalate Calculi in Hyperuricosuric…
2.5 Recommended Dosage for Management of Recurrent Calcium Oxalate Calculi in Hyperuricosuric Patients The recommended dosage for the management of recurrent calcium oxalate stones in hyperuricosuric patients is 200 mg to 300 mg orally daily in divided doses or as the single equivalent. This dose may be adjusted depending upon the resultant control of the hyperuricosuria based upon subsequent 24-hour urinary urate determinations.
2.6 Recommended Dosage in Patients with Renal Impairment
2.6 Recommended Dosage in Patients with Renal Impairment The recommended initial dosages of allopurinol tablets in adult patients with renal impairment are shown in Tables 1 and 2 [see Use in Specific Populations (8.6)]. Patients with Gout The recommended initial dosages in adult patients with gout with impaired kidney function are shown in Table 1 [see Use in Specific Populations (8.6)].
Initiate treatment with a lower dose of allopurinol tablets and increase the dose gradually in 50 mg/day increments every 2 weeks to 4 weeks in patients with renal impairment to decrease the risk of drug induced serious adverse reactions. Use the lowest dose possible to achieve the desired effect on serum and/or urine uric acid.
Monitor kidney function in gout patients with chronic kidney disease closely when initiating treatment with allopurinol tablets and decrease or withdraw the drug if increased abnormalities in kidney function appear and persist. Table 1. Recommended Initial Dosage in Adult Patients with Gout eGFR Initial Dosage > 60 mL/minute No dosage modification > 30 to 60 mL/minute 50 mg daily > 15 to 30 mL/minute 50 mg every other day 5 to 15 mL/minute 50 mg twice weekly < 5 mL/minute 50 mg once weekly The maximum dosage that should be used in patients with various levels of renal impairment is not defined at different eGFR levels.
Patients with Recurrent Calcium Oxalate Calculi Data are insufficient to provide dosage recommendations for the treatment of recurrent calcium oxalate calculi in patients with renal impairment. Allopurinol and its metabolites are excreted by the kidney, and accumulation of the drug can occur in renal failure [see Warnings and Precautions (5.3) and Use in Specific Populations (8.6)].
Hyperuricemia Associated with Cancer Therapy The recommended dosage of allopurinol tablets for the management of hyperuricemia associated with cancer therapy in adult patients with renal impairment is shown in Table 2 [see Use in Specific Populations (8.6)]. Table 2. Recommended Dosage of Allopurinol Tablets in Adult Patients for Management of Hyperuricemia Associated with Cancer Therapy with Renal Impairment eGFR Recommended Dosage > 20 mL/min to 60 mL/min No dosage modification 10 mL/min to 20 mL/min 200 mg/day < 10 mL/min 100 mg/day On dialysis 50 mg every 12 hours, or 100 mg every 24 hours Treatment with allopurinol tablets has not been studied in pediatric patients with severe renal impairment (eGFR < 20 mL/min) or on dialysis.
There is insufficient information to establish dosing for allopurinol tablets in pediatric patients with renal impairment. In these patients, consider the risks and potential benefits before initiating treatment with allopurinol tablets [see Warnings and Precautions (5.3) and Use in Specific Populations (8.6)].
Dosing: Altered kidney function
Allopurinol and its active metabolite oxipurinol are cleared by the kidneys, so exposure rises steeply as kidney function falls. The US label gives starting doses by estimated glomerular filtration rate (eGFR) for gout, then slow titration by 50 mg/day every 2 to 4 weeks.
Kidney function measure: Label tables use eGFR expressed in mL/min (both gout and cancer-therapy tables); the label does not state indexing to 1.73 m2.
Show full dosing details
- eGFR ≥60
- Gout: no starting-dose modification (label: eGFR >60 mL/min). Titrate to serum urate target; use the lowest effective dose.
- eGFR 30–59
- Gout: start 50 mg daily (label: eGFR >30 to 60 mL/min); increase by 50 mg/day every 2 to 4 weeks. Cancer-therapy hyperuricemia: no modification at eGFR >20 to 60 mL/min.
- eGFR 15–29
- Gout: start 50 mg every other day (label: eGFR >15 to 30 mL/min); titrate slowly. Cancer-therapy hyperuricemia: no modification at eGFR >20; 200 mg/day at eGFR 10 to 20 mL/min (label Table 2).
- eGFR <15 (not on dialysis)
- Gout: start 50 mg twice weekly (eGFR 5 to 15 mL/min) or 50 mg once weekly (eGFR <5 mL/min). Cancer-therapy hyperuricemia: 100 mg/day at eGFR <10 mL/min.
- Hemodialysis (intermittent)
- Gout: the label gives no dialysis dose; start at the lowest band dose and titrate to the urate target with specialist input. Allopurinol and oxipurinol are removed by hemodialysis (label, Overdosage); give doses after the session on dialysis days. Cancer-therapy hyperuricemia on dialysis: 50 mg every 12 hours or 100 mg every 24 hours (label).
- Peritoneal dialysis
- No PD-specific dose in the label; the label's 'on dialysis' row (cancer-therapy hyperuricemia) does not name the modality.
- CRRT
- No data in label. Insufficient data: use with specialist input.
- Dialyzable? Yes: allopurinol and oxipurinol are dialyzable (label, Overdosage); benefit of dialysis in overdose is unknown.
- Monitoring Consider HLA-B*58:01 testing before starting in patients of Asian ancestry (the label names Han Chinese, Korean and Thai; label 5.1); avoid in carriers unless benefit clearly outweighs risk. The kidney-band doses are starting doses: increase by 50 mg/day every 2 to 4 weeks to serum urate below 6 mg/dL; the label does not define a maximum by eGFR, and ACR 2020 supports titration above traditional CrCl-based doses. Monitor kidney function closely when starting in chronic kidney disease (CKD); reduce or stop if kidney abnormalities appear and persist. Watch for serious skin reactions.
Children (kidney dosing)
Show full dosing details
- eGFR ≥60
- Normal kidney function: usual pediatric dosing (cancer-therapy hyperuricemia; label).
- eGFR 30–59
- Insufficient information in the label to set pediatric doses in kidney impairment; weigh risks and benefits (label). Specialist input.
- eGFR 15–29
- Insufficient information in the label to set pediatric doses in kidney impairment; weigh risks and benefits (label). Specialist input.
- eGFR <15 (not on dialysis)
- Insufficient information in the label to set pediatric doses in kidney impairment; weigh risks and benefits (label). Specialist input.
- Hemodialysis (intermittent)
- Not studied in children on dialysis (label). Specialist input.
- Peritoneal dialysis
- Not studied in children on dialysis (label). Specialist input.
- CRRT
- No data. Specialist input.
Pediatric eGFR: bedside Schwartz equation, 0.413 × height (cm) / serum creatinine (mg/dL). Weight-based doses should not exceed the adult maximum.
renalcarematters.com guidance, reviewed by William Gregory M. Rivero, MD, FPCP, DPSN on November 17, 2026. Sources are listed under References. Use with the product's package insert and the patient's current kidney function.
US label text: Renal impairment US FDA label
2.6 Recommended Dosage in Patients with Renal Impairment The recommended initial dosages of allopurinol tablets in adult patients with renal impairment are shown in Tables 1 and 2 [see Use in Specific Populations (8.6)]. Patients with Gout The recommended initial dosages in adult patients with gout with impaired kidney function are shown in Table 1 [see Use in Specific Populations (8.6)].
Initiate treatment with a lower dose of allopurinol tablets and increase the dose gradually in 50 mg/day increments every 2 weeks to 4 weeks in patients with renal impairment to decrease the risk of drug induced serious adverse reactions. Use the lowest dose possible to achieve the desired effect on serum and/or urine uric acid.
Monitor kidney function in gout patients with chronic kidney disease closely when initiating treatment with allopurinol tablets and decrease or withdraw the drug if increased abnormalities in kidney function appear and persist. Table 1. Recommended Initial Dosage in Adult Patients with Gout eGFR Initial Dosage > 60 mL/minute No dosage modification > 30 to 60 mL/minute 50 mg daily > 15 to 30 mL/minute 50 mg every other day 5 to 15 mL/minute 50 mg twice weekly < 5 mL/minute 50 mg once weekly The maximum dosage that should be used in patients with various levels of renal impairment is not defined at different eGFR levels.
Patients with Recurrent Calcium Oxalate Calculi Data are insufficient to provide dosage recommendations for the treatment of recurrent calcium oxalate calculi in patients with renal impairment. Allopurinol and its metabolites are excreted by the kidney, and accumulation of the drug can occur in renal failure [see Warnings and Precautions (5.3) and Use in Specific Populations (8.6)].
Hyperuricemia Associated with Cancer Therapy The recommended dosage of allopurinol tablets for the management of hyperuricemia associated with cancer therapy in adult patients with renal impairment is shown in Table 2 [see Use in Specific Populations (8.6)]. Table 2. Recommended Dosage of Allopurinol Tablets in Adult Patients for Management of Hyperuricemia Associated with Cancer Therapy with Renal Impairment eGFR Recommended Dosage > 20 mL/min to 60 mL/min No dosage modification 10 mL/min to 20 mL/min 200 mg/day < 10 mL/min 100 mg/day On dialysis 50 mg every 12 hours, or 100 mg every 24 hours Treatment with allopurinol tablets has not been studied in pediatric patients with severe renal impairment (eGFR < 20 mL/min) or on dialysis.
There is insufficient information to establish dosing for allopurinol tablets in pediatric patients with renal impairment. In these patients, consider the risks and potential benefits before initiating treatment with allopurinol tablets [see Warnings and Precautions (5.3) and Use in Specific Populations (8.6)].
8.6 Renal Impairment Allopurinol and its primary active metabolite, oxipurinol, are eliminated by the kidneys; therefore, changes in renal function have a profound effect on exposure. In patients with decreased renal function or who have concurrent illnesses which can affect renal function, perform periodic laboratory parameters of renal function and reassess the patient's dosage of allopurinol [see Dosage and Administration (2.6), Warnings and Precautions (5.3)].
Dosing: Pediatric
- Approved ages
- Cancer-therapy hyperuricemia: established in pediatric patients (about 200 studied). Not established for gout, recurrent calcium oxalate calculi, or inborn errors of purine metabolism.
- Usual dose
- Cancer-therapy hyperuricemia: 100 mg/m2 orally every 8 to 12 hours (10 mg/kg/day), maximum 800 mg/day; keep urine output at least 100 mL/m2/hour.
- Maximum dose
- 800 mg/day (label).
- Neonates
- Neonates: specialist input (label gives no neonatal dose).
The label states treatment has not been studied in pediatric patients with severe renal impairment (eGFR <20 mL/min) or on dialysis.
Kidney dosing in children: see Dosing: Altered kidney function.
renalcarematters.com, reviewedPediatric use (US label) US FDA label
8.4 Pediatric Use Hyperuricemia Associated with Cancer Therapy The safety and effectiveness of allopurinol for the management of pediatric patients with leukemia, lymphoma and solid tumor malignancies who are receiving cancer therapy which causes elevations of serum and urinary uric acid levels have been established in approximately 200 pediatric patients. The efficacy and safety profile observed in this patient population were similar to that observed in adults.
Primary or Secondary Gout The safety and effectiveness of allopurinol have not been established for the treatment of signs and symptoms of primary or secondary gout in pediatric patients. Recurrent Calcium Oxalate Calculi The safety and effectiveness of allopurinol have not been established for the management of pediatric patients with recurrent calcium oxalate calculi.
Inborn Errors of Metabolism The safety and effectiveness of allopurinol have not been established in pediatric patients with rare inborn errors of purine metabolism.
Dosage forms
Philippines
- Tablet: 100 mg, 300 mg
- Capsule: 100 mg, 300 mg
- Film-coated tablet: 100 mg, 300 mg
Registered products in the Philippines
65 products registered with the Food and Drug Administration (FDA) Philippines list Allopurinol as the generic name (including products registered under a variant spelling). Registration status changes; confirm a product's current status on the FDA portal before relying on it.
Also registered under: Allopurino (1 product). Products registered under these spellings are included in the table and marked.
All registered products65
| Package insert | |||||||
|---|---|---|---|---|---|---|---|
AllonavAllopurinol | 300 mg TabletAluminum Foil Strip x 10's (Box of 100's) | Rx | Lloyd Laboratories, Inc.Philippines | JN Carlo Pharmaceuticals DistributorTrader: Westfield Pharmaceuticals, Inc. | DRP-8769-01 | Oct 19, 2030 | |
AllujenAllopurinol | 100 mg TabletAlu/PVC Blister Pack x 20's Box of 100's | Rx | New Myrex Laboratories, Inc.Philippines | TGP Pharma Inc. | DRP-1866-01 | Jan 27, 2030 | |
AllujenAllopurinol | 300mg TabletAlu/Clear PVC Blister Pack x 10's (Box of 100's) | Rx | New Myrex Laboratories, Inc.Philippines | TGP Pharma Inc. | DRP-2173-01 | Apr 5, 2031 | |
AllunolAllopurinol | 300 mg TabletAluminum Foil Strip x 10's (Box of 100's) | Rx | Lloyd Laboratories, Inc.Philippines | Trader: Westfield Pharmaceuticals, Inc. | DRP-8769 | Oct 19, 2030 | |
AlluprexAllopurinol | 100 mg TabletAlu/PVC Blister Pack x 20's (Box of 100's) | Rx | New Myrex Laboratories, Inc.Philippines | — | DRP-1866 | Jan 27, 2030 | |
AlluprexAllopurinol | 300 mg TabletAlu/Clear PVC Blister Pack x 10's (Box of 100's) | Rx | New Myrex Laboratories, Inc.Philippines | — | DRP-2173 | May 14, 2030 | |
AlluraseAllopurinol | 100 mg TabletFoil Strip x 10's (Box of 100's) | Rx | Drugmaker's Laboratories, Inc.Philippines | Trader: Terramedic, Inc. | DR-XY700 | Jun 26, 2031 | |
AlluraseAllopurinol | 300 mg TabletFoil Strip x 10's (Box of 50's) | Rx | Drugmaker's Laboratories, Inc.Philippines | Trader: Terramedic, Inc. | DR-XY1380 | Mar 15, 2029 | |
AloprexAllopurinol | 100 mg Film-Coated TabletAlu/Pvc Blister Pack X 10's (Box of 100's) | Rx | Huazhong Pharmaceuticals Co., Ltd.China | PhilRx Pharma Inc. | DRP-18443 | Jul 13, 2031 | |
AloprexAllopurinol | 300 mg Film-Coated TabletAlu/Pvc Blister Pack X 10'S (Box of 100's) | Rx | Huazhong Pharmaceuticals Co., Ltd.China | PhilRx Pharma Inc. | DRP-18442 | Jul 13, 2031 | |
AlorexAllopurinol | 100 mg TabletAlu/Clear PVC Blister pack x 20's (Box of 100's) | Rx | Drugmaker's Laboratories, Inc.Philippines | Phil Pharmawealth, Inc. | DRP-5680-02 | Dec 28, 2028 | |
AlorexAllopurinol | 300 mg TabletAluminum Foil Strip x 10's (Box of 100's) | Rx | Drugmaker's Laboratories, Inc.Philippines | Phil Pharmawealth, Inc. | DRP-8402-01 | Sep 20, 2028 | |
AlpugenAllopurinol | 100 mg TabletAlu-PVC Blister Pack x 10's (Box of 30's, 50's and 100's) | Rx | Azarias Pharmaceutical Laboratories IncPhilippines | Eba Generisch Trading Inc. | DRP-16097-02 | Oct 30, 2029 | |
AlpuraseAllopurinol | 300 mg TabletStrip Foil x 10's | Rx | Lloyd Laboratories, Inc.Philippines | Nutramedica Inc.Trader: Foramen Products Corporation | DRP-494 | Nov 7, 2031 | |
AlpurinAllopurinol | 300 mg TabletFoil Strip x 10's (Box of 100's) | Rx | Lloyd Laboratories, Inc.Philippines | 999 Seth Pharmaceutical, Inc.Trader: Euro-Health Care Exponents, Inc. | DR-XY22259 | Nov 21, 2027 | |
Alrinol 100Allopurinol | 100 mg TabletAlu/Alu Strip x 10's (Box of 10's) | Rx | Acme Formulation Pvt. LtdIndia | SRS Life Sciences Inc. | DRP-16254 | Jan 13, 2030 | |
300 mg TabletAlu/-Alu Strip x 10's (Box of 10's) | Rx | Acme Formulation Pvt. Ltd.India | SRS Life Sciences Inc. | DRP-16253 | Jan 13, 2030 | ||
AlunlanAllopurinol | 300 mg TabletBlister pack of 10's Box of 100's | Rx | Y.S.P. Industries (M) Sdn. Bhd.Malaysia | Yung Shin (Philippines), Inc. | DR-XY27540 | Jun 4, 2027 | |
AluprinAllopurinol | 100 mg TabletAlu/Clear PVC Blister Pack x 20's (Box of 100's) | Rx | Drugmaker's Laboratories, Inc.Philippines | — | DRP-5680 | Dec 28, 2028 | |
AluprinAllopurinol | 300 mg TabletAluminum Foil Strip x 10's (Box of 100's) | Rx | Drugmaker’s Laboratories Inc.Philippines | — | DRP-8402 | Sep 20, 2028 | |
AprunolAllopurinol | 100 mg TabletAlu-PVC Blister Pack x 10's (Box of 30's, 50's and 100's) | Rx | Azarias Pharmaceutical Laboratories Inc.,Philippines | — | DRP-16097 | Oct 30, 2029 | |
Aprunol 300Allopurinol | 300mg TabletAlu/PVC Clear Blister Pack x 10’s (Box of 30’s, 50’s & 100’s) | Rx | Azarias Pharmaceutical Laboratories Inc.Philippines | — | DRP-18524 | Aug 3, 2031 | |
AurinolAllopurinol | 100 mg TabletAlu/Clear PVC Blister Pack x 10's (Box of 100's) | Rx | Pharmasant Laboratories Co., Ltd.Thailand | Importer: Endure Medical, Inc. | DR-XY41243 | Sep 13, 2027 | |
DocinolAllopurinol | Tablet ; 100mgAlu/clear PVC Blister Pack x 10's Box of 10's; Alu/clear PVC Blister Pack x 10's Box of 30's; Alu/clear PVC Blister Pack x 10's Box of 100's | Rx | PHIL. UNITED PHARMA CORPORATIONPhilippines | Trader: DOCTEUR'S CHOICE CORPORATION | DRP-9460 | Jan 21, 2031 | |
DocinolAllopurinol | Tablet ; 300 mgAlu/clear PVC Blister Pack x 10's Box of 10's; Alu/clear PVC Blister Pack x 10's Box of 30's; Alu/clear PVC Blister Pack x 10's Box of 100's | Rx | PHIL. UNITED PHARMA CORPORATIONPhilippines | Trader: DOCTEUR'S CHOICE CORPORATION | DRP-9461 | Jan 21, 2031 | |
ElavilAllopurinol | 100mg TabletAlu/PVC Blister Pack x Pack 20's (Box of 100's) | Rx | Am-Europharma CorporationPhilippines | Rilem Pharma Corp. | DRP-2614 | Jun 9, 2030 | |
ELAVILAllopurinol | 300 mg TabletAlu/Pvc Blister Pack X 10's (Box of 100's) | Rx | Am-Europharma CorporationPhilippines | Rilem Pharma Corp | DRP-2928 | Jun 9, 2031 | |
GogoutAllopurinol | 100mg TabletAlu/Clear PVC Blister Pack x 10's (Box of 10's,30's,100's) | Rx | Phil. United Pharma CorporationPhilippines | Trader: Golden Dale Pharma Corp. | DRP-9454 | Jan 21, 2031 | |
GogoutAllopurinol | 300mg TabletAlu/Clear PVC Blister Pack x 10's (Box of 10's,30's and 100's) | Rx | Phil. United Pharma CorporationPhilippines | Trader: Golden Dale Pharma Corp. | DRP-9455 | Jan 21, 2031 | |
GoutrolAllopurinol | 100 mg tabletAlu/PVC Blister Pack x 10's (Box of 100's) | Rx | Scheele Laboratories Phils., Inc.Philippines | — | DRP-10217 | Feb 5, 2029 | |
GoutrolAllopurinol | 300 mg tabletAlu/PVC Blister Pack x 10's (Box of 100's) | Rx | Scheele Laboratories Phils., Inc.Philippines | — | DRP-5299 | Feb 10, 2028 | |
LlanolAllopurinol | 100 mg TabletAluminum foil strip x 4's (Box of 100's) | Rx | Amherst Laboratories, Inc.Philippines | Trader: UNILAB, Inc. | DR-7571 | May 30, 2027 | |
LlanolAllopurinol | 300 mg TabletAluminum Foil Strip x 4's (Box of 100's) | Rx | Amherst Laboratories, Inc.Philippines | Trader: UNILAB, Inc. | DR-X8671 | May 30, 2037 | |
LogoutAllopurinol | 100 mg TabletAlu Strip Foil x 10's (Box of 100's) | Rx | Inga Laboratories P. Ltd.India | Ambica International Corporation | DRP-9406 | Jun 30, 2030 | |
Loric-100Allopurinol | 100 mg TabletAlu/PVC Blister Pack x 25's (Box of 100's) | Rx | Oman Pharmaceutical Products Co., LLCOman | MG Prime Pharmaceutical, Inc.Importer: Atlantic Pharmaceuticals, Inc. | DRP-7463 | Aug 16, 2030 | |
Loric-300Allopurinol | 300 mg TabletAlu-Clear PVC Blister Pack x 14's (Box of 28's) | Rx | Oman Pharmaceutical Products Co., LLCOman | MG Prime Pharmaceutical, Inc.Importer: Atlatinc Pharmaceuticals, Inc. | DRP-7460 | Aug 16, 2030 | |
LoricidAllopurinol | 300 mg TabletFoil Strip x 10's (Box of 100's) | Rx | DRUGMAKER'S LABORATORIES, INC.Philippines | Trader: LITTMAN DRUG CORPORATION | DR-XY17277 | Jun 19, 2027 | |
LovazAllopurinol | 300 mg TabletBlister Pack x 10's (Box of 100's) | Rx | Lloyd Laboratories, Inc.Philippines | Ezmeds Pharma, Inc.Trader: Gamot Philippines, Inc. | DR-XY27689 | Jul 16, 2027 | |
NoneAllopurinol | 100 mg TabletAlu/Clear PVC Blister Pack x 10's (Box of 100's) | Rx | Harman Finochem LimitedIndia | Ritemed Phils., Inc. | DRP-15560 | Aug 15, 2029 | |
NoneAllopurinol | 100 mg TabletAlu/Clear PVC Blister pack x 20's Box of 100's | Rx | Drugmaker's Laboratories, Inc.Philippines | TGP Pharma Inc. | DRP-5680-01 | Dec 28, 2028 | |
NoneAllopurinol | 100 mg TabletAlu/Clear PVC Blister Pack x 10's (Box of 10's, 30's and 100's) | Rx | Phil. United Pharma CorporationPhilippines | — | DRP-9456 | Jan 21, 2031 | |
NoneAllopurinol | 300 mg TabletAlu/PVC Blister Pack x 10's (Box of 100's) | Rx | Scheele Laboratories Phils., Inc.Philippines | RiteMED Phils., Inc. | DRP-5299-01 | Feb 10, 2028 | |
NoneAllopurinol | 300 mg TabletAlu/clear PVC Blister Pack x 10's (Box of 10's, 30's and 100's) | Rx | Phil. United Pharma Corp.Philippines | — | DRP-9457 | Jan 21, 2031 | |
Opunol-100Allopurinol | 100 mg TabletAlu/Alu Blister Pack x 10’s (Box of 30’s) | Rx | Sydler Remedies Pvt. Ltd.India | Ambica International Corporation | DRP-6641 | Apr 12, 2038 | |
Opunol-300Allopurinol | 300 mg TabletAlu/Alu Blister Pack x 10’s (Box of 30’s) | Rx | Sydler Remedies Pvt. Ltd.India | Ambica International Corporation | DRP-6640 | Apr 12, 2038 | |
PrinolAllopurinol | 100 mg CapsuleAlu/PVC/PVDC Blister Pack x 10's (Box of 100's) | Rx | Hizon Laboratories, Inc.Philippines | Willore Pharma Corporation | DR-XY35650 | Apr 1, 2029 | |
Psylloprim 100Allopurinol | 100 mg TabletAlu/clear PVC Blister Pack x 10's (Box of 10's, 30's and 100's)) | Rx | Phil. United Pharma Corp.Philippines | Trader: ATC Healthcare International Corp. | DRP-9458 | Jan 21, 2031 | |
Psylloprim 300Allopurinol | 300 mg TabletAlu/Clear PVC Blister Pack x 10's (Box of 10's, 30's and 100's) | Rx | Phil. United Pharma CorporationPhilippines | Trader: ATC Healthcare International Corp. | DRP-9459 | Jan 21, 2031 | |
PurinaseAllopurinol | 100 mg TabletFoil Strip x 4's (Box of 100's) | Rx | AMHERST LABORATORIES, INC.Philippines | Trader: UNILAB, Inc. | DRP-9873 | Oct 1, 2027 | |
PurinaseAllopurinol | 300 mg TabletFoil Strip x 4's (Box of 50's) | Rx | Amherst Laboratories, Inc.Philippines | Trader: UNILAB, Inc. | DRP-9904 | Oct 1, 2030 | |
PurispecAllopurinol | 100 mg TabletFoil Strip x 10's (Box of 100's) | Rx | Lloyd Laboratories, Inc.Philippines | Trader: Pharmaspec N.A., Inc. | DR-XY22527 | Feb 4, 2027 | |
PurispecAllopurinol | 300 mg TabletAluminum Foil Strip x 10's (Box of 100's) | Rx | Lloyd Laboratories, Inc.Philippines | Trader: Pharmaspec N.A., Inc. | DR-XY19811-B | Aug 1, 2027 | |
RapurinolAllopurinol | 100 mg TabletAlu-PVC Blister Pack x 10's (Box of 30's, 50's and 100's) | Rx | Azarias Pharmaceutical Laboratories Inc.Philippines | St. Raphael Archangel Pharmaceutical Product Distribution | DRP-16097-01 | Oct 30, 2030 | |
SaphrinolAllopurinol | 100 mg TabletAlu foil strip x 10's (Box of 100's) | Rx | Sapphire Lifesciences Pvt. Ltd.India | Nelpa Lifesciences, Inc. | DRP-16652 | Jun 3, 2030 | |
TrinolAllopurinol | 100 mg TabletAlu-PVC Blister Pack x 10's (Box of 30's, 50's and 100's) | Rx | Azarias Pharmaceutical Laboratories Inc.Philippines | Triple 888 Medical And Pharma Inc | DRP-16097-03 | Oct 30, 2029 | |
UnbrandedAllopurinol | 300 mg CapsuleBlister Pack x 10’s (Box of 100’s) | Rx | Hizon Laboratories, Inc.Rizal | — | DRP-217 | Oct 10, 2031 | |
UrisolAllopurinol | 100 mg TabletAlu/PVC Blister Pack x 10's (Box of 100's) | Rx | Centurion Remedies Pvt. Ltd.India | Philgen Pharmaceuticals Inc. | DRP-10108 | Mar 6, 2031 | |
UrisolAllopurinol | 100 mg TabletAlu/Amber PVDC Blister Pack x 10's (Box of 100's) | Rx | Centurion Laboratories Pvt. Ltd.India | Philgen Pharmaceuticals Inc. | DRP-15189 | May 22, 2029 | |
XanpurinAllopurinol | 300 mg TabletBlister Pack x 10's (Box of 100's) | Rx | Lloyd Laboratories, Inc.Philippines | Trader: Corbridge Group Phils., Inc. | DR-XY25636 | Nov 4, 2029 | |
ZylnolAllopurinol | 300 mg TabletFoil Strip x 10's (Box of 100's) | Rx | Lloyd Laboratories, Inc.Philippines | D And JB Pharma Medica Corp.Trader: Foramen Products Corporation | DRP-494-01 | Aug 26, 2031 | |
ZyloprimAllopurinol | 100 mg TabletAlu/ PVC Blister Pack x 25's Box of 100's | Rx | Aspen Bad Oldesloe GmbHGermany | Importer: Aspen Philippines, Inc. | DR-273 | Oct 3, 2027 | |
ZyloprimAllopurinol | 300 mg TabletAlu/PVC Blister Pack of 10's Box of 100's | Rx | Aspen SA Operations (Pty) LtdRepublic of South Africa | Aspen Philippines Inc. | DR-XY46133 | Oct 25, 2027 | |
(no brand name)Allopurinol | 100 mg TabletAlu/PVC Clear Blister Foil x 20's (Box of 100's). | Rx | Diamond Laboratories Inc.Philippines | — | DRP-16194 | Jan 14, 2030 | |
(no brand name)Allopurinol | 300 mg TabletAlu/Clear PVC Blister Pack x 20's (Box of 100's) | Rx | Diamond Laboratories Inc.Philippines | — | DRP-14602 | Nov 3, 2028 | |
(no brand name)Allopurinol | 300 mg TabletAlu/Clear PVC Blister Pack x 10's (Box of 100's) | Rx | Harman Finochem LimitedIndia | Ritemed Phils., Inc. | DRP-15559 | Aug 15, 2029 |
Source: FDA Philippines product registration database. "Valid until" is the registration validity date listed by the FDA; a past date may mean a renewal is pending. Package insert links point to files published by the FDA.
United States (label)
Dosage forms and strengths (US label) US FDA label
3 DOSAGE FORMS & STRENGTHS Allopurinol tablets have functional scoring and are available in the following strengths: 100 mg: A flat-faced raised hexagon, beveled edge, white to off-white tablet, one side engraved “ZYLOPRIM 100” with a score bar and the other side plain. 200 mg: White to off-white, biconvex, round, scored tablets, imprinted “ZYLOPRIM” about the upper periphery, and 200 on the lower half, below the score and plain on the other side. 300 mg: A flat-faced raised hexagon, beveled edge, peach tablet, one side engraved “ZYLOPRIM 300” with a score bar and the other side plain. Tablets: 100 mg, 200 mg, and 300 mg, functionally scored.
Warnings/Precautions
- Skin Rash and Hypersensitivity: Allopurinol has been associated with serious and sometimes fatal dermatological reactions. Discontinue allopurinol tablets at the first appearance of skin rash or other signs of hypersensitivity reaction. (5.1)
- Gout Flares: May occur during initiation of treatment. Concurrent prophylactic treatment with colchicine or anti-inflammatory agents is recommended. (5.2)
- Nephrotoxicity: Allopurinol may affect kidney function. Patients with decreased kidney function require lower doses of allopurinol tablets. (5.3)
- Hepatoxicity: Cases of reversible hepatotoxicity have occurred. If signs and symptoms of hepatotoxicity develop, evaluate liver function. (5.4)
- Myelosuppression: Bone marrow suppression has been reported with allopurinol. (5.5)
- Potential Effect on Driving and Use of Machinery: Drowsiness, somnolence and dizziness have been reported in patients taking allopurinol tablets. (5.6)
5.1 Skin Rash and Hypersensitivity
5.1 Skin Rash and Hypersensitivity Serious and sometimes fatal dermatologic reactions, including toxic epidermal necrolysis (TEN), Stevens-Johnson syndrome (SJS), and drug reaction with eosinophilia and systemic symptoms (DRESS) have been reported in patients taking allopurinol [see Adverse Reactions (6)]. These reactions occur in approximately 5 in 10,000 (0.05%) patients taking allopurinol.
Other serious hypersensitivity reactions that have been reported include exfoliative, urticarial and purpuric lesions, generalized vasculitis, and irreversible hepatotoxicity. Discontinue allopurinol tablets permanently at the first appearance of skin rash or other signs which may indicate a hypersensitivity reaction. The HLA-B*58:01 allele is a genetic marker for severe skin reactions indicative of hypersensitivity to allopurinol.
Patients who carry the HLA-B*58:01 allele are at a higher risk of allopurinol hypersensitivity syndrome (AHS), but hypersensitivity reactions have been reported in patients who do not carry this allele. The frequency of this allele is higher in individuals of African, Asian (e.g., Han Chinese, Korean, Thai), and Native Hawaiian/Pacific Islander ancestry [see Clinical Pharmacology (12.5)].
The use of allopurinol tablets is not recommended in HLA- B*58:01 positive patients unless the benefits clearly outweigh the risks. Consider screening for HLA-B*5801 before starting treatment with allopurinol tablets in patients from populations in which the prevalence of this HLA-B*5801 allele is known to be high. Screening is generally not recommended in patients from populations in which the prevalence of HLA-B*58:01 is low, or in current allopurinol users, as the risk of SJS/TEN/DRESS is largely confined to the first few months of therapy, regardless of HLA- B*58:01 status.
Hypersensitivity reactions to allopurinol tablets may be increased in patients with decreased kidney function receiving thiazide diuretics and allopurinol tablets concurrently. Concomitant use of the following drugs may also increase the risk of skin rash, which may be severe: bendamustine, ampicillin and amoxicillin [see Drug Interactions (7.1)].
Discontinue allopurinol tablets immediately if a skin rash develops. Instruct patients to stop taking allopurinol tablets immediately and seek medical attention promptly if they develop a rash.
5.2 Gout Flares
5.2 Gout Flares Gout flares have been reported during initiation of treatment with allopurinol tablets, even when normal or subnormal serum uric acid levels have been attained due to the mobilization of urates from tissue deposits. Even with adequate therapy with allopurinol tablets, it may require several months to deplete the uric acid pool sufficiently to achieve control of the flares.
The flares typically become shorter and less severe after several months of therapy. In order to prevent gout flares when treatment with allopurinol tablets is initiated, concurrent prophylactic treatment with colchicine or an anti-inflammatory agent is recommended [see Dosage and Administration (2.2)]. Advise patients to continue allopurinol tablets and prophylactic treatment even if gout flares occur, as it may take months to achieve control of gout flares.
5.3 Nephrotoxicity
5.3 Nephrotoxicity Treatment with allopurinol tablets may result in acute kidney injury due to formation of xanthine calculi or due to precipitation of urates in patients receiving concomitant uricosuric agents. Patients with pre-existing kidney disease, including chronic kidney disease or history of kidney stones, may be at increased risk for worsening of kidney function or acute kidney injury due to xanthine calculi while receiving treatment with allopurinol tablets.
In patients receiving allopurinol tablets for the management of gout or the management of recurrent calcium oxalate calculi, monitor kidney function frequently during the early stages of allopurinol administration. Maintain fluid intake sufficient to yield a urinary output of at least 2 liters per day of neutral or, preferably, slightly alkaline urine to avoid the possibility of formation of xanthine calculi and help prevent renal precipitation of urates in patients receiving concomitant uricosuric agents.
In patients receiving allopurinol tablets for the management of tumor lysis syndrome, monitor kidney function at least daily during the early stages of allopurinol administration. Maintain fluid intake sufficient to yield a urinary output of at least 2 liters per day in adults and at least 2 liters/m 2 /day (or at least 100 mL/m 2 /hour) in pediatric patients [see Dosage and Administration (2.4)].
5.4 Hepatotoxicity
5.4 Hepatotoxicity Cases of reversible clinical hepatotoxicity have occurred in patients taking allopurinol tablets, and in some patients, asymptomatic rises in serum alkaline phosphatase or serum transaminase have been observed. If anorexia, weight loss, or pruritus develop in patients on allopurinol tablets, evaluate liver enzymes.
In patients with pre-existing liver disease, monitor liver enzymes periodically. Discontinue allopurinol tablets in patients with elevated liver enzymes.
5.5 Myelosuppression
5.5 Myelosuppression Myelosuppression, manifested by anemia, leukopenia or thrombocytopenia, has been reported in patients receiving allopurinol tablets. The cytopenias have occurred as early as 6 weeks up to 6 years after the initiation of therapy of allopurinol tablets. Concomitant use of allopurinol tablets with cytotoxic drugs associated with myelosuppression may increase the risk of myelosuppression.
Monitor blood counts more frequently when cytotoxic drugs are used concomitantly [see Drug Interactions (7.2)]. Concomitant use with allopurinol increases the exposure of either mercaptopurine or azathioprine which may increase the risk of myelosuppression. Reduce the dosage of mercaptopurine or azathioprine as recommended in their respective prescribing information when used concomitantly with allopurinol tablets [see Drug Interactions (7.2)].
5.6 Potential Effect on Driving and Use of Machinery
5.6 Potential Effect on Driving and Use of Machinery Drowsiness, somnolence and dizziness have been reported in patients taking allopurinol tablets [see Adverse Reactions (6)]. Inform patients also that the central nervous system depressant effects of allopurinol tablets may be additive to those of alcohol and other CNS depressants.
Advise patients to avoid operation of automobiles or other dangerous machinery and activities made hazardous by decreased alertness when starting allopurinol tablets or increasing the dose, until they know how the drug affects them.
Drug interactions
| Drug or class | Severity | Effect | What to do |
|---|---|---|---|
| Thiazide diuretics | Adjust or monitor | Higher risk of skin rash and hypersensitivity; kidney impairment adds to the risk. | Monitor kidney function and reduce the allopurinol dose in kidney impairment; stop at the first rash. |
| Azathioprine or mercaptopurine | Adjust or monitor | Allopurinol blocks their metabolism; more myelosuppression. | With allopurinol 300 to 600 mg/day, cut the azathioprine or mercaptopurine dose to about one-third to one-fourth. |
| Capecitabine | Avoid | Lower levels of capecitabine's active metabolites; may reduce efficacy. | Do not use allopurinol during capecitabine treatment. |
| Pegloticase | Avoid | Can blunt the urate rise that signals loss of response and raise anaphylaxis risk. | Stop and do not start allopurinol during pegloticase. |
| Cyclosporine | Adjust or monitor | Higher cyclosporine levels. | Check cyclosporine levels more often and adjust its dose. |
| Chlorpropamide | Adjust or monitor | Longer chlorpropamide half-life (competing tubular excretion); hypoglycemia risk in renal insufficiency. | Monitor for hypoglycemia in kidney impairment. |
| Warfarin or dicumarol | Adjust or monitor | May enhance the anticoagulant effect. | Monitor prothrombin time and adjust the anticoagulant. |
| Ampicillin, amoxicillin, bendamustine | Adjust or monitor | More skin rash, which may be severe. | Stop allopurinol at the first rash or sign of hypersensitivity. |
Severity scale (renalcarematters.com): Avoid: do not combine; Adjust or monitor: change the dose or monitor closely; Minor: usually no action.
renalcarematters.com, reviewed- The following drugs may increase the risk of serious skin reactions: bendamustine, thiazide diuretics, ampicillin and amoxicillin. (7.1)
- Capecitabine: Avoid concomitant use. (7.2)
- Mercaptopurine or Azathioprine: Reduce mercaptopurine or azathioprine dose as recommended in the respective prescribing information. (7.2)
- Pegloticase: Discontinue and refrain from initiating treatment with allopurinol tablets. (7.2)
- See FPI for complete list of significant drug interactions. (7.2)
7.1 Drugs Known to Affect the Occurrence of Skin Rash and Hypersensitivity
7.1 Drugs Known to Affect the Occurrence of Skin Rash and Hypersensitivity Concomitant use of the following drugs may increase the risk of skin rash, which may be severe: bendamustine, thiazide diuretics, ampicillin and amoxicillin. Renal impairment may further increase risk with concomitant use of thiazide diuretics [see Warnings and Precautions (5.1, 5.2) and Clinical Pharmacology (12.2)].
Monitor kidney function and reduce the dose of allopurinol tablets in patients with concomitant thiazide diuretic use and impaired renal function [see Dosage and Administration (2.6), Warnings and Precautions (5.1)]. Discontinue allopurinol tablets at the first appearance of skin rash or other signs which may indicate a hypersensitivity reaction when use concomitantly with these drugs [see Warnings and Precautions (5.1)].
7.2 Drugs Known to Have Clinically Important Drug Interactions with Allopurinol Tablets
7.2 Drugs Known to Have Clinically Important Drug Interactions with Allopurinol Tablets Table 3: Interventions for Clinically Important Drug Interactions with Allopurinol Tablets Capecitabine Clinical Impact Concomitant use with allopurinol may decrease concentration of capecitabine’s active metabolites, which may decrease capecitabine efficacy. Intervention Avoid the use of allopurinol tablets during treatment with capecitabine Chlorpropamide Clinical Impact Allopurinol tablets prolongs the half-life of chlorpropamide as both compete for renal tubular excretion.
In patients with renal insufficiency, the risk of hypoglycemia may be increased due to this mechanism. Intervention Monitor patients with renal insufficiency for hypoglycemia when administering chlorpropamide and allopurinol tablets concomitantly. Cyclosporine Clinical Impact Concomitant use of allopurinol increases cyclosporine concentrations, which may increase the risk of adverse reactions.
Intervention Increase frequency of monitoring cyclosporine concentrations as reflected in its prescribing information and modify the dosage of cyclosporine as appropriate when used concomitantly with allopurinol tablets. Cyclophosphamide and Other Cytotoxic Agents Clinical Impact Concomitant use of allopurinol with cyclophosphamide and other cytotoxic agents (doxorubicin, bleomycin, procarbazine, mechloroethamine) increases bone marrow suppression among patients with neoplastic disease, except leukemia.
Intervention Blood count monitoring and regular physician follow-up are recommended. Dicumarol Clinical Impact Allopurinol tablets prolongs the half-life of the anticoagulant, dicumarol. The mechanism of this drug interaction has not been established but should be noted when allopurinol tablet is given to patients already on dicumarol therapy.
Intervention Monitor prothrombin time. Adjust the dosage of dicumarol accordingly when allopurinol tablet is added to anticoagulant therapy. Fluorouracil Clinical Impact Based on non-clinical data, allopurinol may decrease anti-tumor activity due to suppression of phosphorylation of 5-fluorouracil. Intervention Concomitant administration with fluorouracil should be avoided.
Mercaptopurine or Azathioprine Clinical Impact Allopurinol inhibits xanthine oxidase mediated metabolism of mercaptopurine and azathioprine. Concomitant use of allopurinol increases the exposure of either mercaptopurine or azathioprine which may increase the risk of their adverse reactions, including myelosuppression [see Warnings and Precautions 5.5].
Intervention In patients receiving mercaptopurine or azathioprine, the concomitant administration of 300 mg to 600 mg of allopurinol per day will require a reduction in dose to approximately one third to one fourth of the usual dose of mercaptopurine or azathioprine. Subsequent adjustment of doses of mercaptopurine or azathioprine should be made on the basis of therapeutic response and the appearance of toxic effects.
Pegloticase Clinical Impact Concomitant use of allopurinol tablets and pegloticase may potentially blunt the rise of serum uric acid levels and increase the risk of pegloticase related anaphylaxis in patients whose uric acid level increase to above 6 mg/dL. Intervention Discontinue and do not institute allopurinol therapy during treatment with pegloticase.
Theophylline Clinical Impact Concomitant use of allopurinol doses greater than or equal to 600 mg/day may decrease the clearance of theophylline Intervention Monitor and adjust theophylline doses as reflected in the prescribing information. Uricosuric Drugs Clinical Impact Uricosuric agents increase the excretion of the active allopurinol metabolite oxypurinol.
Concomitant use with uricosuric agents decreases oxypurinol exposure which may reduce the inhibition of xanthine oxidase by oxypurinol and increases the urinary excretion of uric acid. The net effect of such combined therapy may be useful in some patients in achieving minimum serum uric acid levels provided the total urinary uric acid load does not exceed the competence of the patient's kidney function.
Intervention Monitor uric acid levels due to the increased chance of hypouricemic effects. Warfarin Clinical Impact Allopurinol may inhibit the metabolism of warfarin, possibly enhancing its anticoagulant effect. Intervention Monitor patients on concomitant therapy for excessive anticoagulation. Assess INR frequently and adjust warfarin dosage accordingly when allopurinol is added to warfarin therapy.
Adverse reactions
Common
- Skin rash (most frequent)
- Diarrhea, nausea (≥1%)
- Raised alkaline phosphatase, AST or ALT (≥1%)
Serious
- Severe skin reactions and hypersensitivity, sometimes fatal
- Nephrotoxicity (acute kidney injury)
- Hepatotoxicity
- Myelosuppression
- Gout flares on starting treatment
Adverse reactions (US label) US FDA label
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: Skin Rash and Hypersensitivity [see Warnings and Precautions (5.1)] Nephrotoxicity [see Warnings and Precautions (5.3)] Hepatoxicity [see Warnings and Precautions (5.4)] Myelosuppression [see Warnings and Precautions (5.5)] Potential Effect on Driving and Use of Machinery [see Warnings and Precautions (5.6)] The following adverse reactions associated with the use of allopurinol were identified in literature, unpublished clinical trials or postmarketing reports. Because some of these reactions were reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
The most frequent adverse reaction to allopurinol is skin rash. Most Common Adverse Reactions (≥ 1%) Gastrointestinal: Diarrhea, nausea, alkaline phosphatase increase, AST/ALT increase. Metabolic and Nutritional: Acute attacks of gout. Skin and Appendages: Rash, maculopapular rash. Less Common Adverse Reactions (< 1%) Body As a Whole: Ecchymosis, fever, headache, malaise.
Cardiovascular: Necrotizing angiitis, vasculitis, pericarditis, peripheral vascular disease, thrombophlebitis, bradycardia, vasodilation. Gastrointestinal: Hepatic necrosis, granulomatous hepatitis, hepatomegaly, hyperbilirubinemia, cholestatic jaundice, vomiting, intermittent abdominal pain, gastritis, dyspepsia, hemorrhagic pancreatitis, gastrointestinal bleeding, stomatitis, salivary gland swelling, hyperlipidemia, tongue edema, anorexia.
Hemic and Lymphatic: Thrombocytopenia, eosinophilia, leukocytosis, leukopenia, aplastic anemia, agranulocytosis, eosinophilic fibrohistiocytic lesion of bone marrow, pancytopenia, prothrombin decrease, anemia, hemolytic anemia, reticulocytosis, lymphadenopathy, lymphocytosis. Musculoskeletal: Myopathy, arthralgias, myalgia.
Nervous: Peripheral neuropathy, neuritis, paresthesia, somnolence, optic neuritis, confusion, dizziness, vertigo, foot drop, decrease in libido, depression, amnesia, tinnitus, asthenia, insomnia. Respiratory: Epistaxis, bronchospasm, asthma, pharyngitis, rhinitis. Skin and Appendages: Erythema multiforme exudativum (Stevens-Johnson syndrome), toxic epidermal necrolysis (Lyell's syndrome), hypersensitivity vasculitis, purpura, vesicular bullous dermatitis, exfoliative dermatitis, eczematoid dermatitis, pruritus, urticaria, alopecia, onycholysis, lichen planus, furunculosis, facial edema, sweating, skin edema.
Special Senses: Taste loss/perversion, cataracts, macular retinitis, iritis, conjunctivitis, amblyopia. Urogenital: Renal failure, uremia, nephritis, impotence, primary hematuria, albuminuria. Endocrine: Infertility (male), hypercalcemia, gynecomastia (male). Most common adverse reactions (incidence > 1%) are nausea, diarrhea, and increase in liver function tests.
(6) To report SUSPECTED ADVERSE REACTIONS, Rising Pharma Holdings, Inc. at 1-844-874-7464 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
Monitoring parameters
- Consider HLA-B*58:01 testing before starting in patients of Asian ancestry (the label names Han Chinese, Korean and Thai; label 5.1); avoid in carriers unless benefit clearly outweighs risk. The kidney-band doses are starting doses: increase by 50 mg/day every 2 to 4 weeks to serum urate below 6 mg/dL; the label does not define a maximum by eGFR, and ACR 2020 supports titration above traditional CrCl-based doses. Monitor kidney function closely when starting in chronic kidney disease (CKD); reduce or stop if kidney abnormalities appear and persist. Watch for serious skin reactions. Kidney
- HLA-B*58:01: consider testing before starting in patients of Southeast Asian (including Filipino), Han Chinese, Korean, Thai, African or Pacific Islander ancestry; avoid allopurinol in carriers unless benefit clearly outweighs risk (label 5.1; ACR 2020). CKD increases the risk of severe hypersensitivity.
- Before starting: serum urate, complete blood count, chemistry panel, liver tests, serum creatinine and eGFR (label)
- Serum urate during titration (target 6 mg/dL or less)
- Kidney function closely in CKD
- Skin rash or other hypersensitivity signs
Pregnancy considerations
Pregnancy (US label) US FDA label
8.1 Pregnancy Risk Summary Based on findings in animals, allopurinol may cause fetal harm when administered to a pregnant woman. Adverse developmental outcomes have been described in exposed animals (see Data). Allopurinol and its metabolite oxypurinol have been shown to cross the placenta following administration of maternal allopurinol.
Available limited published data on allopurinol use in pregnant women do not demonstrate a clear pattern or increase in frequency of adverse developmental outcomes. Among approximately 50 pregnancies described in published literature, 2 infants with major congenital malformations have been reported with following maternal allopurinol exposure.
Advise pregnant women of the potential risk to a fetus. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. The background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Human Data Experience with allopurinol during human pregnancy has been limited partly because women of reproductive age rarely require treatment with allopurinol. A case report published in 2011 described the outcome of a full-term pregnancy in a 35-year-old woman who had recurrent kidney stones since age 18 who took allopurinol throughout the pregnancy.
The child had multiple complex birth defects and died at 8 days of life. A second report in 2013 provided data on 31 prospectively ascertained pregnancies involving mothers exposed to allopurinol for varying durations during the first trimester. The overall rate of major fetal malformations and spontaneous abortions was reported to be within the normal expected range; however, one child had severe malformations similar to those described in the cited earlier case report.
Animal Data There was no evidence of fetotoxicity or teratogenicity in rats or rabbits treated during the period of organogenesis with oral allopurinol at doses up to 200 mg/kg/day and up to 100 mg/kg/day, respectively (about 2.4 times the human dose on a mg/m 2 basis). However, there is a published report in pregnant mice that single intraperitoneal doses of 50 mg/kg or 100 mg/kg (about 0.3 or 0.6 times the human dose on a mg/m 2 basis) of allopurinol on gestation days 10 or 13 produced significant increases in fetal deaths and teratogenic effects (cleft palate, harelip, and digital defects).
It is uncertain whether these findings represented a fetal effect or an effect secondary to maternal toxicity.
Mechanism of action
12.1 Mechanism of Action Allopurinol is a structural analogue of the natural purine base, hypoxanthine. Allopurinol acts on purine catabolism, without disrupting the biosynthesis of purines. It reduces the production of uric acid by inhibiting the biochemical reactions immediately preceding its formation. It is an inhibitor of xanthine oxidase, the enzyme responsible for the conversion of hypoxanthine to xanthine and of xanthine to uric acid, the end product of purine metabolism in humans.
Allopurinol is metabolized to the corresponding xanthine analogue, oxypurinol (alloxanthine), which also is an inhibitor of xanthine oxidase.
US FDA labelPharmacodynamics
Pharmacodynamics (US label) US FDA label
12.2 Pharmacodynamics Allopurinol reduces the production of uric acid by inhibiting the biochemical reactions immediately preceding its formation in a dose dependent manner. The pharmacological action of allopurinol is generally believed to be mediated by its oxypurinol metabolite. Effect on Hypoxanthine and Xanthine Reutilization of both hypoxanthine and xanthine for nucleotide and nucleic acid synthesis is markedly enhanced when their oxidations are inhibited by allopurinol and oxipurinol.
This reutilization does not disrupt normal nucleic acid anabolism, however, because feedback inhibition is an integral part of purine biosynthesis. As a result of xanthine oxidase inhibition, the serum concentration of hypoxanthine plus xanthine in patients receiving allopurinol for treatment of hyperuricemia is usually in the range of 0.3 mg/dL to 0.4 mg/dL compared to a normal level of approximately 0.15 mg/dL.
A maximum of 0.9 mg/dL of these oxypurines has been reported when the serum urate was lowered to less than 2 mg/dL by high doses of allopurinol. These values are far below the saturation levels at which point their precipitation would be expected to occur (above 7 mg/dL). The increased xanthine and hypoxanthine in the urine in patients who were treated with oral allopurinol have not been accompanied by problems of nephrolithiasis; however, there are isolated case reports of xanthine crystalluria.
Drug Interaction Studies Fluorouracil: Based on non-clinical data, allopurinol may decrease anti-tumor activity due to suppression of phosphorylation of 5-fluorouracil. Pegloticase: Concomitant use of allopurinol and pegloticase may potentially blunt the rise of serum uric acid levels required for monitoring the safe use of pegloticase.
Cytotoxic Agents: Enhanced bone marrow suppression by cyclophosphamide and other cytotoxic agents has been reported among patients with neoplastic disease, except leukemia, in the presence of allopurinol. Thiazide Diuretics: Reports that the concomitant administration of allopurinol and thiazide diuretics contributed to increased allopurinol toxicity were reviewed; however, a causal mechanism or cause-and-effect relationship was not found.
Pharmacokinetics
Key PK parameters
| Bioavailability | About 90% absorbed |
|---|---|
| Time to peak | 1.5 hours (allopurinol); 4.5 hours (oxipurinol) |
| Half-life | Allopurinol 1 to 2 hours; oxipurinol about 15 hours |
| Half-life in kidney failure (ESKD) kidney | Oxipurinol half-life markedly prolonged in kidney failure (label gives no figure; exposure rises steeply as eGFR falls, 8.6). |
| Metabolism (CYP, transporters) | Converted to oxipurinol (oxypurinol), also a xanthine oxidase inhibitor |
| Active metabolites | Oxipurinol |
| Renal excretion kidney | Renal (oxipurinol unchanged in urine by filtration and tubular reabsorption); about 20% of the dose in feces |
| Dialyzability kidney | Yes: allopurinol and oxipurinol are dialyzable; value in overdose unknown (label). |
Elimination The half-life of allopurinol and oxipurinol are approximately 1 hour to 2 hours and 15 hours following oral dose of allopurinol, respectively.
Excretion Allopurinol and its primary active metabolite, oxipurinol, are eliminated by the kidneys.
Approximately 20% of the ingested allopurinol is excreted in the feces.
Uricosuric Agents : Uricosuric agents increase the excretion of the active allopurinol metabolite oxypurinol.
Concomitant use with uricosuric agents decreases oxypurinol exposure which may reduce the inhibition of xanthine oxidase by oxypurinol and increases the urinary excretion of uric acid.
Pharmacokinetics (US label) US FDA label
12.3 Pharmacokinetics Absorption Allopurinol is approximately 90% absorbed from the gastrointestinal tract. Peak plasma levels generally occur at 1.5 hours and 4.5 hours for allopurinol and oxipurinol respectively. After a single oral dose of 300 mg allopurinol, maximum plasma levels of about 3 mcg/mL of allopurinol and 6.5 mcg/mL of oxipurinol are produced.
Elimination The half-life of allopurinol and oxipurinol are approximately 1 hour to 2 hours and 15 hours following oral dose of allopurinol, respectively. Metabolism Allopurinol is metabolized to the corresponding xanthine analogue, oxypurinol (alloxanthine), which also is an inhibitor of xanthine oxidase. Excretion Allopurinol and its primary active metabolite, oxipurinol, are eliminated by the kidneys.
Approximately 20% of the ingested allopurinol is excreted in the feces. Oxipurinol is primarily eliminated unchanged in urine by glomerular filtration and tubular reabsorption. Drug Interaction Studies Capecitabine: Concomitant use with allopurinol may decrease concentration of capecitabine’s active metabolites, which may decrease capecitabine efficacy.
Cyclosporine: Concomitant use of allopurinol increases cyclosporine concentrations which may increase the risk of adverse reactions. Mercaptopurine or Azathioprine: Allopurinol inhibits xanthine oxidase mediated metabolism of mercaptopurine and azathioprine. Concomitant use of allopurinol increases the exposure of either mercaptopurine or azathioprine which may increase the risk of their adverse reactions including myelosuppression.
Theophylline: Concomitant use of allopurinol doses greater than or equal to 600 mg/day may decrease the clearance of theophylline. Uricosuric Agents: Uricosuric agents increase the excretion of the active allopurinol metabolite oxypurinol. Concomitant use with uricosuric agents decreases oxypurinol exposure which may reduce the inhibition of xanthine oxidase by oxypurinol and increases the urinary excretion of uric acid.
Warfarin: Allopurinol may inhibit the metabolism of warfarin, possibly enhancing its anticoagulant effect.
Formulary and pricing (Philippines)
Government price references
| Preparation | Price (PHP) | Unit | Type |
|---|---|---|---|
| Allopurinol 100 mg Tablet | ₱0.80–₱4.35Reference ₱1.61 | per tablet | DPRI procurement range |
| Allopurinol 300 mg Tablet | ₱1.10–₱9.25Reference ₱2.00 | per tablet | DPRI procurement range |
Range = lowest-highest procurement price (highest usable only in GIDA areas); reference_price = 2021 DPRI ceiling (median)
These are government procurement and reimbursement references, not retail prices. Sources:
- DOH Drug Price Reference Index (DPRI) 2021, 9th edition (as of September 17, 2021); https://caro.doh.gov.ph/wp-content/uploads/2021/09/2021DPRI-as-of-9-17-2021.pdf, as of September 17, 2021
Formulary and coverage
| Philippine National Formulary | Listed as Allopurinol |
| PNF listing | Oral: 100 mg and 300 mg tablet |
| PhilHealth GAMOT | No |
Sources:
- PNF Essential Medicines List, 8th ed. (as of November 2, 2022), DOH; https://www.philhealth.gov.ph/partners/providers/pdf/PNF-EML_11022022.pdf, as of November 2, 2022
Check availability
Prices and stock vary by branch; renalcarematters.com does not sell medicines or receive payment from pharmacies.
Related guides & calculators
Guides and calculators on renalcarematters.com for this medicine, for patients and clinicians.
 GuideThe CKD Prescriber's PlaybookClinician-focused operational guide: exactly how to start, titrate, and adjust SGLT2 inhibitors, ACEi/ARB, GLP-1 agonists, diuretics, phosphate binders, and ESAs in CKD and nephrology practice. KDIGO 2024 aligned.
 GuideEosinophilia and Kidney Disease: When the Count Changes the WorkupEosinophilia with AKI, CKD, dialysis, or kidney transplant problems — explained for patients and families in four languages, with a full clinician workup: red flags, biopsy and steroid decisions, and the Strongyloides check.
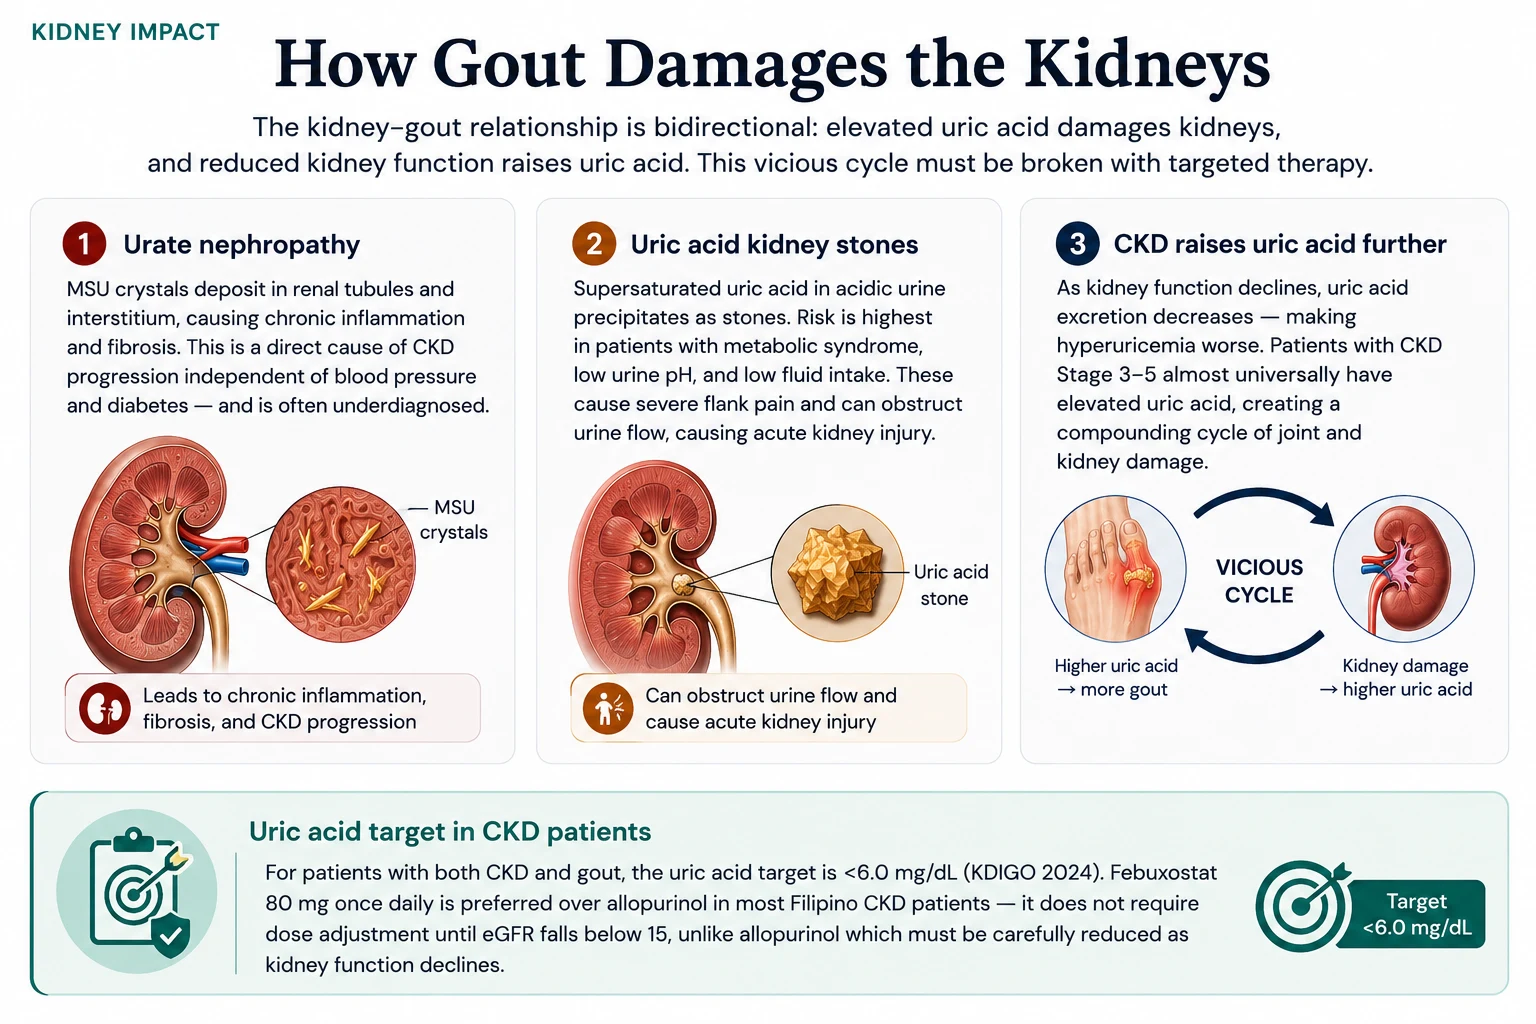 GuideGout — The Crystal Disease You Can Actually ConquerWhy uric acid builds up, how it damages joints and kidneys, gout flare prevention, low-purine Filipino foods, and allopurinol use in kidney disease patients.
- CalculatorUric Acid Target, FEUA & Urate-Lowering Therapy CalculatorInteractive uric acid calculator — serum urate vs target, fractional excretion of uric acid (FEUA) to classify under-excretor vs over-producer, and febuxostat/allopurinol dose guidance by eGFR. With indications, formula, evidence, and refer
- CalculatorRenal Dosing: Nerve Pain & Gout Medicines — Dose Adjustment by CrClLook up renally-adjusted doses for gabapentin, pregabalin, allopurinol, tramadol, and colchicine by Cockcroft–Gault creatinine clearance. Built-in CrCl calculator plus auditable, label/guideline-referenced dose bands with avoid/reduce/stand
- CalculatoreGFR Calculator — CKD-EPI 2021 (race-free)Estimate GFR from serum creatinine using the race-free CKD-EPI 2021 creatinine equation. Enter age, sex, and creatinine to get eGFR and CKD stage. With indications, formula, evidence, and references.
References
- U.S. Food and Drug Administration. Allopurinol · Rising Pharma Holdings, Inc. [US FDA-approved label, version 5, May 21, 2026]. Via DailyMed/openFDA. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=30ad5ba2-1cef-4933-b104-0597f6a2aaa2
- Food and Drug Administration Philippines. Verification portal (product registrations). https://verification.fda.gov.ph
- PNF Essential Medicines List, 8th ed. (as of November 2, 2022), DOH; https://www.philhealth.gov.ph/partners/providers/pdf/PNF-EML_11022022.pdf
- DOH Drug Price Reference Index (DPRI) 2021, 9th edition (as of September 17, 2021); https://caro.doh.gov.ph/wp-content/uploads/2021/09/2021DPRI-as-of-9-17-2021.pdf
- Rising Pharma Holdings, Inc.. (2026). Allopurinol (allopurinol) [Prescribing information; US FDA-approved label, NDA016084, set ID 30ad5ba2-1cef-4933-b104-0597f6a2aaa2, version effective May 21, 2026]. DailyMed, U.S. National Library of Medicine. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=30ad5ba2-1cef-4933-b104-0597f6a2aaa2
- FitzGerald, J. D., Dalbeth, N., Mikuls, T., Brignardello-Petersen, R., Guyatt, G., Abeles, A. M., Gelber, A. C., Harrold, L. R., Khanna, D., King, C., Levy, G., Libbey, C., Mount, D., Pillinger, M. H., Rosenthal, A., Singh, J. A., Sims, J. E., Smith, B. J., Wenger, N. S., ... Neogi, T. (2020). 2020 American College of Rheumatology guideline for the management of gout. Arthritis Care & Research, 72(6), 744–760. https://doi.org/10.1002/acr.24180
- Schwartz, G. J., Muñoz, A., Schneider, M. F., Mak, R. H., Kaskel, F., Warady, B. A., & Furth, S. L. (2009). New equations to estimate GFR in children with CKD. Journal of the American Society of Nephrology, 20(3), 629–637. https://doi.org/10.1681/ASN.2008030287
renalcarematters.com content: Kidney and pediatric dosing: reviewed by William Gregory M. Rivero, MD, FPCP, DPSN on November 17, 2026. Dosing, interaction, adverse-effect and monitoring summary: reviewed by William Gregory M. Rivero, MD, FPCP, DPSN on November 16, 2026.
Last updated: .